
LSD Blotters

Minus 12.3 MADRS: Psilocybin Trial Evidence for Clinicians

Randomized clinical trials show that a single 25 mg dose of psilocybin, paired with structured psychological support, produces clinically meaningful drops in depressive symptoms for many adults with major depressive disorder or treatment-resistant depression. Benefits often show up within days and can persist for weeks to months. The evidence is real but still incomplete: trials are small, blinding is imperfect, and some studies report increased suicidal ideation on dosing days, which is why every trial has kept psilocybin inside supervised medical settings.
TL;DR:
- Psilocybin shows faster onset of antidepressant effects, often within days, with peak benefits typically appearing between one and six weeks after dosing.
- The most effective dose consistently used in trials is 25 mg, with lower doses showing smaller and less reliable symptom reductions.
- A 4% rate of suicidal ideation on dosing days in some trials justifies supervised medical settings and thorough psychiatric screening.
- Small sample sizes and blinding issues across studies limit the certainty of long-term safety and efficacy data, emphasizing the need for larger, more rigorous trials.
- Clinical support, including preparation and integration sessions, likely plays a crucial role in maintaining treatment benefits beyond the primary dosing session.
Table of Contents
- What Do Clinical Trials Show About Psilocybin and Depression?
- How Might Psilocybin Actually Relieve Depression?
- How Is Psilocybin Therapy Actually Delivered in Trials?
- What Are the Safety Risks and Who Should Avoid Psilocybin?
- Who Tends to Respond Best to Psilocybin Treatment?
- What Are the Biggest Gaps in the Current Evidence?
- Where Fungipsilocybinmushroom Fits Into Informed and Safe Use
- Primary Sources and Further Reading
- An Honest Read on Where This Research Actually Stands
- Buy Lab-Tested Mushrooms and Learn Safe, Informed Use
- Sources
- FAQ
What Do Clinical Trials Show About Psilocybin and Depression?
Three trials anchor most of what we currently know about psilocybin for depression, and the numbers are specific enough to actually evaluate.
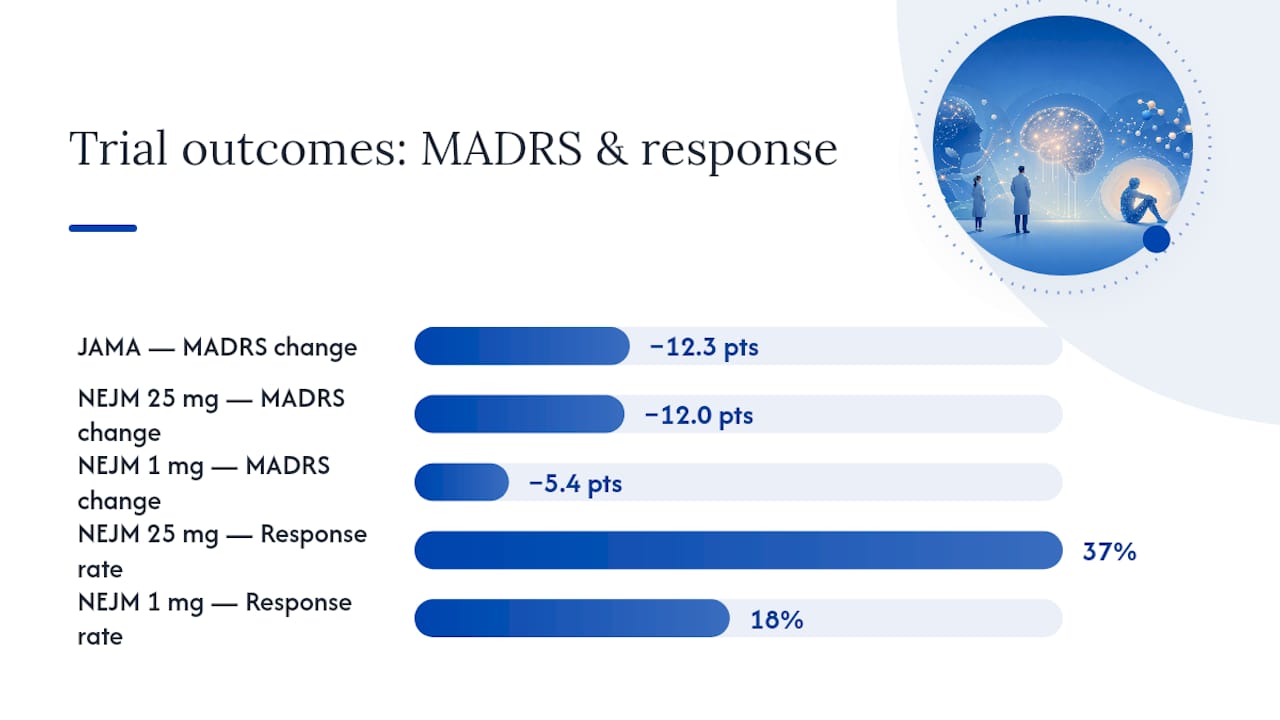
The JAMA multi-site phase 2 trial randomized adults with major depressive disorder to 25 mg psilocybin or a niacin placebo. By day 43, the psilocybin group showed a mean MADRS score difference of −12.3 compared to placebo, a gap large enough to represent the difference between moderate depression and near remission on that scale. Sustained response rates were also higher in the psilocybin arm, meaning the benefit wasn’t just a one-week spike that faded.
The NEJM trial took a different comparison approach, testing 25 mg against a 1 mg near-inactive dose in people with a treatment-resistant depressive episode. At week 3, the 25 mg group had a least-squares mean MADRS change of −12.0, versus −5.4 for the 1 mg group. Response rates told a similar story: 37% of the high-dose group responded compared to 18% on the near-placebo dose. Adverse events were mostly headache and nausea, though the trial also recorded some reports of suicidal ideation.
Then there’s the EPISODE trial, a phase 2b study focused specifically on treatment-resistant depression, and it’s the one that keeps the field honest. With 144 adults randomized, the primary endpoint at week 6 (measured on the HAMD17 scale) did not reach statistical significance. That’s a real result, not a footnote. But secondary outcomes and within-participant analyses still pointed toward clinically meaningful benefit for the 25 mg group, and 4% of participants reported suicidal ideation on dosing days compared to 1 to 2% in the comparator arms.
Here’s the pattern across all three trials:
- Effects tend to appear fast, often within days of the dosing session, not weeks like conventional antidepressants.
- Peak differences between psilocybin and control groups usually show up somewhere between 1 and 6 weeks post-dose.
- Durability varies. Some trials show benefit holding at day 43 or later; others see effects narrowing over time.
- Response and remission rates consistently favor higher doses (25 mg) over low-dose comparators, even when the primary endpoint misses significance.
The MADRS gap that matters: A −12.3 point difference on the Montgomery-Åsberg Depression Rating Scale, as seen in the JAMA trial, is roughly the clinical distance between “moderately depressed” and “mostly recovered.” That’s the number worth remembering when someone tells you psilocybin’s effects are marginal.
A systematic review pooling multiple controlled trials found a consistent direction of benefit across the literature, with moderate-to-large effect sizes. The same review is equally clear about the catch: small sample sizes and blinding problems run through nearly every study in this field, which limits how confidently anyone can generalize the results yet.
How Might Psilocybin Actually Relieve Depression?
Psilocybin itself is a prodrug. Once ingested, the body converts it into psilocin, the compound that actually crosses into the brain and binds to serotonin receptors, most notably the 5-HT2A receptor. That binding triggers a cascade tied to short-term neuroplasticity, essentially a window where neural connections can reorganize more freely than usual.
Neuroimaging work adds a second layer to the story. fMRI studies from researchers at UCL describe a pattern now commonly called the “reset hypothesis”:
- Acutely, psilocybin disrupts the default mode network, the brain circuit associated with self-referential thinking and, in depression, often with rumination.
- Blood flow to the amygdala decreases during the acute phase, and that decrease correlates with reduced depressive symptoms afterward.
- In the days and weeks following dosing, certain default mode network connections and vmPFC to posterior cingulate circuits show increased connectivity, a pattern that tracks with clinical improvement.
- The rigid, repetitive thought loops common in depression appear to loosen temporarily, giving therapy and reflection more traction than usual.
None of this happens in a vacuum. The subjective experience itself, what researchers call a mystical-type or emotionally intense experience, seems to matter for outcomes. Clinical guidance on psychedelic-assisted therapy consistently points to set and setting, meaning the person’s mental state going in and the physical and emotional safety of the room, as a real driver of what happens during the session and how someone processes it afterward.
Worth saying plainly: mechanism research here is convergent, not conclusive. Much of the connectivity data is correlational, not causal, and the “reset” framing is a working hypothesis that fits the data well rather than a settled biological fact.
How Is Psilocybin Therapy Actually Delivered in Trials?
Every major trial follows roughly the same skeleton, even though the details vary by protocol. Understanding that structure matters more than fixating on the dose alone.
- Screening. Candidates go through psychiatric and medical evaluation to rule out contraindications like a personal or family history of psychosis or mania.
- Preparation sessions. Before any dosing, participants meet with trained facilitators to build trust, set intentions, and understand what physical and emotional sensations to expect.
- The dosing session. Most efficacy trials use 25 mg as the high, active dose, administered in a monitored clinical setting with trained staff present for the several hours the acute effects last. Lower-dose arms (1 mg in the NEJM trial, niacin in the JAMA trial) consistently show smaller symptom reductions.
- Integration sessions. Multiple follow-up therapy sessions after dosing help participants process what came up. Some researchers argue this step, not the dosing session itself, drives much of the sustained benefit.
Medication status complicates all of this. SSRIs and SNRIs can downregulate 5-HT2A receptor responsiveness, which may blunt psilocybin’s acute effects. That’s why trials typically require a supervised taper off these medications before dosing rather than an abrupt stop, which carries its own withdrawal and relapse risk.
Pro Tip: If you’re on an SSRI or SNRI and thinking about psilocybin down the road, the tapering conversation belongs with a prescribing clinician, not a calendar app. Stopping cold on your own timeline is one of the more avoidable risks in this whole picture.
Plenty remains unresolved: how often a dose should be repeated, whether synthetic psilocybin performs differently than the natural compound, and who can legally access supervised treatment in the first place, since regulatory frameworks vary widely by country and even by region within a country.
What Are the Safety Risks and Who Should Avoid Psilocybin?
Most adverse events in these trials are short-lived. Headache, nausea, dizziness, and transient anxiety or dysphoria during the dosing window show up consistently across studies, and they typically resolve within hours.
The more serious signals deserve direct attention rather than a footnote. The EPISODE trial recorded suicidal ideation in 4% of participants on 25 mg dosing days, compared to 1 to 2% in comparator groups. That’s not a reason to dismiss the treatment outright, but it is precisely why every trial keeps a clinician in the room during dosing and monitors participants closely afterward. Rare hallucinogen persisting perception disorder (HPPD) has also been reported in the broader psychedelic literature, though it shows up infrequently in controlled trial settings.
The number that shapes every protocol: A 4% rate of suicidal ideation on dosing days, documented in the EPISODE trial, is the exact reason supervised administration isn’t optional in this research. It’s also why home use for depression treatment sits entirely outside what the evidence currently supports.
Trials exclude people with:
- A personal or family history of psychosis, schizophrenia, or bipolar disorder with mania.
- Uncontrolled cardiovascular disease or other unstable medical conditions.
- Current substance use disorders that could complicate monitoring or interpretation of results.
These exclusions exist because psilocybin’s acute effects can intensify existing psychiatric vulnerabilities, and researchers need a clean signal to interpret results responsibly. Good clinical practice in this space includes thorough psychiatric screening, monitored sessions with trained staff, a clear emergency plan, and medication changes handled by a clinician rather than the patient alone.
Who Tends to Respond Best to Psilocybin Treatment?
Trials generally enroll two overlapping but distinct populations: people with major depressive disorder and people with treatment-resistant depression, meaning they’ve already failed multiple standard antidepressant trials. That distinction matters for interpreting results, since TRD populations tend to be harder to treat across the board, which makes the effect sizes in trials like EPISODE more notable, not less.
A few patterns show up repeatedly in trial analyses:
- People who report more intense subjective experiences during dosing, including emotional breakthrough or mystical-type qualities, tend to show larger symptom improvements afterward.
- Certain post-dose changes in brain connectivity correlate with better outcomes, though this research is still exploratory.
- Comorbid psychiatric conditions, active substance use, and unstable medical illness all reduce suitability and are consistently screened out in trial protocols.
None of this replaces an actual clinical evaluation. The trials that generated these findings ran inside supervised research settings with trained staff on hand for exactly this reason.
What Are the Biggest Gaps in the Current Evidence?
The honest caveats matter as much as the promising numbers. Sample sizes across these trials remain small by pharmaceutical standards, often in the dozens to low hundreds of participants rather than the thousands typically required for a new antidepressant approval.
Blinding is a persistent problem. It’s difficult to convince a participant they received an inactive placebo when the active dose produces hours of perceptual change, so “functional unblinding” likely inflates some reported benefits through expectancy effects alone. Endpoints also vary across trials (some use MADRS, others HAMD17), which makes cross-study comparison messier than it should be.
Open questions that still need answers include how long benefits actually last beyond a few months, whether psilocybin is safe across broader and more diverse populations than current trials include, how it stacks up against existing antidepressants and psychotherapy in head-to-head comparisons, and whether the treatment model is cost-effective at scale. Readers following this space should watch for larger phase 3 trials, pragmatic real-world studies, and longer safety follow-up before treating psilocybin as a settled clinical answer.

Where Fungipsilocybinmushroom Fits Into Informed and Safe Use
Fungipsilocybinmushroom exists to give people accurate information alongside lab-tested products, not to replace clinical care. Every strain listed, from Golden Teacher to Penis Envy, goes through lab testing before sale, and the site’s educational guide on Golden Teacher mushrooms and depression walks through strain-level differences that trial data alone doesn’t cover.
This page is educational, not medical advice. Nothing here substitutes for a licensed clinician’s evaluation, particularly given the psychiatric screening and monitored dosing that every trial cited above required. Readers exploring dosing questions can check the practical guide on how to dose magic mushrooms for harm-reduction context, and those weighing microdosing against the macrodose protocols used in trials can compare approaches in the microdosing psychedelics resource. For treatment decisions specifically, talk to a clinician.
Primary Sources and Further Reading
For readers who want to check the trial data directly: the JAMA phase 2 randomized trial and NEJM treatment-resistant depression trial sit behind journal paywalls, while the EPISODE trial and the systematic review of psilocybin for major depressive disorder are both open access through PMC. The UCL fMRI mechanism study is also freely available and worth reading for the neuroimaging detail alone.
An Honest Read on Where This Research Actually Stands
The conventional pitch you’ll hear about psilocybin depression treatment tends to oversell certainty in one direction. Advocates point to the JAMA and NEJM numbers as though the case is closed; skeptics point to EPISODE’s nonsignificant primary endpoint as though the whole field collapsed. Both readings miss what the data actually supports: a genuinely promising but still-forming treatment, hemmed in by small trials and blinding problems that no amount of enthusiasm fixes.
What gets underweighted in most coverage is the integration piece. The dosing session gets all the attention because it’s dramatic, but the research on psychological support during psychedelic therapy suggests the follow-up therapy sessions may carry as much weight as the mushroom itself. Treating psilocybin as a pill that does the work alone misreads every protocol that produced these results.
If you take one thing from this research, prioritize the safety screening and the supervised structure over the dose number. A 25 mg benchmark means nothing without the clinical oversight the trials built around it.
— Alex
Buy Lab-Tested Mushrooms and Learn Safe, Informed Use
This vendor offers lab-tested products and evidence-based educational materials to support informed use, rather than relying on vague marketing claims about mood and wellness.
The catalog includes various strains, capsules, edibles, teas, and grow kits for home cultivation. Products are tested before shipping, and orders are shipped with discretion and privacy in mind. If you’re an adult exploring psilocybin for personal or therapeutic use and want a source that treats safety and lab verification as the baseline rather than an upsell, browse the full product catalog to see current strains and formats, or check the guide on buying mushroom capsules in the USA if capsules fit your routine better than dried product.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
- Single-Dose Psilocybin Treatment for Major Depressive Disorder: A Randomized Clinical Trial | JAMA
- Single-Dose Psilocybin for a Treatment-Resistant Episode of Major Depression | NEJM
- Psilocybin for treatment-resistant depression: fMRI-measured brain mechanisms (UCL discovery)
FAQ
Does Psilocybin Actually Help With Depression?
Clinical trials show psilocybin combined with psychological support can produce clinically meaningful reductions in depression, with a mean MADRS difference of −12.3 versus placebo at day 43 in one major trial. Results vary by study, and not every trial has hit statistical significance on its primary endpoint.
How Long Do Psilocybin’s Antidepressant Effects Last?
Benefits often appear within days and can persist for weeks to months, with peak differences between treatment and control groups typically showing up between week 3 and day 43 across major trials. Durability beyond a few months is still an open research question.
Is Psilocybin Safe for Treating Depression?
Common side effects like headache, nausea, and transient anxiety are typically short-lived, but some trials have reported increased suicidal ideation on dosing days, including in 4% of EPISODE trial participants on the 25 mg dose. This is why psilocybin depression research happens exclusively in supervised medical settings with psychiatric screening beforehand.
What Dose of Psilocybin Is Used in Depression Trials?
Most major trials use 25 mg as the high, active therapeutic dose, compared against much lower doses like 1 mg or an inactive placebo like niacin. Lower-dose comparison arms consistently show smaller symptom reductions in trials like the NEJM study.
Can I Buy Lab-Tested Psilocybin Mushrooms From Fungipsilocybinmushroom?
Yes, Fungipsilocybinmushroom sells lab-tested dried mushrooms, capsules, edibles, teas, and grow kits, including strains like Golden Teacher and Penis Envy, with worldwide discreet delivery. Current pricing and available strains are listed directly on the product catalog.
Recommended
- Psilocybin Depression Treatment California: Your Complete Guide to Legal Mushroom Delivery Services and Therapeutic Options 2025
- How to Dose Magic Mushrooms
- Microdosing Psychedelics: Unveiling Remarkable Health Benefits and Therapeutic Potential 2026
- Blue Meanie vs Penis Envy Magic Mushrooms – Best Strain for Depression & Anxiety Relief (Buy Online at Psychedelic Today) 2026

Shrooms Drug Test: Federal Panels Skip Psilocin, DoD Added It in 2026
Standard workplace drug tests don’t screen for psilocybin or psilocin, so a routine 5-panel or 10-panel test almost never flags mushroom use. Specialized mass-spectrometry tests can detect psilocin, but the window is short, often around 24 hours in urine. The real exceptions are military programs, court-ordered testing, and forensic toxicology, where labs sometimes order psilocin specifically.
TL;DR:
- Routine workplace drug tests rarely detect psilocybin or psilocin because standard panels do not include these substances and specialized tests are costly.
- Psilocin has a detection window of about 24 hours in urine and less than a day in blood, making detection difficult after this period without targeted testing.
- Specialized mass spectrometry methods like LC-MS/MS or GC-MS are necessary for definitive detection, and most agencies only order these when legally or medically justified.
- The Department of Defense began testing for psilocin in 2025, making military testing an exception to typical civilian screening policies.
- False positives for shrooms on standard panels are rare, and confirmatory testing is essential to verify any initial positive result.
Table of Contents
- Does a Shrooms Drug Test Show Up on Standard Panels?
- How Long Does Psilocybin Stay in Your System?
- When Do Labs Order a Specialized Psilocybin Test?
- What Actually Changes Your Detection Risk?
- Can a Drug Test Give a False Positive for Shrooms?
- What Do the Federal Guidelines and Research Say?
- What Should You Actually Do If You’re Worried About a Test?
- Sources
- FAQ
Does a Shrooms Drug Test Show Up on Standard Panels?
The immunoassay panels used by most employers, from pre-employment screens to random workplace checks, are built to catch a fixed list of substances: THC, cocaine, opiates, amphetamines, and PCP. Psilocybin and its active metabolite psilocin aren’t on that list, and they never automatically enter it just because a lab is running a “drug test.” Building a test that also flags psilocin costs more and requires a different chemistry setup, so unless someone specifically orders it, it won’t appear.
That’s the core reason so many people search “do shrooms show up on a drug test” and get conflicting answers. The honest answer depends entirely on what kind of test is being run and who ordered it.
Standard immunoassay panels (5-panel, 10-panel): built for common street and prescription drugs, not psilocin. These are the tests used for most employment screening, and psilocybin detection isn’t part of the design.
Here’s how detection windows break down by sample type when a lab does order psilocin-specific testing:
| Sample type | Typical detection window | Notes |
|---|---|---|
| Urine | Around 24 hours | Some anecdotal reports suggest longer windows, but pharmacokinetic evidence supports a detection window generally around one day |
| Blood | Less than a day | Psilocin clears quickly from plasma |
| Saliva | Only several hours | The shortest practical detection window among sample types |
| Hair | Up to 90 days | Rarely used and less reliable for psilocin specifically |
| Nails | Potentially months | Longest theoretical window, but almost never tested in practice |
The hair and nail numbers deserve a caveat. Laboratory studies have detected psilocin in hair samples using LC-MS/MS methods, but the concentrations involved are low and the validation data behind hair testing for mushrooms is thinner than it is for drugs like cocaine or opioids. Most labs won’t build a case on a hair result alone.
How Long Does Psilocybin Stay in Your System?
Psilocybin itself barely exists in the body for long. Once swallowed, it converts almost immediately into psilocin, the compound actually responsible for the psychedelic effects and the one any lab test would need to target.

Psilocin’s elimination half-life runs roughly 2 to 5 hours, and the bulk of what gets excreted in urine shows up within the first 8 to 24 hours after ingestion. That’s a narrow biological window by any standard, far shorter than THC’s, which can linger for weeks in frequent users.
A few things shape how that timeline plays out in practice:
- Single, moderate doses clear fastest, often falling below detectable levels within a day.
- Repeated or heavy use over several days can extend residual traces, though solid data on this pattern is still limited.
- Body composition and liver function affect how quickly any individual metabolizes and excretes psilocin.
- Occasional use doesn’t build up the way chronic use of some other drugs does, since psilocin doesn’t store in fat tissue.
The takeaway is straightforward. Because breakdown happens fast and excretion front-loads into the first day, the practical detection window is genuinely narrow. Someone who takes mushrooms on a Friday night has a very different risk profile than someone testing 12 hours later versus five days later.
When Do Labs Order a Specialized Psilocybin Test?
Nobody accidentally gets tested for shrooms. Psilocin testing requires a deliberate decision by whoever ordered the panel, and that decision tends to show up in a handful of specific contexts.
- Court and probation orders, where a judge or supervising officer has specified psilocin as a monitored substance.
- Forensic investigations, including autopsies or incident-related toxicology where psychedelic use is suspected.
- Clinical toxicology after an emergency room visit, when a patient’s symptoms suggest hallucinogen use and doctors need to confirm it.
- Certain military programs, most notably the Department of Defense, which added psilocin to its drug testing program starting October 1, 2025.
When labs do go looking for psilocin, they rely on LC-MS/MS or GC-MS, mass spectrometry methods that can identify the compound with high specificity. These tests cost significantly more per sample than a standard immunoassay strip, which is exactly why routine employer screening skips them.
Federal policy backs this up directly. The Mandatory Guidelines for Federal Workplace Drug Testing Programs don’t include psilocin among the authorized analytes for routine federal panels. Individual agencies can request biomarker authorization for a specific substance, which is essentially what the DoD did, but that’s an opt-in exception, not the federal default.
What Actually Changes Your Detection Risk?
Two people who took the same dose at the same time can produce completely different results depending on a handful of variables.
- Dose and frequency matter most. A larger dose or repeated use over several days pushes more psilocin through the system and can extend the window slightly.
- Metabolism and physiology, including age, liver function, and body composition, change how fast any individual clears the compound.
- Timing relative to ingestion is the single biggest factor. Testing 6 hours after use versus 36 hours after use produces wildly different odds of a positive result.
- Lab cutoffs and method decide whether anything shows up at all. A screening immunoassay that doesn’t even target psilocin will report negative no matter what’s in the sample, while a confirmatory mass-spec test ordered specifically for psilocin is far more sensitive.
Home “detox” drinks and flushing tricks don’t meaningfully change any of this. Psilocin’s clearance is driven by liver metabolism and kidney excretion on its own biological timeline, not by how much water someone drinks beforehand.
Pro Tip: If you know a specific test date and are worried, timing matters more than any detox product on the market. Understanding how dosing amounts affect how much psilocin enters your system is more useful than any last-minute trick.
Can a Drug Test Give a False Positive for Shrooms?
Cross-reactivity with psilocin on standard panels is uncommon, mostly because those panels aren’t built to look for it in the first place. A false positive specifically attributed to mushrooms is rare in practice, largely because the screening step usually isn’t even chemically capable of flagging it.
The real accuracy question comes down to which stage of testing produced the result.
- Screening immunoassays are fast and cheap but not built to target psilocin on standard panels.
- Confirmatory testing with LC-MS/MS or GC-MS is what labs use when a result needs to hold up legally or clinically, and it identifies psilocin with high specificity.
- A Medical Review Officer (MRO) typically reviews any non-negative result before it becomes official, giving the tested person a chance to explain or contest it.
If you’re ever notified of a positive result tied to psilocybin, ask two direct questions: which analyte triggered the flag, and whether confirmatory mass-spec testing was run. A presumptive screen alone shouldn’t be treated as a final answer.
What Do the Federal Guidelines and Research Say?
The policy and science line up cleanly on this topic, which is part of why the answer to “will I fail a shrooms drug test” is more consistent than people expect.
- Federal workplace testing guidelines set the baseline most private employers follow, and psilocin isn’t part of that authorized panel for routine screening.
- Pharmacokinetic research confirms psilocin’s short half-life and rapid urinary excretion, which is the biological reason detection windows stay narrow.
- The DoD’s 2025 policy expansion shows that individual agencies can and do diverge from the federal default when they have a specific reason to test for it.
Those three facts together explain almost every real-world scenario a reader might face, from a routine pre-employment screen to a military drug panel.
What Should You Actually Do If You’re Worried About a Test?
Three things matter more than anything else here: routine tests won’t catch mushroom use, targeted tests can but only within a short window, and the panel type determines everything. If a test is coming up, find out who ordered it and which analytes it covers. Request confirmatory testing if a result seems wrong, and loop in medical or legal counsel for anything court-related. Testing policy keeps shifting, so what’s true in 2026 may not hold in a few years.
— Alex
Sources
- Federal Register, Volume 91 Issue 49 (Friday, March 13, 2026)
- Pharmacokinetics review (doi:10.1007/s40262-017-0540-6)
- Journal of Analytical Toxicology – screening and confirmation methods (doi:10.1093/jat/bkv067)
If you’re researching psilocybin for reasons beyond drug testing, whether that’s therapeutic interest or simple curiosity about strains and dosing, Fungipsilocybinmushroom carries lab-tested products including dried mushrooms, capsules, and edibles with discreet worldwide shipping. Readers exploring how different consumption methods affect experience and timing might also find the dosing guide useful before making any decisions.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
FAQ
Do Shrooms Show Up on a Standard Workplace Drug Test?
No. Standard 5-panel and 10-panel immunoassay tests don’t screen for psilocybin or psilocin unless an employer specifically orders a specialized panel.
How Long Do Shrooms Stay in Your Urine?
Psilocin is typically detectable in urine for around 24 hours, with some anecdotal reports suggesting longer windows, but pharmacokinetic evidence supports detection generally around one day.
What Test Method Can Actually Detect Psilocybin?
LC-MS/MS and GC-MS are the confirmatory laboratory methods capable of reliably detecting psilocin, but they’re expensive and rarely included in routine employer screening.
Does the Military Test for Psilocybin?
Yes. The Department of Defense added psilocin to its drug testing program starting October 1, 2025, making military testing a notable exception to civilian routine practice.
Can You Get a False Positive for Shrooms on a Drug Test?
It’s uncommon, since most standard panels don’t chemically target psilocin at all. A confirmed positive typically requires a specialized test ordered specifically for that analyte.
Recommended

24–48 Hour Psilocybin Toxicity: Clinical Triage and Lab Tested Safety
Psilocybin has one of the widest safety margins of any psychoactive compound, and lethal poisoning from the drug itself is essentially unheard of in clinical literature. The real hazards are psychological, meaning severe anxiety, disorientation, and behavior that leads to injury, plus the danger of eating a misidentified toxic mushroom instead of a genuine psilocybin species. Effects begin within an hour and usually resolve within a day, and most cases need nothing more than a calm setting and reassurance rather than aggressive medical intervention.
TL;DR:
- Most adverse effects like nausea, headache, and anxiety typically resolve within 24 to 48 hours without medical intervention.
- The primary danger stems from psychological reactions causing disorientation or panic, which may lead to injury if alone or in unsafe environments.
- Psilocybin’s toxicity at the molecular level is very low, with no established lethal dose and animal studies showing no neuronal damage.
- Serious complications are mostly linked to unsafe behavior or misidentification of toxic mushrooms, not the pharmacology of psilocybin itself.
- Using lab-tested products, starting with low doses, and having a sober, familiar sitter significantly reduce the risks associated with recreational use.
Table of Contents
- What Does Psilocybin Toxicity Actually Look Like?
- How Toxic Is Psilocybin at the Molecular Level?
- How Long Do the Effects Last?
- What Should You Do If Someone Is Having a Bad Reaction?
- Who Should Avoid Psilocybin Entirely?
- What Are the Rare but Serious Complications?
- How Can You Reduce the Risk Before You Ever Take a Dose?
- What Resources Help You Assess Product Safety?
- Why Clinical Data and Real-World Use Tell Different Stories
- Choosing Tested Product Over Guesswork
- Where to Learn More
- Sources
- FAQ
What Does Psilocybin Toxicity Actually Look Like?
Most people who take psilocybin experience a predictable cluster of physical effects that would alarm a first-time user but rarely require treatment. Nausea shows up in 4% to 48% of cases depending on dose and setting, headache in 2% to 66%, and anxiety in 4% to 26%, according to a review of emergency visits linked to magic mushroom use. Heart rate and blood pressure tend to climb temporarily, mirroring the body’s general stress response rather than signaling organ damage.
Statistic Callout: Nausea (4–48%), headache (2–66%), and anxiety (4–26%) are the most commonly reported adverse effects, and nearly all resolve within 24 to 48 hours without medical treatment.
The psychological presentation is where things get more variable and, for some users, more frightening. Common findings include:
- Visual and auditory hallucinations, ranging from mild pattern distortion to full perceptual shifts
- Acute anxiety or panic, sometimes escalating into paranoia
- Ego dissolution, a loss of the usual sense of a separate self, which can feel profound or deeply destabilizing depending on preparation and setting
- Confusion or disorientation that impairs judgment about physical safety
- In rare cases, severe agitation bordering on a transient psychotic state
The injury risk rarely comes from the drug’s chemistry. It comes from a disoriented person climbing something, wandering into traffic, or panicking near water. Emergency clinicians see this pattern often enough that trauma, not toxicology, is the more common reason for a psilocybin-related ER visit.
Children and older adults deserve separate attention. A child who accidentally ingests mushrooms can show more pronounced gastrointestinal upset and unpredictable behavioral change relative to body weight, and any pediatric exposure warrants a call to poison control regardless of apparent severity. Older adults, particularly those with existing cardiovascular disease, are more vulnerable to the transient blood pressure and heart rate increases that younger, healthier users tolerate without issue. Red flags that justify emergency evaluation in any age group include chest pain, seizure activity, loss of consciousness, or agitation severe enough to risk harm to the person or others.

How Toxic Is Psilocybin at the Molecular Level?
Psilocybin itself is a prodrug. Once ingested, the body converts it into psilocin, the active compound that binds to serotonin 5-HT2A receptors in the brain and produces the perceptual and mood effects associated with a psychedelic experience. That receptor activity also disrupts the default mode network, the brain circuit tied to self-referential thought, which is part of why users report altered senses of identity and time.
What psilocybin does not do, at typical doses, is threaten vital organs. Reviews of clinical-trial data describe a favorable safety profile with a notably large therapeutic index, indicating a wide margin between effective and harmful doses, though exact ratios vary with factors like purity and individual health.
Neurotoxicity is a separate question from acute overdose, and here the animal data are reassuring rather than alarming. A study mapping brain tissue in rats found no HSP70 expression, a marker of neuronal injury, after psilocybin exposure. In contrast, ketamine and other NMDA receptor antagonists did trigger that marker in the same model. This suggests psilocybin may not cause the neuronal damage seen with some dissociative drugs, though animal findings may not fully predict human safety.
A few structural points explain why psilocybin’s toxicity profile differs so much from what people expect:
- No known lethal dose has been established in human clinical settings, unlike alcohol or opioids
- The compound does not appear to accumulate in tissue or cause cumulative organ stress with typical use patterns
- Clinical trials that screen participants and monitor them closely report low rates of serious adverse events
- The dominant real-world danger is not psilocybin at all: it is misidentifying a toxic wild mushroom as a psilocybin species, which can cause liver failure or death from unrelated toxins
That last point deserves emphasis because it gets lost in casual conversations about “mushroom overdose.” Amatoxin-containing species like Amanita phalloides look nothing like psilocybin mushrooms to a trained mycologist, but to an untrained forager they can be mistaken for one, and cooking or drying does not neutralize the toxins. Deaths attributed to “magic mushrooms” in emergency literature are frequently traced back to this kind of misidentification rather than psilocybin itself.
How Long Do the Effects Last?
Timing follows a fairly consistent arc across users, which is part of why harm-reduction planning works as well as it does. According to guidance from California Poison Control, symptom onset usually occurs within an hour after ingestion, with effects lasting several hours depending on dose and individual metabolism.
The progression generally breaks down like this:
- 0 to 60 minutes: Early autonomic symptoms appear first, including nausea, mild sweating, and a faster heartbeat, sometimes accompanied by a rising sense of anticipation or unease.
- 1 to 3 hours: Peak perceptual effects set in, with visual distortions, altered thought patterns, and emotional intensity reaching their height.
- 3 to 6 hours: The experience gradually levels off, though residual perceptual changes and fatigue can persist.
- 6 to 12 hours: Most acute effects resolve, leaving many users with a lingering sense of mental clarity or, alternatively, exhaustion.
- 24 to 48 hours: Nearly all physical symptoms, including headache and lingering nausea, fully resolve by this point for the large majority of users.
Delayed reactions are uncommon but worth knowing about. A small subset of users report Hallucinogen Persisting Perception Disorder, or HPPD, where visual disturbances like trailing lights or geometric patterns recur weeks or months after the original experience. This appears rare relative to total use, and current evidence does not point to a reliable predictor for who develops it, though prior anxiety disorders and heavy hallucinogen use are frequently discussed as possible risk factors.
What Should You Do If Someone Is Having a Bad Reaction?
The overwhelming majority of adverse psilocybin reactions resolve with environmental management alone, not medication. That single fact changes how a rescuer, sitter, or clinician should approach the situation.
Pro Tip: Before assuming a “bad trip” needs medical intervention, try moving the person to a quiet, dimly lit room with one calm, familiar person present. A change in surroundings resolves the majority of acute panic reactions without any drug intervention at all.
- Create a low-stimulation environment. Dim lighting, reduced noise, and a small number of familiar, calm people work better than a crowded or chaotic space. Remove sharp objects, open flames, or anything the person could trip over or fall from.
- Stay present and speak calmly. Simple, reassuring statements, reminding the person the effects are temporary and drug-induced, help ground someone experiencing anxiety or paranoia. Avoid arguing with hallucinations or dismissing what they’re describing; validate the feeling while gently redirecting attention.
- Monitor vital signs informally. Watch for breathing difficulty, chest pain, or a level of confusion that seems out of proportion to a typical trip. This is where a companion who stayed sober earns their keep.
- Escalate to emergency services when specific red flags appear. These include seizures, loss of consciousness, chest pain, severe agitation that risks injury to the person or others, signs of self-harm, or any airway or breathing compromise. Do not wait to see if it passes.
- In a clinical setting, benzodiazepines are the first-line pharmacologic option for agitation that does not respond to a calm environment. Emergency toxicology references to describe diazepam dosing in the range of 5 to 10 mg IV for adults as a typical starting point, titrated to effect. Midazolam is another option cited in the same guidance.
- Antipsychotics are used cautiously, if at all. Some clinicians reach for sedating antipsychotics in refractory cases, but these carry a risk of lowering seizure threshold and are generally considered second-line behind benzodiazepines.
- Document everything and involve a poison control consult when uncertainty exists, particularly if the substance ingested is not confirmed to be psilocybin, if a child or older adult is involved, or if symptoms seem disproportionate to what psilocybin alone typically causes.
There is no antidote to psilocybin. Every management approach described here is supportive, meaning the goal is to keep the person safe and comfortable while the drug clears the system on its own. If you’re planning ahead of an experience rather than reacting to one already underway, the guide to avoiding a bad mushroom trip covers preparation steps that reduce the odds you’ll ever need this section.
Who Should Avoid Psilocybin Entirely?
Certain histories change the risk calculation enough that psilocybin should be avoided outright or only considered under close clinical supervision. Clinical trial protocols consistently exclude people with schizophrenia, bipolar disorder, and serious cardiovascular disease, and that exclusion criteria reflects real risk, not overcaution.
Statistic Callout: Reviewers behind clinical dosing protocols note that a personal or family history of psychosis, uncontrolled bipolar disorder, or unmanaged serious heart disease are among the most consistently cited exclusion criteria in trial screening.
Key contraindications and interaction concerns include:
- Personal or family history of psychosis or schizophrenia. Psilocybin can trigger or worsen psychotic symptoms in vulnerable individuals, and this risk appears to persist even years after a psychotic episode has resolved.
- Uncontrolled bipolar disorder. The mood-altering effects of psilocybin can potentially destabilize mood cycling in people whose bipolar disorder is not well managed.
- Pregnancy and breastfeeding. There’s no established safety data for fetal or infant exposure, so avoidance is the standard recommendation.
- SSRIs, SNRIs, and other serotonergic medications. Combining these with psilocybin raises a theoretical risk of serotonin syndrome, though published case reports remain scarce. Clinical guidance still recommends careful medication screening and, in supervised settings, a supervised taper before dosing.
- MAOIs and tricyclic antidepressants. These carry a similar theoretical serotonergic risk and are generally treated as a reason for extra caution or avoidance.
- UGT enzyme inhibitors. Psilocin is metabolized in part through UGT1A9 and UGT1A10 pathways. Drugs or substances that inhibit these enzymes could theoretically prolong or intensify psilocin’s effects, an area where research is still developing.
None of this is a one-size-fits-all checklist. A person on a low-dose SSRI with no psychiatric history is in a very different risk category than someone with a first-degree relative who has schizophrenia, and any decision involving current medications should include an honest conversation with a prescribing clinician rather than a guess based on a forum post.
What Are the Rare but Serious Complications?
Severe outcomes from psilocybin exist in the medical literature, but they cluster around indirect causes far more than direct pharmacological toxicity. Case reports and emergency department reviews describe trauma, acute kidney injury, seizures, and cardiac arrhythmia tied to psilocybin use, but these events are consistently linked to unsafe behavior during intoxication, coingested substances, or preexisting undiagnosed conditions rather than psilocybin acting as a direct organ toxin.
The most-discussed long-term concerns break down into two categories:
- HPPD (Hallucinogen Persisting Perception Disorder): Recurring visual disturbances after the drug has fully cleared the body. Current estimates suggest this is rare relative to total psilocybin use, though exact incidence figures are difficult to pin down given inconsistent diagnostic criteria across studies.
- Persistent psychosis risk: Documented mainly in individuals with preexisting vulnerability to psychotic disorders rather than emerging spontaneously in psychiatrically healthy users.
- Reported deaths involving psilocybin are overwhelmingly linked to trauma, coingested substances, or misidentified toxic mushroom species rather than psilocybin toxicity in isolation.
Set against these rare case reports, controlled clinical-trial data tell a more reassuring story. Trials that screen out high-risk participants and monitor dosing sessions closely report few serious adverse events, a gap that highlights how much screening and supervision reduce risk compared to unsupervised recreational use. The takeaway isn’t that psilocybin is risk-free. It’s that the risk profile changes dramatically based on who is taking it, in what setting, and under what supervision.
How Can You Reduce the Risk Before You Ever Take a Dose?
Harm reduction for psilocybin starts long before ingestion, and most serious incidents trace back to a step that got skipped here rather than anything unpredictable about the drug itself.
- Know your source. Lab-tested product removes the biggest variable in psilocybin safety: not knowing what you’re actually taking. Foraging wild mushrooms without expert-level identification skills is where the most severe poisonings originate, not from psilocybin itself.
- Start low and go slow. Conservative dosing, especially for first-time users, reduces the odds of an overwhelming psychological reaction. A structured dosing approach beats guessing based on someone else’s experience.
- Control set and setting. A comfortable, familiar environment and a stable emotional state going in matter as much as the dose itself. A sober sitter who knows the plan and stays present the entire time is one of the single highest-value harm-reduction steps available.
- Skip the alcohol and other substances. Mixing psilocybin with alcohol, stimulants, or other psychoactive drugs increases unpredictability and complicates any emergency response if one becomes necessary.
- Store products securely. Keep mushrooms and edibles clearly labeled and out of reach of children and pets. An unlabeled edible in a shared fridge is a common and entirely preventable source of accidental pediatric exposure.
- Know when to call poison control. If an accidental ingestion happens, especially involving a child, call poison control immediately and be ready to describe what was taken, roughly how much, when it happened, and any symptoms observed so far.
Pro Tip: Photograph any product before consuming it, including packaging and any lab-testing information available. If an adverse reaction happens, that photo gives poison control or an emergency clinician something concrete to work from instead of a vague description.
What Resources Help You Assess Product Safety?
Reducing psilocybin’s risk profile comes down largely to controlling the one variable users can actually manage: knowing exactly what they’re taking. Fungipsilocybinmushroom built its process around that idea, using lab testing to verify potency and screen for contamination before any product reaches a customer.
That approach shows up across a few practical resources:
- Strain-specific information that helps users understand potency differences between varieties, rather than treating “mushrooms” as one uniform product
- Dosing guidance aimed at conservative titration for people new to psilocybin
- Safety pages addressing interactions and precautions beyond the psychotropic medication list covered earlier in this guide
- Background material on how psilocybin compares to other psychedelics people frequently ask about, including DMT and LSD
None of this replaces a conversation with a physician or pharmacist, particularly for anyone managing psychiatric medication or a complex medical history. What it does is close the information gap that leads most people into risky situations in the first place, whether that’s an unverified street product or a dose calculated by guesswork instead of a plan.
Why Clinical Data and Real-World Use Tell Different Stories
The gap between what clinical trials show and what happens in unsupervised settings is the single most misunderstood part of the psilocybin safety conversation. Trials succeed partly because of the drug and partly because of everything wrapped around it: screening out people with psychotic disorders, controlling dose precisely, and having trained staff present for hours. Strip away those safeguards, and the risk profile shifts, not because the pharmacology changed, but because the guardrails did.

That’s not an argument against psilocybin. It’s an argument for treating “set, setting, and screening” as seriously as dose. Anyone with a complicated psychiatric history, a heart condition, or a long medication list owes it to themselves to talk to a clinician before assuming they fall into the low-risk category most safety data describes. The people getting hurt aren’t usually the ones asking these questions ahead of time. They’re the ones who skipped that step entirely.
There’s also an honest gap in the research that deserves more attention than it gets: long-term data on repeated recreational use, outside the structure of a clinical trial, remains thin. Until that gap closes, cautious, informed use, backed by verified product and realistic expectations, is the most defensible position anyone can take.
— Alex
Choosing Tested Product Over Guesswork
Foraging carries the poisoning risk, and unverified street product carries the potency guesswork. An alternative to both is to use lab-tested products for potency and contamination before shipping, discreetly, wherever ordered. That removes the single biggest variable this entire article has been about, not knowing what’s actually in front of you.
For anyone planning a first experience, the smartest place to start isn’t a strain page, it’s the dosing guide, which walks through conservative titration so you’re not calculating a first dose from a stranger’s forum post. From there, browsing tested options like the Amazonian psilocybin mushroom line gives you a verified starting point instead of an unknown one. This is educational and product information, not medical advice. Anyone with a psychiatric history, cardiovascular condition, or current medication concerns should talk to a clinician before deciding anything.
Where to Learn More
A few sources back the clinical claims throughout this guide and are worth bookmarking directly:
- California Poison Control’s psilocybin safety page covers acute management, dosing timelines, and misidentification warnings.
- The PMC review on emergency treatment after magic mushroom use breaks down adverse effect incidence rates in detail.
- PMC’s dosing and administration review outlines clinical screening protocols and contraindications.
- UVA Toxicology’s clinical reference details emergency department management and medication dosing.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
- Adverse experiences resulting in emergency medical treatment after use of magic mushrooms (PMC)
- Magic Mushrooms (Psilocybin) Safety — California Poison Control
- Therapeutic use of psilocybin: Practical considerations for dosing and administration (PMC)
- Psilocybin — UVA Toxicology (PDF)
FAQ
Is Psilocybin Toxic to the Body?
Psilocybin has low direct physical toxicity and a wide margin between an effective and a dangerous dose, with clinical trials reporting few serious organ-related adverse events in screened, supervised settings. The greater risk comes from psychological effects and unsafe behavior during intoxication, not organ damage from the drug itself.
How Long Does Mushroom Toxicity Take to Resolve?
Effects typically begin within 15 to 60 minutes, peak within a few hours, and resolve within 24 to 48 hours for the large majority of users. Symptoms lasting significantly longer, or involving confusion out of proportion to a typical trip, warrant medical evaluation.
What Is Ego Death With Psilocybin?
Ego dissolution describes a temporary loss of the usual sense of a separate self, a common feature of moderate to high psilocybin doses that some users describe as profound and others find deeply distressing. Research suggests it often correlates with positive therapeutic outcomes in supervised clinical settings, but it can trigger severe panic in unsupervised or poorly prepared circumstances.
Is Psilocybin Bad for the Brain?
Preclinical research mapping neuronal injury markers found no evidence of the neurotoxic signal seen with some other drugs like ketamine, suggesting psilocybin doesn’t cause that type of structural brain damage at studied doses. Long-term human data on repeated use outside clinical settings is still limited, so caution and conservative use remain reasonable.
Can You Overdose on Psilocybin?
A fatal overdose from psilocybin alone is exceptionally rare in medical literature, largely because of its wide therapeutic index. Most severe outcomes tied to “mushroom overdose” trace back to misidentified toxic species, coingested substances, or injury during intoxication rather than psilocybin’s own pharmacology.
Recommended
- How to Dose Magic Mushrooms
- How to Avoid a Bad Mushroom Trip: Complete Guide to Safe Psychedelic Experiences 2026
- How Long Does a Magic Mushroom Trip Last? Guide | Where to buy Magic Mushroom | 3.5g Magic Mushroom For Sale
- Understanding MACRO Macrodose Psilocybin Capsules: A Comprehensive Guide to Effects, Safety, and Legal Considerations 2026

4 Quick Field Tests Growers Use to Tell Mycelium From Mold
If what you’re looking at is bright white, dense, and hugging the substrate, it’s almost certainly healthy mycelium. If it’s dull gray, wispy, and climbing up into the air above your growing medium, treat it as cobweb mold until proven otherwise. The fastest way to settle it: watch for a 24 to 48 hour growth burst, or grab a bottle of 3% hydrogen peroxide and spray a test spot.
TL;DR:
- Healthy mycelium grows at 1 to 2 centimeters per day, remains low in the substrate, and has a dense, chalky white appearance.
- Cobweb mold can cover a tub within 24 to 48 hours, lifts above the substrate, and shows a wispy, grayish or dingy white texture.
- Applying hydrogen peroxide or performing a Q-tip test quickly reveals mold by dissolving it or transferring pigment, distinguishing it from healthy mycelium.
- High humidity combined with stagnant air creates ideal conditions for cobweb mold, so proper fresh-air exchange and sanitation are critical for prevention.
- Early detection of contamination, within the first 48 hours, using visual cues or simple tests, greatly improves the chances of salvage or containment.
Table of Contents
- Mycelium vs Mold: The Visual Differences That Matter Most
- How Do You Run a Peroxide or Q-Tip Test?
- Should You Isolate, Salvage, or Discard the Grow?
- What Should Your Grow Room Environment Look Like?
- Where Can You Find Reliable Grow Guidance?
- What Molds and Mycelium Species Actually Show Up in Cultivation?
- How Does Contamination Progress Visually Over Time?
- Does Mold Contamination Actually Hurt Your Yield?
- Can Magnification Help You Confirm What You’re Looking At?
- A Grower’s Take on Staying Calm Through Contamination Scares
- Ready to Start With Cleaner Spawn and Better Odds?
- Sources
- FAQ
Mycelium vs Mold: The Visual Differences That Matter Most
Growers panic first and check facts second, which is backward. The good news is that mycelium and mold rarely look alike once you know what to check, and the differences show up in four places: color, texture, speed, and direction of growth.
Healthy mycelium is bright, opaque white, almost chalky in its density, and it spreads at a fairly modest 1 to 2 centimeters per day. It stays low, colonizing outward through the substrate rather than up into the air. Cobweb mold, by contrast, is grayish or dingy white, thin as spun cotton, and it doesn’t stay put. It lifts 0.5 to 1 inch above the substrate surface and can blanket an entire tub in 24 to 48 hours, a pace healthy mycelium never matches.
Smell is a secondary clue worth trusting. Mycelium usually carries a mild, earthy, almost mushroomy scent. A sour, musty, or chemical odor is a signal something else has moved in, even if the color still looks close to white.
| Feature | Healthy Mycelium | Cobweb / Mold Contaminant |
|---|---|---|
| Color | Bright, opaque white | Gray tinted, dingy, or dull white |
| Texture/density | Dense, ropy, tomentose | Wispy, thread-like, airy |
| Growth speed | About 1 to 2 cm/day | Can cover a tub in 24 to 48 hours |
| Growth direction | Hugs the substrate | Lifts into headspace |
| Smell | Mild, earthy | Sour, musty, or chemical |
| Response to disturbance | Holds shape | Collapses easily |
A few field notes that separate the two at a glance:
- Mycelium appears integrated into the substrate surface, firmly attached.
- Cobweb mold tends to lie loosely on the surface, delicate and easily disturbed.
- Some green molds like Trichoderma can initially appear white before changing color later, so a white patch does not guarantee safety.
- Gently blowing near the patch may cause cobweb mold to wave or collapse, which mycelium does not.
How Do You Run a Peroxide or Q-Tip Test?
You don’t need a lab to get a real answer here. Four checks, done in order of speed and cost, will tell you almost everything you need to know.
- Hydrogen peroxide spray. Mix or use straight 3% hydrogen peroxide from the pharmacy and mist a small amount directly onto the suspicious patch. Cobweb mold visibly melts or dissolves within seconds. Healthy mycelium shows little to no reaction, maybe a slight sheen, nothing more.
- Fan or breath test. A light puff of air or a few seconds under a small fan tells you a lot. Cobweb collapses or waves like a spider web in a breeze. Mycelium holds its structure because it’s actually rooted into the substrate.
- Photo-marking and time-lapse. Circle the suspicious spot with a marker on the outside of the container, snap a photo, and check again in 24 hours. Growth that’s crept well past your mark in a day is growing far faster than mycelium’s normal pace.
Pro Tip: Run the peroxide test on a small corner first, not the whole patch. If it’s mycelium, you’ll want to keep the rest of that colonization intact, not soak it.
Should You Isolate, Salvage, or Discard the Grow?
Containment comes before diagnosis. Move any suspect tub away from your other grows immediately and avoid opening lids or disturbing the surface, since agitation can send spores airborne and cross-contaminate an entire grow room.
Some situations call for an immediate discard, no debate needed:
- Green, black, pink, or powdery patches, especially with visible sporulation
- A strong sour, chemical, or rotten smell coming off the substrate
- Growth that’s doubled or tripled overnight, far outpacing normal colonization
- Contamination that’s spread past 50% of the substrate surface
Early-stage cobweb, caught before it sporulates, sometimes responds to a peroxide spray followed by re-covering and close observation for another day. This works best when the contamination is small and isolated, not when it’s already spread across a wide area. When in doubt, discard the batch and start clean rather than risk your health on a borderline call.
What Should Your Grow Room Environment Look Like?
Cobweb mold thrives in one specific combination: very high humidity paired with stagnant, poorly exchanged air. Fix that combination and most cobweb problems disappear before they start.
Keep relative humidity in the moderate range typical for fruiting, generally high but avoid condensation pooling on surfaces or allowing the substrate to become waterlogged. Standing moisture is basically an invitation. Pair that humidity with real fresh-air exchange, several times a day if you can manage it, so the headspace doesn’t turn into a stagnant, humid box where mold spores settle and germinate uninterrupted.
Sanitation matters just as much as climate. Wipe down tools and work surfaces with isopropyl alcohol before handling substrate, and avoid touching your grow with unwashed hands. Cobweb spores are everywhere in ambient air, waiting for the right conditions.
- Keep humidity high enough to fruit, but never let substrate sit wet or waterlogged.
- Run fresh-air exchange multiple times daily to avoid a stagnant, humid headspace.
- Sanitize tools, hands, and work surfaces before every substrate handling session.
- Take a daily photo of your grow and mark anything suspicious for a 24 hour recheck.
Pro Tip: A small personal fan on low, aimed near but not directly at your grow, does more for fresh-air exchange than most growers expect, and it costs less than a bag of substrate.
Where Can You Find Reliable Grow Guidance?
Good identification skills only get you so far if your setup or spawn was compromised from the start. That’s where sourcing and instructions matter as much as the peroxide bottle in your kit.
- A step-by-step grow kit guide walks through colonization timelines so you know what “normal” looks like before day 10 ever arrives.
- The full cultivation guide covers environmental setup in detail, which is where most contamination problems actually start.
- A troubleshooting FAQ is worth checking before you write off a whole grow as a loss.
Lab-tested spawn matters here too. Contamination that shows up in week one is sometimes traceable back to spawn quality rather than anything the grower did. Starting with tested material removes one entire category of guesswork from the identification process.
What Molds and Mycelium Species Actually Show Up in Cultivation?
Not every contaminant looks or behaves the same, and knowing the usual suspects speeds up your diagnosis. Cobweb mold, caused by species in the Cladobotryum genus, is the one growers run into most often, recognizable by that wispy, gray, cotton-candy texture drifting above the substrate.
Trichoderma species show up as aggressive green mold, though as noted earlier, they can start deceptively white before the color shift kicks in. Penicillium brings the classic blue-green, powdery look, often with a distinct musty smell. Black mold, usually Aspergillus or similar species, is less common on grain or straw but shows up occasionally on overly wet substrate.
On the mycelium side, cultivated species differ visually too. Psilocybe cubensis strains, including popular varieties like Golden Teacher, tend to produce dense, rope-like white mycelium that colonizes fast once established. Some strains run noticeably ropier or more rhizomorphic than others, which is normal strain variation, not a warning sign.
Taxonomically, molds and mushroom-forming fungi often sit in entirely different branches of the fungal kingdom, a distinction the NCBI Taxonomy database catalogs in detail. That’s a useful reminder that “mold vs fungus” isn’t really the right framing. Mold is a fungus. So is mycelium. The real question is always which specific organism you’re looking at.

How Does Contamination Progress Visually Over Time?
Contamination rarely announces itself on day one. It builds in a fairly predictable sequence, and knowing the stages helps you catch problems before they’re unsalvageable.
In the first 24 hours, a contaminant patch usually looks like nothing more than a slightly fuzzy or off-white dot, easy to mistake for normal mycelium pinning. By hour 48, if it’s cobweb, that dot has usually tripled in size and started lifting visibly off the surface. Pigmented molds like Trichoderma or Penicillium tend to hold a whitish appearance through this stage too, which is exactly why the Q-tip and color-tracking checks matter more than a single glance.
By day 3 to 4, color typically resolves. Green, black, or blue-green pigment becomes obvious, and any lingering doubt usually disappears. Cobweb mold, if left alone, can blanket an entire substrate surface in that same window, which is faster than almost any healthy colonization stage.
The takeaway: the earlier you catch a contaminant, visually or through testing, the more options you have. A patch identified at hour 12 is a spot treatment. The same patch ignored until day 4 is usually a total loss.
Does Mold Contamination Actually Hurt Your Yield?
Yes, and often more than growers expect from a small-looking patch. Contamination competes directly with your intended fungus for nutrients and substrate real estate, and it releases metabolites that can slow or stall pinning even in areas that look untouched.
A contaminated tub that isn’t fully discarded often produces a noticeably smaller flush, smaller fruit sizes, and sometimes fruit with off coloring or texture near the contamination site. Mold pressure also raises the risk of secondary contamination during later flushes, since spores from an early cobweb outbreak can linger in your grow space and reappear on subsequent batches if sanitation isn’t tightened up.
The financial and time cost adds up quickly too. Substrate, spawn, and weeks of colonization time all get lost if a tub has to be scrapped, which is exactly why early identification through the peroxide and Q-tip tests pays off. Catching contamination at the pinhead stage, rather than after it’s spread across half the tub, is often the difference between a partial loss and a total one.
Can Magnification Help You Confirm What You’re Looking At?
A basic 30x to 60x jeweler’s loupe or a cheap USB microscope adds a level of confidence the naked eye can’t match, especially for growers who deal with contamination often enough that it’s worth the small investment.
Under magnification, healthy mycelium shows clear, uniform hyphal strands, often described as looking like fine white threads woven tightly together. Cobweb mold, under the same magnification, looks noticeably thinner and more erratic, with hyphae that branch out in a looser, spider-web pattern rather than a dense weave.

Magnification won’t replace the peroxide or Q-tip tests, and it’s not necessary for every grower. But if you’re running multiple grows at once, or if you’ve had recurring contamination issues you can’t quite pin down, a $15 to $20 loupe pays for itself the first time it saves you from tossing a perfectly healthy tub of mycelium.
A Grower’s Take on Staying Calm Through Contamination Scares
Most fuzzy white patches growers panic over turn out to be normal aerial mycelium, not mold. Slow down, check the growth pattern and the fan test, and photograph before deciding anything. A rushed discard costs you a whole grow; a careful 24-hour check rarely costs you anything.
— Alex
Ready to Start With Cleaner Spawn and Better Odds?
Every test in this guide gets easier when you start with lab-tested spawn instead of gambling on unknown sourcing. Some grow kits available on the market go through lab testing before shipping, which can reduce the incidence of mystery patches and allow more colonization time spent growing rather than troubleshooting.
If you’re building your first setup or replacing a contaminated batch, the grow kit and cultivation guide walks through timelines, humidity targets, and troubleshooting steps in order, so you’re not guessing at what “normal” looks like on day 5. Ready to start fresh? Browse the current mushroom and grow kit selection and pick a strain suited to your setup, then follow the guide step by step from spawn to first flush.
Sources
- Cobweb Mold vs. Mycelium – Fungi Academy
- Mushroom Growing Tips — Contamination ID
- Cobweb Mold vs Mycelium: Tell the Difference Fast – MycoMansion
FAQ
Is Mycelium Harmful to Humans?
Healthy, properly identified mycelium from a food-grade or cultivated mushroom species is not harmful to touch or be around. Problems come from actual mold contaminants like Trichoderma or Penicillium, not from mycelium itself.
Is Eating Mycelium Good for You?
Mycelium from edible mushroom species is commonly consumed and forms the basis of several mycelium-based food products, but you should never eat mycelium from a tub that showed any signs of contamination, discoloration, or off odors.
Is Mycelium Mold Toxic?
Mycelium itself isn’t mold and isn’t toxic, but true mold contaminants like Trichoderma or Aspergillus can produce compounds that cause allergic reactions or illness, which is why identification tests matter before you consume anything from a questionable grow.
Is This White Mold or Mycelium?
Run the peroxide test first: a spot that visibly collapses within seconds under 3% hydrogen peroxide is mold, while unaffected white growth that’s dense and hugging the substrate is almost certainly healthy mycelium.
Recommended
- Next Level 100% Mycelium B+ Magic Mushroom Grow Kit Guide
- Grow B+ Mushrooms with 100% Mycelium: Fast Colonization, Massive Flushes, and Rock-Solid Results
- Magic Mushroom Grow Kit FAQ: All Questions & Solutions 2026
- How to Grow Magic Mushrooms at Home: The Secret Method Experts Don’t Want You to Know 2day

60% vs 1.3%: Psilocybin Risks and When Clinical Safety Applies
The biggest danger with psilocybin isn’t a toxic overdose, it’s a bad psychological episode in the wrong setting. Physical toxicity at typical doses is low, but the psychological risks (acute distress, paranoia, and in rare cases a psychotic break) are real, especially for people with a personal or family history of psychosis, severe bipolar disorder, uncontrolled cardiovascular disease, or pregnancy. Supervised clinical use with proper screening cuts serious-event rates far below what recreational, unsupervised use produces.
TL;DR:
- The primary danger from psilocybin is a poorly managed psychological episode, especially for individuals with personal or family histories of psychosis, bipolar disorder, or unmanaged health issues.
- Physical risks at therapeutic doses are minimal, with rare serious events mainly linked to high doses, polysubstance use, or preexisting conditions, and most side effects resolve within two days.
- Misidentified wild mushrooms pose a much greater poison risk than psilocybin itself, and using lab-tested products reduces this danger significantly.
- Most adverse psychological effects, like anxiety or paranoia, are managed in clinical settings, but unsupervised use increases the chance of persistent perceptual disorders like HPPD.
- Pre-screening and harm reduction measures, including thorough health assessment and having a sober support person, considerably lower the risk; skipping these increases the chance of dangerous outcomes.
Table of Contents
- Physical and Physiological Risks of Psilocybin
- Psychological Risks: Distress, Paranoia, Psychosis, and HPPD
- Contraindications and Who Should Not Use Psilocybin
- Drug Interactions and Medical Screening for Psilocybin
- Acute vs. Long-Term Psilocybin Risks: What the Research Actually Shows
- Clinical Supervised Use vs. Recreational, Unsupervised Use
- How to Reduce Psilocybin Risks Before and During Use
- Psilocybin Overdose Symptoms and Emergency Response
- A Straight Answer on Whether Psilocybin Is Worth the Risk
- Sources
- FAQ
Physical and Physiological Risks of Psilocybin
Psilocybin has one of the most forgiving safety profiles among controlled substances when it comes to raw toxicity. Clinical reviews describe a wide therapeutic index, meaning the dose that causes real harm sits far above the dose that produces the psychedelic effect people are actually seeking, based on dosing guidance from clinical protocols. Death from psilocybin toxicity alone is essentially not documented in the therapeutic dosing literature.
That doesn’t mean the body has an easy time of it. A systematic review and meta-analysis of six randomized controlled trials covering 528 participants found psilocybin produced significantly more of the following than placebo or comparator drugs:
- Headache
- Nausea
- Anxiety
- Dizziness
- Elevated blood pressure
Statistic Callout: Nausea occurred at nearly nine times the rate seen in comparison groups (relative risk 8.85), and dizziness came in at nearly six times the comparator rate (relative risk 5.81), according to the JAMA Network Open meta-analysis. Most of these effects resolved within 24 to 48 hours.
Rare case reports describe more serious events, including seizures, rhabdomyolysis, and stress-induced cardiomyopathy, but these show up almost exclusively in uncontrolled settings involving high doses, polysubstance use, or preexisting conditions. They’re outliers, not the expected outcome.
The physical risk that deserves more attention than it usually gets is poisoning from misidentified mushrooms. Foraged fungi that resemble psilocybin species can be lethal, and no amount of drying, cooking, or home processing neutralizes those toxins, according to the California Poison Control System. That’s a completely different hazard from psilocybin itself, but it gets lumped into the same conversation constantly.
Psychological Risks: Distress, Paranoia, Psychosis, and HPPD
Acute psychological distress is the psilocybin risk that shows up most often in both clinical trials and real-world reports. Anxiety during the session, transient paranoia, and periods of intense fear or confusion (sometimes called a “challenging experience”) happen even in monitored settings, where they’re managed with reassurance and a calm environment rather than medication.
The JAMA Network Open meta-analysis found no significant increase in paranoia or transient thought disorder across pooled trial data, which tells you something important: clinical screening removes most of the people who’d be vulnerable to those outcomes before they ever take a dose. People with a personal or family history of psychosis are routinely excluded from trials, so the low reported rates of psychotic reactions in that research don’t tell you much about what happens to someone with that vulnerability who uses psilocybin outside a screened setting.
Hallucinogen persisting perception disorder, or HPPD, is where a lot of confusion sets in. The condition involves ongoing visual disturbances, like halos, trails, or static in the visual field, that persist well after the drug has left the body.
Statistic Callout: Transient visual symptoms after psychedelic use are common, reported by roughly 40% to 60% of users in some surveys. A formally diagnosed case of HPPD, the kind that causes clinical distress or impairment, showed up in only about 1.3% of respondents in a 2023 study.
Risk factors that raise the odds of a rough psychological outcome include:
- High doses without a controlled setting
- Preexisting anxiety disorders or unaddressed trauma
- Using alone or with unfamiliar/untrusted people
- Combining psilocybin with other substances, especially stimulants or alcohol
Contraindications and Who Should Not Use Psilocybin
Some people carry enough risk that psilocybin use, clinical or otherwise, is not appropriate without a serious conversation with a clinician first. The contraindications below are drawn from clinical guidance and institutional screening protocols, not guesswork.
- Personal or family history of schizophrenia or schizoaffective disorder. Psilocybin can precipitate or worsen psychotic symptoms in people with this vulnerability, according to guidance from Memorial Sloan Kettering Cancer Center.
- Active psychosis or a history of psychotic episodes. This is a hard exclusion in essentially every clinical protocol.
- Severe bipolar disorder. Manic or mixed episodes can be triggered or intensified.
- Borderline personality disorder. Emotional dysregulation during the session carries elevated risk.
- Uncontrolled cardiovascular disease or significant arrhythmia. Psilocybin raises blood pressure and heart rate, a real problem for anyone whose cardiac status is not stable.
- Pregnancy and breastfeeding. There’s no safety data supporting use in either case, so it’s excluded categorically.
Anyone with a complex psychiatric or medical history who is still considering psilocybin, clinically or otherwise, should talk to a clinician first rather than assume their situation is “probably fine.”
Drug Interactions and Medical Screening for Psilocybin
Psilocybin’s biggest interaction risk involves serotonin. Combining it with SSRIs, SNRIs, or MAOIs raises a theoretical risk of serotonin syndrome, and some clinical protocols require a supervised taper or washout period before a session, following guidance summarized by Memorial Sloan Kettering.
Lithium is a separate concern. Several treatment protocols exclude patients who’ve taken lithium recently, since case reports link the combination to seizures, based on clinical dosing guidance. Antipsychotic medications raise similar red flags and are typically screened for individually.
There’s also a metabolic angle that rarely gets discussed. Psilocin, the active compound psilocybin converts into, is processed partly through UGT enzymes. Drugs like diclofenac and probenecid can inhibit those enzymes, potentially altering how strongly and how long psilocin’s effects last. This area is still thinly studied, so treat it as a caution rather than a settled rule.
- Full medication list review before any session, clinical or otherwise
- Cardiac history screening
- Suicidality and mental health screening
Pro Tip: If you take any prescription medication, write down the exact name, dose, and last time taken before talking to a clinician about psilocybin. Vague answers like “I’m on an antidepressant” don’t give a screener enough to work with.
Acute vs. Long-Term Psilocybin Risks: What the Research Actually Shows
Short-term trial data is fairly strong. Long-term data is thinner and comes with real caveats worth naming upfront.
| Risk category | Evidence source | Key finding |
|---|---|---|
| Acute adverse effects | Meta-analysis, 6 RCTs, N=528 | Higher headache, nausea, anxiety, dizziness, elevated blood pressure vs. comparators; most resolve in 24 to 48 hours |
| Psychotic-like symptoms | Same meta-analysis | No significant increase in paranoia or transient thought disorder |
| Transient visual symptoms | Survey data | Roughly 40% to 60% of users report some effect |
| Diagnosed HPPD | 2023 study | About 1.3% of respondents |
The JAMA Network Open meta-analysis is strong evidence, but it’s built on trial participants who were screened, prepared, and monitored by trained staff. That’s a very different population than someone taking dried mushrooms at a festival with no clinical support.
Statistic Callout: The gap between transient visual symptoms (up to 60%) and diagnosed HPPD (1.3%) is the single most misunderstood number in psilocybin safety discussions. Most people who notice lingering visual quirks never develop anything close to a clinical disorder.
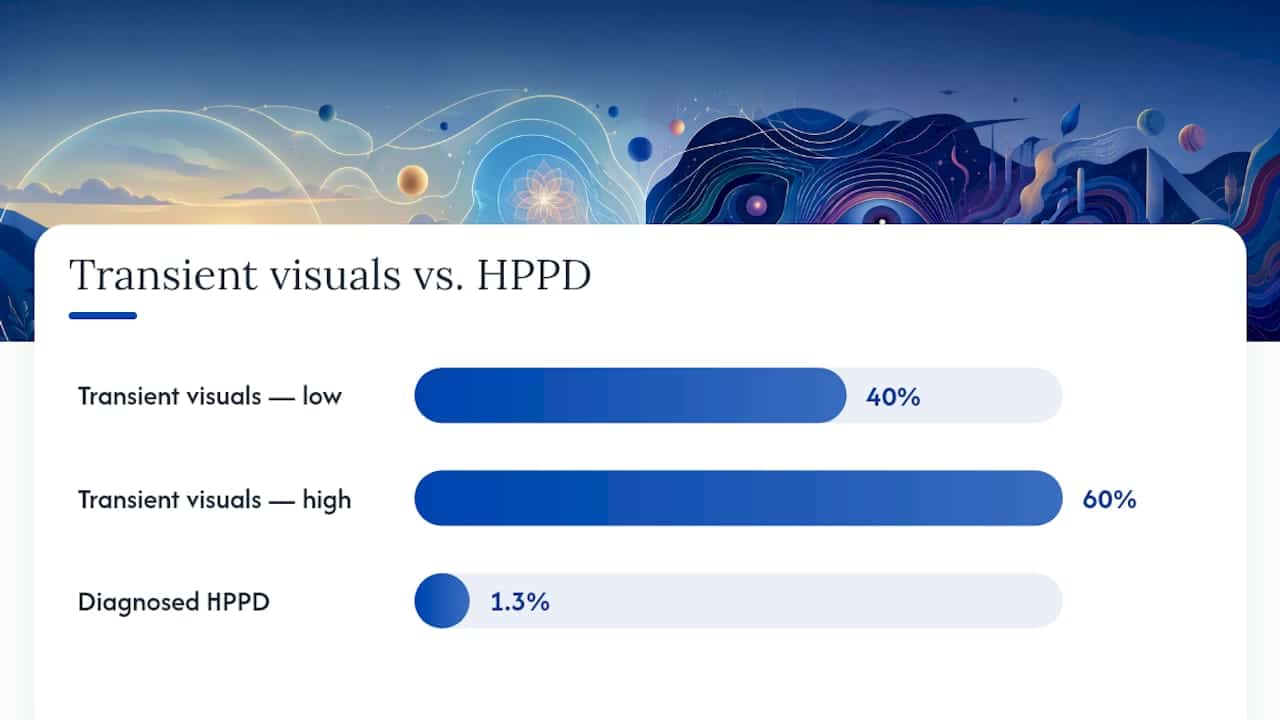
Longer-term harms documented in case series tend to trace back to a small set of contributors: excessive dose, poor set and setting, and preexisting vulnerability that wasn’t screened for. That pattern shows up again and again in the clinical literature.
Clinical Supervised Use vs. Recreational, Unsupervised Use
The difference in outcomes between clinical and recreational psilocybin use isn’t about the drug changing chemically depending on where you take it. It’s about everything surrounding the experience.
Clinical protocols build in preparation sessions before dosing, a trained facilitator present throughout the experience, a controlled and known dose, and structured integration sessions afterward to process what happened. That combination is repeatedly identified as the reason challenging experiences in trials resolve without lasting harm, according to practical clinical guidance on dosing.
Recreational use typically strips out every one of those protections:
- Dose and purity are frequently unknown
- No trained support person is present
- Mixing with alcohol or other substances is common
- There’s no plan for what happens after a difficult experience
Some protective habits from clinical research translate reasonably well to a non-clinical setting, like having a sober, trusted person present, choosing a quiet and familiar environment, and avoiding other substances entirely. But the safety numbers from trials don’t automatically transfer to someone using alone in an unfamiliar setting, and treating them as if they do is one of the more common mistakes people make when researching this. For a broader comparison of how psilocybin’s risk profile stacks up against other psychedelics like LSD and MDMA, it’s worth reading before deciding what “acceptable risk” looks like for you.
How to Reduce Psilocybin Risks Before and During Use
If you’re going to use psilocybin outside a clinical setting, or you’re preparing to ask a clinician the right questions, a handful of steps meaningfully cut your risk.
- Review your health history honestly. Screen yourself against the contraindications above before anything else.
- Check every medication you take, including supplements, for serotonergic or lithium-related interactions.
- Source lab-tested products rather than foraged mushrooms. Misidentification remains one of the most preventable causes of severe poisoning, according to the California Poison Control System.
- Start with a low dose. A dosing guide can help you calibrate a first experience rather than guessing.
- Wait out the full effect before considering more. Redosing too early is a common cause of overwhelming experiences.
- Have a sober, trusted person nearby, not necessarily guiding you, but present and calm.
- Plan for integration. Even a short conversation with someone you trust the next day helps process a difficult session.
Pro Tip: If any contraindication on this list applies to you, a supervised clinical program is a meaningfully safer route than self-administered use. Screening exists precisely to catch the risk factors you might not think to flag yourself.
Psilocybin Overdose Symptoms and Emergency Response
Most psilocybin sessions, even difficult ones, don’t require emergency intervention. But some signs mean it’s time to call for help immediately:
- Chest pain, irregular heartbeat, or signs of a cardiac event
- Seizure activity
- Loss of consciousness or unresponsiveness
- Severe, unrelenting panic that isn’t responding to reassurance
- Any symptom that could indicate poisoning from a misidentified mushroom (vomiting, severe abdominal pain, jaundice appearing hours after ingestion)
Keep the person safe from physical harm, speak calmly, and avoid leaving them alone. When you call emergency services or poison control, have this ready: what was taken, roughly how much, when it was ingested, and any medications or medical conditions involved. Emergency staff typically respond with cardiac monitoring, calming medication if agitation is severe, and testing to rule out actual poisoning rather than a psychological reaction.
A Straight Answer on Whether Psilocybin Is Worth the Risk
People want a clean yes-or-no answer on psilocybin safety, and the honest response is that the question is incomplete without asking “safe for whom, and in what setting.” The data genuinely supports a favorable physiological safety profile at researched doses. What it doesn’t support is the leap so many recreational users make: assuming that because clinical trials look safe, their unscreened, unsupervised experience will look the same.
The number that should actually change how people think about this is the gap between 60% and 1.3%, transient visual effects versus diagnosed HPPD. Most of the fear around lasting psychological damage traces back to a small number of cases, usually involving people who had risk factors nobody checked for beforehand. That’s not a reason to dismiss the risk. It’s a reason to take screening seriously instead of treating it as a formality.
If there’s one place conventional wisdom gets it backward, it’s the assumption that “natural” means low-risk. A compound can have a wide margin of physiological safety and still be genuinely dangerous for the wrong person in the wrong setting. Both things are true at once, and pretending otherwise does readers no favors.
— Alex
Sources
The clinical claims here rely on a small set of higher-quality sources rather than general internet consensus. The JAMA Network Open meta-analysis supplied acute adverse event rates across six randomized trials. The PMC clinical dosing guidance and Memorial Sloan Kettering’s psilocybin overview informed contraindications and screening protocols. The 2023 HPPD prevalence study grounded the perceptual-disorder figures, and the California Poison Control System informed the poisoning and misidentification guidance.
Fungipsilocybinmushroom’s own dosing guide and product pages, including its selection of therapy-oriented mushroom strains, reflect the same harm-reduction principles covered above, with lab-tested products intended to remove the misidentification risk entirely.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
- Acute Adverse Effects of Therapeutic Doses of Psilocybin: A Systematic Review and Meta-Analysis | JAMA Network Open
- Therapeutic use of psilocybin: Practical considerations for dosing and administration – PMC
- Psilocybin | Memorial Sloan Kettering Cancer Center
- Prevalence and correlates of hallucinogen-persisting perception disorder following classic psychedelic use (2023)
- Magic Mushrooms (Psilocybin) Safety | California Poison Control System
FAQ
How Risky Is Psilocybin, Really?
Physiologically, the risk is low at researched doses, with no documented lethal toxicity in clinical trials. The real risk sits in the psychological domain: acute distress, and for vulnerable individuals, the chance of triggering a psychotic episode.
Who Shouldn’t Use Psilocybin?
People with a personal or family history of schizophrenia, active psychosis, severe bipolar disorder, or borderline personality disorder should avoid it, along with anyone with uncontrolled cardiovascular disease or who is pregnant or breastfeeding, per guidance from Memorial Sloan Kettering.
Is Psilocybin Hard on the Liver?
Psilocybin isn’t flagged in clinical literature as a significant liver toxin at studied doses, and reviews of therapeutic dosing note a wide safety margin rather than organ toxicity concerns. The bigger physical risks documented in trials are cardiovascular (elevated blood pressure) and gastrointestinal (nausea), not hepatic.
Is Psilocybin Less Harmful Than Alcohol?
Direct head-to-head risk comparisons weren’t part of the clinical trial data reviewed here, but psilocybin’s favorable therapeutic index and lack of documented lethal overdose stand in contrast to alcohol’s well-established toxicity and dependence risks. That said, psilocybin carries its own distinct psychological risks that alcohol does not, so “less harmful” depends heavily on which harm category you’re weighing.
What Is HPPD and How Common Is It?
HPPD is a condition involving persistent visual disturbances after psychedelic use. Formal diagnosis is uncommon, affecting about 1.3% of respondents in a 2023 study, even though transient visual symptoms are reported by a much larger share of users.
Recommended
- How to Dose Magic Mushrooms
- Understanding MACRO Macrodose Psilocybin Capsules: A Comprehensive Guide to Effects, Safety, and Legal Considerations
- Microdosing Psychedelics: Unveiling Remarkable Health Benefits and Therapeutic Potential
- Psilocybin Depression Treatment California: Your Complete Guide to Legal Mushroom Delivery Services and Therapeutic Options

Peyote Legality in the US: Native Exemption, Texas Sales, Conservation
Peyote is a Schedule I controlled substance under federal law, which technically makes possession illegal for everyone. But 42 U.S.C. §1996a carves out a narrow exception: an Indian using or possessing peyote for bona fide traditional ceremonial purposes cannot be prosecuted under federal or state law for that specific use. Cultivation and sale to the general public remain illegal almost everywhere, and state law adds another layer of variation on top of the federal baseline.
TL;DR:
- Peyote possession by Native Americans for traditional ceremonies is protected only if their practice predates the 1994 law and involves bona fide religious purposes.
- Cultivation, sale, or transport of peyote outside specific licensed systems, especially for non-ceremonial or commercial purposes, remains illegal across all states.
- Texas stands out as the only state where selling peyote legally occurs through a regulated distribution chain, primarily serving verified Native American Church members.
- Most states criminalize planting, harvesting, drying, or processing peyote, with penalties varying from misdemeanors to felonies, especially in California.
- Alternatives like lab-grown psilocybin mushrooms or legal research compounds are available for those interested in psychedelic use without risking federal or state laws.
Peyote Legality Under Federal Law: The CSA and the Indian Exemption
Mescaline, the psychoactive compound in peyote, sits on Schedule I of the Controlled Substances Act, the same category as heroin and LSD. The DEA’s Orange Book lists mescaline and peyote-related substances there, meaning federal law presumes the plant has no accepted medical use and a high potential for abuse. That presumption drives every enforcement decision at the federal level, and it’s the reason peyote legality confuses so many people: the plant is simultaneously illegal and, for a specific group of people, legally protected.
The protection comes from a single, carefully worded statute: Congress passed 42 U.S.C. §1996a in 1994 specifically to settle a legal fight that had been dragging through the courts for years. The operative language states that the use, possession, or transportation of peyote by an Indian for bona fide traditional ceremonial purposes in connection with the practice of a traditional Indian religion is lawful, and shall not be prohibited by the United States or any state. That’s the entire exemption. It doesn’t legalize peyote outright. It protects a specific act, by a specific population, tied to a specific religious practice.
The DEA’s implementing regulation, 21 C.F.R. §1307.31, formalizes this by exempting the Native American Church and its members from prosecution for peyote used in bona fide religious ceremonies. A Department of Justice Office of Legal Counsel opinion goes further, clarifying just how tightly the exemption is drawn. According to the DOJ’s own analysis, the exemption was built around the Native American Church and religions with a comparable, documented history of peyote use. It was never intended as a blanket religious freedom pass for any group that adopts peyote ceremonies.
Pro Tip: If you’re trying to figure out whether a religious group’s peyote use is federally protected, ask whether that specific tradition has a documented history predating the statute. Newly formed groups claiming the exemption face a much steeper legal hurdle than the Native American Church does.
Here’s what the exemption does not cover, and this is where a lot of confusion sets in:
- General manufacturing or commercial distribution of peyote to the public
- Possession by non-Indians, even in a genuine spiritual context, absent a separate legal basis
- Cultivation for sale, gifting, or non-ceremonial personal use
- Transport across state lines for any purpose other than the protected ceremonial use
- Use by Indian individuals outside the context of a bona fide traditional religious ceremony
The legislative history behind §1996a, preserved in the U.S. Code’s preliminary text, shows Congress meant to protect traditional religious practice while still allowing reasonable regulation of how peyote gets grown, harvested, and moved. That balancing act is why cultivation and sale laws exist even in a country that has technically legalized ceremonial possession for one group. The exemption protects the ceremony. It does not protect the supply chain, except through one specific state mechanism discussed below.
Where Peyote Is Legal: State Laws, Texas, and Tribal Lands
Federal law sets the floor, but states decide how much further to go, and the differences are significant. Some states mirror the federal religious exemption almost word for word in their own controlled substances codes, explicitly protecting Native American Church members. Others say nothing about peyote at all beyond listing it as a controlled substance, which leaves practitioners relying entirely on federal preemption if state authorities ever push back. A handful of states have language broad enough to create real ambiguity about how local prosecutors would actually handle a ceremonial possession case.
Texas stands apart from every other state in one specific way: it’s the only place where selling peyote is legal, through a licensed and regulated distribution chain. Reporting from KUT Public Media documents how a small number of registered “peyoteros” in South Texas hold state licenses to harvest wild peyote and sell it to verified Native American Church members. This isn’t an open market. Buyers typically need to demonstrate tribal enrollment or documented NAC membership, and the whole system exists because South Texas happens to sit on top of most of the peyote habitat remaining in the country.
California takes the opposite approach on cultivation. California Health & Safety Code §11363 makes it a crime to plant, cultivate, harvest, dry, or process any plant of the genus Lophophora, which includes peyote, with no carve-out for personal or religious cultivation by non-tribal members. The federal exemption still applies to bona fide ceremonial possession for Indians even in California, but growing your own plant is a separate offense under state law regardless of intent.
Tribal lands complicate the picture further. Enforcement on reservations often falls under tribal law and, in some cases, federal jurisdiction rather than state authority, which can change how a ceremonial use case gets handled entirely. That doesn’t mean cultivation becomes automatically permissible on tribal land. It means the enforcing authority and applicable code may differ from the surrounding state.
| Jurisdiction type | Ceremonial possession by Indians | Cultivation | Sale/distribution |
|---|---|---|---|
| Federal baseline | Protected under §1996a | Not addressed by the exemption | Generally illegal |
| Texas | Protected, supported by licensing | Wild harvest only, by licensed peyoteros | Legal through registered sellers to verified NAC members |
| California | Protected by federal law | Explicitly criminalized under HSC §11363 | Illegal |
| Most other states | Varies by state code language | Generally illegal or unaddressed | Generally illegal |
State statutes change, and legislatures amend controlled substances schedules more often than most people realize. Treat any state-specific summary, including this one, as a starting point for your own search of the current code rather than a final answer.
What Conduct Gets Prosecuted: Cultivation, Sale, and Possession Explained
Peyote statutes generally target a specific sequence of acts rather than the plant’s mere existence. California’s §11363 spells this out clearly by naming five distinct actions as criminal: planting, cultivating, harvesting, drying, and processing. Each one can be charged separately, and prosecutors don’t need to prove intent to sell for a cultivation charge to stick.
- Planting or cultivating the plant, even for ornamental or personal spiritual reasons, triggers criminal liability in states like California regardless of whether you ever harvest it.
- Harvesting wild or cultivated peyote is treated as its own act under statutes modeled on California’s approach, separate from cultivation.
- Drying and processing the harvested plant into a usable form adds additional exposure, since these steps show intent to prepare the substance for consumption or distribution.
- Distribution or sale to anyone outside a licensed, verified channel is illegal in every state except Texas’s narrow registered system.
- Simple possession of prepared or dried peyote by a non-exempt individual is prosecuted differently than cultivation. Enforcement tends to focus more heavily on cultivation and distribution, since those acts touch supply rather than a single act of ceremonial use.
California’s cultivation offense is a “wobbler,” meaning prosecutors can charge it as either a misdemeanor or a felony depending on the circumstances, the defendant’s history, and the quantity involved. A misdemeanor conviction can carry county jail time and fines, while felony charges expose a defendant to state prison. That flexibility gives prosecutors significant discretion, which is exactly why cultivation cases are riskier to predict than straightforward possession cases.
One area that trips people up: seeds and small ornamental plants sold as botanical curiosities occupy a legal gray zone in some states, since a dormant seed isn’t the same as a prepared, consumable substance. That distinction doesn’t hold up everywhere, and several states treat the living plant itself, not just processed material, as the controlled substance. Anyone considering purchasing peyote seeds or buying a peyote cactus for collection needs to check their specific state code before assuming an ornamental sale is automatically lawful.
How Native Americans Access Peyote Legally, and What Non-Native Practitioners Face
For Native American Church members, lawful access runs almost entirely through two channels: NAC chapters that organize ceremonies and coordinate supply, and the licensed Texas peyoteros who sell to verified members under state registration. This system works because it keeps the entire chain, harvest, sale, and ceremonial use, inside a documented, bona fide religious context. Break that chain (buy from an unlicensed source, use outside a ceremony, resell to a non-member) and the federal protection no longer applies.
Non-Native individuals face a much harder legal path. Court decisions including Employment Division v. Smith and Gonzales v. O Centro Espírita Beneficente União do Vegetal shape how far religious freedom claims can stretch for substances outside the specific §1996a exemption. The DOJ’s OLC opinion discusses this history directly, and the upshot is sobering: RFRA claims have succeeded for other substances in narrow cases, but peyote’s exemption remains statutorily tied to Indian religious practice in a way that’s difficult for other groups to access through litigation.
Practical, lawful alternatives exist for people drawn to the broader tradition without qualifying for the exemption:
- San Pedro cactus, which contains mescaline but occupies different legal territory in most U.S. states since the plant itself isn’t scheduled
- Synthetic mescaline, available only through narrow research or clinical contexts, never as a consumer product
- Ceremonial retreats held in countries with different legal frameworks around mescaline-containing plants, though travelers need to research the destination country’s actual law rather than assume tolerance equals legality
Pro Tip: San Pedro’s legal status hinges on the plant being unscheduled, not on any exemption. Confirm your specific state hasn’t separately scheduled the plant before assuming that distinction protects you.
Enforcement Trends and Why Psychedelic Reform Rarely Includes Peyote
Federal prosecutors focus resources overwhelmingly on distribution and cultivation cases rather than ceremonial possession by verified Indian practitioners, since the latter carries almost no prosecutorial upside given the statutory exemption. States generally follow that same pattern, though enforcement intensity against unlicensed cultivation varies a lot by jurisdiction and by how aggressively local prosecutors treat wobbler offenses.
The bigger trend worth understanding: the wave of psychedelic decriminalization sweeping through states in recent years has largely carved peyote out entirely. Oregon’s psilocybin services program and Colorado’s Natural Medicine Health Act both focus on other substances, and explainers tracking these reforms note that peyote is routinely excluded from the plants and fungi covered by decriminalization measures. That exclusion isn’t an oversight. Tribal advocacy groups have pushed specifically to keep peyote out of broader reform, worried that expanded legal access would accelerate demand on an already strained wild supply.
A few points worth remembering:
- Tribal nations, including the Navajo Nation, have taken active conservation positions on peyote harvest, separate from any state or federal drug policy debate
- Broader psychedelic reform measures at the state level almost never extend legal access to peyote, even when they legalize psilocybin or other substances
- The practical outcome for readers: don’t assume a state’s psilocybin decriminalization law says anything at all about peyote’s legal status there
How to Verify Peyote’s Legal Status Before You Act
Getting this wrong carries real criminal exposure, so treat verification as a real step, not a formality.
- Pull the current text of your state’s controlled substances code directly from your state legislature’s official website, and note the statute number and its last amendment date. Secondhand summaries, including this one, can lag behind actual amendments.
- Cross-check the federal statute and DEA regulation. Read 42 U.S.C. §1996a and the DEA’s Schedule I listing directly rather than relying on paraphrases, since the exact wording determines what conduct is actually protected.
- Contact your state attorney general’s office if the statutory language is ambiguous about how cultivation, possession, or religious exemptions apply in your situation.
- If you’re claiming the religious exemption, consult NAC leadership or tribal religious authorities first. They can speak to whether your specific practice and community meet the “bona fide traditional ceremonial purposes” standard the statute requires.
- Retain counsel experienced in tribal and federal drug law before taking any action involving cultivation, transport, or distribution, even in a religious context.
Pro Tip: Never start cultivating, transporting, or supplying peyote based on an assumption about your legal standing. Get explicit clearance in writing from counsel or a tribal authority first. The wobbler penalties in states like California make guessing an expensive mistake.
Until you’ve done that homework, treat cultivation and sale as closed doors. That’s the safest working assumption for anyone outside a licensed Texas peyotero or a documented NAC ceremonial chain.
The Conservation Problem Behind Peyote’s Legal Restrictions
Peyote grows slower than almost any other cactus harvested for consumption, often taking a decade or more to mature. That biology is a big part of why cultivation and unauthorized harvest carry criminal penalties in states like California: unregulated demand can outpace the plant’s ability to regenerate in the wild, and South Texas habitat, the primary wild source supplying licensed peyoteros, has already shown signs of strain from overharvesting.
Native communities, particularly the Native American Church, view peyote as sacred rather than recreational, and many tribal leaders have spoken out against commercial exploitation or casual use by outsiders as a threat to both the plant’s survival and the integrity of the ceremony itself.
Tribal advocacy around peyote conservation isn’t about restricting access for its own sake. It reflects a concern that expanded non-ceremonial demand could permanently damage the wild populations that Native American Church practitioners depend on for a practice with no substitute material.
If you’re drawn to this plant’s history or its chemistry, the more responsible path runs through legal, ceremonial channels or through legal alternatives that don’t pressure an already limited wild supply. Fungi Psilocybin Mushroom’s broader guide to psychedelic legal frameworks covers how peyote’s legal treatment compares with psilocybin, which faces a very different regulatory trajectory in the U.S. right now.
- Peyote’s slow growth cycle limits how fast supply can recover from overharvesting
- The Native American Church and other tribal voices have actively opposed commercial or casual peyote use by non-practitioners
- Legal plant alternatives and research contexts exist for people who want to explore mescaline’s effects without pressuring wild peyote populations
What I’d Tell a Friend Asking About This
The gap between what people assume about peyote legality and what the statute actually says is enormous, and it’s not a small technicality. People hear “Native Americans can legally use peyote” and assume that means peyote is basically legal with an asterisk. It’s the reverse. Peyote is federally illegal with one extremely narrow, carefully bounded exception, and everything else, cultivation, sale, non-ceremonial possession, use by non-exempt individuals, remains squarely illegal in nearly every state.
What actually surprises most readers is Texas. A state famous for strict drug enforcement runs the only legal peyote sales chain in the country, purely because it happens to sit on the habitat and built a licensing system around supplying the Native American Church responsibly. That’s not a loophole. It’s a deliberate regulatory compromise that took decades to build, and it’s fragile precisely because the wild supply it depends on is shrinking.
If there’s one thing worth internalizing here, it’s that peyote’s legal story is really a conservation story wearing a drug-law costume. The restrictions on cultivation exist as much to protect a slow-growing plant from disappearing as they do to control a Schedule I substance. Treat that distinction seriously before treating peyote like just another substance with a legal gray area to exploit. Check your statute. Talk to a tribal authority or attorney if you have any real claim to the exemption. Do not guess.
— Alex
Legal, Lab Tested Alternatives Worth Exploring
Peyote’s legal path is narrow by design, and this article doesn’t encourage anyone around that. Instead, lawful, transparent alternatives exist for people interested in psychedelic exploration without the criminal exposure that comes with unauthorized peyote cultivation or purchase: lab-tested psilocybin mushrooms, grow kits, and microdosing products shipped with discreet, secure delivery.
If therapeutic use is what drew you to this topic in the first place, a guide to psilocybin’s legal therapeutic landscape in California walks through where mushroom-based options currently stand under state law, including delivery services built around compliance rather than guesswork. Lab testing behind products ensures you know what you’re getting before it arrives. Browse current selections and see which lawful option fits what you’re actually looking for.
This article is general information, not a substitute for advice from a qualified lawyer. Consult a qualified legal professional about your own circumstances before acting on anything here.
Sources
- 42 U.S.C. § 1996a — LII / Legal Information Institute
- Department of Justice — Peyote exemption (OLC opinion)
- California Health & Safety Code §11363 — California Legislative Information
- KUT Public Media — In the only state where selling peyote is legal, the cactus is threatened and still controversial
- DEA — Controlled Substances Alphabetical List (Orange Book)
Recommended

72 Hour Rescue Checklist for Growers: Trichoderma Contamination
If you see white fluff turning bright green with a faint coconut smell, that’s almost certainly Trichoderma contamination. Never open a sporulating bag or bin indoors without a mask and gloves.
TL;DR:
- Trichoderma initially appears as dense, white mycelium that quickly turns green and sporulates within 24 to 48 hours, often starting at bag seams or ports.
- The fungus feeds on mushroom mycelium by secreting enzymes that break down its cell walls, making it highly destructive once established.
- Early signs include a coconut or sweet moldy smell and rapid growth, which can be confirmed by specific tests like smell, stickiness, or growth rate.
- Rescue is only possible if contamination is surface-level and caught quickly; otherwise, disposal and thorough decontamination are necessary to prevent spread.
- Prevention relies on using vigorous, lab-tested spawn, proper sterilization, pH control, and strict hygiene to give mycelium a competitive advantage over Trichoderma spores.
Table of Contents
- What Does Trichoderma Contamination Look Like?
- Why Does Trichoderma Spread So Fast and Damage Mycelium?
- Should You Rescue or Discard a Contaminated Grow?
- How Do You Prevent Trichoderma Contamination in the First Place?
- How Do You Decontaminate a Grow Room After an Outbreak?
- Is Trichoderma Contamination a Health Risk to People?
- Is Trichoderma Really That Different From Other Contaminants?
- Want a Lower-Risk Way to Start Your Next Grow?
- Where Can You Learn More About Trichoderma Contamination?
- Sources
What Does Trichoderma Contamination Look Like?
Trichoderma starts out looking almost innocent. It emerges as a patch of dense, white mycelium that could pass for healthy growth, which is exactly why so many growers miss the window to act. Within 24 to 48 hours, that white patch develops a yellowish tinge, then blooms into a distinct forest or emerald green as it sporulates. By the time you see solid green, the fungus has already been feeding for a day or two.

The texture gives it away faster than color sometimes does. Trichoderma mycelium grows tighter and more compact than the fluffy, rope-like strands of healthy oyster or Psilocybe mycelium. It often appears in concentric rings radiating outward from a single point of entry, almost like a target pattern pressed into the substrate.
Location matters too. Trichoderma tends to show up first at bag seams, injection ports, the edges of a monotub, or anywhere air exchange creates a gap in humidity control. These are the exact spots where spores from the room’s air have the easiest entry.
The scent is the most reliable early warning most growers overlook. Trichoderma produces a compound called 6‑PAP that smells distinctly like coconut or sometimes sweet, moldy hay, according to ShroomCraft Lab’s diagnostic guide. If you catch that coconut note before any green is visible, you’re looking at contamination in its earliest, most treatable stage.
A few quick checks help you confirm what you’re looking at before you panic:
- Smell test: Crack the lid or bag briefly and sniff for a coconut or sour, musty note rather than the neutral, earthy smell of healthy mycelium.
- Q-tip test: Lightly press a cotton swab into a suspicious patch. Trichoderma tends to release a faint green dust or leave a slightly slimy residue; clean white mycelium usually doesn’t.
- Light angle check: Tilt the container under a lamp. Healthy mycelium looks matte and fibrous; early Trichoderma often has a slightly wetter, denser sheen before it greens up.
- Growth speed: If a patch doubled in size overnight, that pace is far more typical of Trichoderma than of your intended mushroom species.
False positives happen constantly with beginners. Rhizomorphic mycelium, some cobweb mold (which stays gray and fuzzy, not green), and even certain lighting can trick a new grower’s eye. Cobweb mold grows loosely and collapses when touched; Trichoderma stays dense and doesn’t wilt. When you genuinely can’t tell, isolate the container and send a sample for lab identification rather than guessing.
Pro Tip: Keep a small notebook or phone log of when you first noticed any unusual patch. Trichoderma’s speed is one of its biggest tells, and knowing exactly how many hours passed between “looks fine” and “looks green” helps you and any lab confirm the diagnosis faster.
Why Does Trichoderma Spread So Fast and Damage Mycelium?
Trichoderma isn’t just a mold competing for space. It’s a mycoparasite, meaning it actively hunts down and digests other fungi, including the mushroom mycelium you’re trying to grow. It does this by secreting chitinases and glucanases, enzymes that break down the cell walls of competing hyphae, according to research on invasive Trichoderma infections. Once those enzymes go to work, your mushroom mycelium doesn’t just get crowded out. It gets eaten.
Spore ubiquity makes this worse. Trichoderma spores are practically everywhere: in soil, compost, wood chips, and floating in ambient air. A single overlooked crack in a fruiting chamber’s seal is often all it takes for spores to land and germinate.
Historical outbreaks in Pennsylvania mushroom houses caused crop losses ranging from 30% to 100% in affected growing rooms, largely traced back to contaminated personnel, tools, and rooms that weren’t steamed thoroughly enough between crops, according to Penn State Extension. That range alone tells you how unforgiving this contaminant can be once it establishes itself at scale.
Not all Trichoderma species behave the same way. Some strains are aggressive colonizers that tear through a substrate within days, while others move more slowly and stay localized longer. Warm temperatures, high humidity, excess nitrogen in the substrate, and a pH drifting toward neutral all favor Trichoderma over your intended mushroom species. That’s the environmental sweet spot you’re trying to avoid creating in the first place, and it’s exactly why the prevention steps below focus so heavily on humidity, nitrogen, and pH control rather than treating contamination as pure bad luck.

Should You Rescue or Discard a Contaminated Grow?
The decision comes down to how far the contamination has spread and whether it’s still confined to the surface. Don’t negotiate with substrate that’s contaminated internally. It isn’t salvageable and trying to save it usually just spreads spores around your grow space.
If you’re in rescue territory, work through this sequence:
- Isolate the container immediately. Move it away from other active grows, ideally to a separate room or at minimum a closed container.
- Put on PPE before opening anything. A properly fitted respirator (not just a paper mask), nitrile gloves, and eye protection matter here. Trichoderma spores are a genuine respiratory irritant, and some species carry real infection risk, particularly for people with compromised immune systems, per the Journal of Antimicrobial Chemotherapy’s clinical review.
- Excise the patch with a generous margin. Cut out the visible contamination plus at least an inch of surrounding substrate that looks clean. Use a sterilized blade for each cut and don’t reuse it on healthy areas afterward.
- Treat the cut edges. A 3% hydrogen peroxide solution dabbed directly onto exposed cut surfaces, sometimes combined with a light dusting of table salt, works as an early-stage spot treatment, according to ShroomCraft Lab’s field guidance. Skip bleach on active porous substrate; it’s too harsh and can damage the mycelium you’re trying to save.
- Move the container to a rescue chamber. This should be a separate, lower-humidity space with stronger fresh air exchange (FAE) than your main setup, giving your mushroom mycelium a fighting chance to outcompete any remaining spores.
- Watch daily for 72 hours. Any return of green growth means the rescue failed. Discard immediately rather than trying a second round.
If you’re past the rescue threshold, disposal is about containment, not conservation:
- Double bag the contaminated substrate before it leaves the grow room, sealing each bag before moving it.
- Dispose of it outdoors in regular trash. Don’t add it to a home compost pile unless that pile reliably sustains internal temperatures above 160°F, which most backyard setups don’t.
- Disinfect every tool and surface the contaminated material touched, including the outside of gloves before you remove them.
- Wash your hands thoroughly and change clothes if you were in close contact with a sporulating patch.
Pro Tip: Never shake, blow on, or vacuum a green, sporulating patch. Any of those actions aerosolizes millions of spores into your air, which is the single fastest way to seed contamination into every other grow in the room.
How Do You Prevent Trichoderma Contamination in the First Place?
Prevention beats rescue every time, and it starts before you ever inoculate a substrate. Extension specialists are blunt about this: total elimination of Trichoderma from your environment is not realistic, since spores are essentially everywhere. The real goal is giving your mushroom mycelium such a strong head start that Trichoderma never gets a foothold, an approach Penn State Extension frames as out-competing rather than eliminating the contaminant.
A handful of practices make the biggest difference:
- Start with fresh, lab-tested spawn. Vigorous spawn colonizes faster, and speed is your best defense since Trichoderma needs time and an open niche to establish itself.
- Match your sterilization method to your substrate. Pressure sterilization at 15 PSI for roughly 90 minutes is the standard for nutrient-rich, bran-amended substrates, according to guidance from the AHDB knowledge library on managing Trichoderma in commercial mushroom production. For lower-nutrient lignocellulosic materials like straw or sawdust, hot-water immersion at moderate temperatures for extended periods or immersion in alkalinized water have been shown in controlled experiments to reduce Trichoderma growth, offering gentler alternatives to full sterilization.
- Don’t over-sterilize and then re-expose. Sterilized substrate that gets re-inoculated with even trace Trichoderma can actually favor the contaminant, because sterilization wipes out the competing microflora that would normally help keep it in check, a finding documented in research on lignicolous mushroom cultivation.
- Watch your nitrogen levels. Excess nitrogen supplementation shifts your carbon-to-nitrogen ratio in a direction Trichoderma exploits. Balance is more protective than piling on extra nutrients.
- Buffer your casing layer with hydrated lime. Raising casing pH above roughly 8.0 with calcium hydroxide inhibits Trichoderma spore germination while most gourmet mushroom mycelia tolerate the shift fine. Test on a small batch first since tolerance varies by species and strain.
- Run a sealed chamber with scheduled fresh air exchange. Growers using app-controlled or timer-based FAE report noticeably fewer green mold incidents than those relying on manual humidity tents, based on operator observations from Lykyn’s grower guide.
- Enforce clean-handling discipline. Dedicated grow-room clothing, tools that never touch outdoor soil or compost, and a habit of washing hands before opening any container all close off the entry points Trichoderma relies on most.
Reliable spawn is worth emphasizing on its own. If you want a deeper look at how spawn vigor drives faster colonization and stronger competitive resistance, our guide to growing B+ mushrooms with 100% mycelium walks through exactly why that head start matters.
How Do You Decontaminate a Grow Room After an Outbreak?
Once contaminated material is gone, the room itself still needs real attention before you restart anything. Skipping this step is how a single outbreak turns into a recurring problem.
- Empty the space completely and dispose of all contaminated substrate, casing, and disposable liners before cleaning anything else.
- Wipe down every hard surface with a disinfectant appropriate for the material. Diluted bleach solutions work well on non-porous surfaces like plastic bins and metal shelving, with a contact time of at least 10 minutes before rinsing.
- Replace anything porous that touched the contamination directly. Foam gaskets, cloth filters, and cardboard simply can’t be reliably sterilized.
- Clean or replace HVAC filters, humidifier reservoirs, and any HEPA filtration in your fruiting chamber, since spores lodge in these far more than most growers expect.
- Consider ozone or UV treatment for a persistent recurring problem in a dedicated grow space, but only with proper ventilation and never while people or pets are present in the room.
- Wait at least 48 to 72 hours after cleaning, then run an empty test cycle to confirm no green growth appears before introducing a new batch.
Pro Tip: Run a clean, uninoculated substrate sample through your decontaminated room for a few days as a canary test. If it stays clean, your room is genuinely ready. If green shows up on the test sample, you’ve got a lingering source somewhere you haven’t found yet.
Is Trichoderma Contamination a Health Risk to People?
For most healthy growers, brief exposure to Trichoderma spores causes mild respiratory irritation at worst, similar to reacting to any household mold. The bigger concern is for people who are immunocompromised, where certain species have been linked to genuinely invasive infections rather than just surface irritation, according to clinical reviews of Trichoderma infections.
A few points worth keeping in mind:
- Some strains produce mycotoxins, including gliotoxin, which is one more reason contaminated mushrooms should never be eaten, harvested, or salvaged for consumption.
- Growers with chronic lung conditions, autoimmune disorders, or suppressed immunity should avoid handling sporulating material entirely and let someone else manage disposal if possible.
- Seek medical attention if you develop persistent respiratory symptoms, skin irritation that doesn’t resolve, or any fever following heavy exposure, and tell your clinician specifically that you were exposed to Trichoderma mold spores and mention your immune status.
Is Trichoderma Really That Different From Other Contaminants?
Most beginner troubleshooting guides lump Trichoderma in with cobweb mold, black pin mold, and bacterial wet spot as if they’re roughly interchangeable problems. They’re not. Cobweb mold is mostly a nuisance you can often out-grow with a light hydrogen peroxide misting. Trichoderma is a predator with a chemical arsenal built specifically to break down fungal cell walls, and that distinction should change how seriously you treat the first sighting.
What surprises a lot of new growers is that sterilization, the step everyone assumes is the safest possible substrate prep, isn’t automatically the winning move against this particular contaminant. Wiping out the competing microbial community on a substrate and then reintroducing even a trace of Trichoderma can hand it an open field with no rivals left to slow it down. That’s a genuinely counterintuitive result, and it’s why matching your prep method to your substrate type matters more than defaulting to the most aggressive-sounding option.
The other thing worth saying plainly: rescue attempts fail more often than beginner forums admit. Anything beyond that is usually money and time better spent starting clean than fighting a losing battle and risking your entire growing space in the process. Starting with pre-colonized, lab-tested material removes a huge share of the guesswork that leads to contamination in the first place, simply because you’re not the one managing every variable from raw grain to first pins.
— Alex
Want a Lower-Risk Way to Start Your Next Grow?
Every prevention step above boils down to one idea: give your mycelium the fastest possible head start so contaminants never get a foothold. A pre-colonized, lab-tested starter block does exactly that by skipping the riskiest phase of the process, the early grain-to-substrate window where most home contamination actually begins.
Some suppliers build their kits around that principle. Look for three things in any kit you consider: documented lab testing for contaminants, clear step-by-step instructions that match your experience level, and a support channel you can actually reach if something looks off. Our 100% mycelium B+ grow kit guide breaks down what fast, verified colonization looks like in practice, and our grow kit FAQ covers the troubleshooting questions beginners ask most. If you’re ready to skip the highest-risk stage of the process entirely, browse our full lineup of fresh grow kits and pick a starter block built to outcompete contamination from day one.
Where Can You Learn More About Trichoderma Contamination?
For deeper reading beyond this guide, Penn State Extension’s green mold overview remains the standard reference on outbreak patterns and prevention in commercial settings. The peer-reviewed study on substrate treatments offers the experimental data behind hot-water and alkaline immersion methods. For the clinical side, the Journal of Antimicrobial Chemotherapy’s review of invasive infections and the PMC review on Trichoderma harzianum safety cover human health risk in detail. For hands-on species identification, ShroomCraft Lab’s diagnostic guide remains one of the most practical field references available.
Sources
- Green mold of mushrooms (Penn State Extension)
- Efficiency of treatments for controlling Trichoderma spp during spawning in cultivation of lignicolous mushrooms
- Invasive Trichoderma spp. infections: clinical presentation and outcome (Journal of Antimicrobial Chemotherapy)
- How to Identify Trichoderma: Technical Diagnosis of the Green Monster — ShroomCraft Lab
Recommended

Psilocybin Legal Status: 4 Steps to Verify U.S. and Global Rules
Psilocybin remains a Schedule I controlled substance under federal law, meaning possession, cultivation, and distribution are federal crimes anywhere in the United States. Oregon and Colorado are the two exceptions that matter: both run state-licensed programs where adults can legally access supervised psilocybin experiences. More than 30 U.S. cities have deprioritized enforcement, but that’s a policing choice, not a change to state or federal law, and it offers no real protection if you’re caught with mushrooms.
TL;DR:
- Federal law classifies psilocybin as a Schedule I drug, making possession and distribution illegal nationwide, despite some state and city decriminalization efforts.
- Oregon and Colorado have established regulated frameworks for supervised psilocybin use, but both programs operate within strict on-site, supervised models that do not legalize take-home possession.
- The lack of FDA approval for psilocybin-based medicines means it remains in Schedule I until clinical trials in progress conclude, which could take several years.
- City deprioritization policies reduce enforcement but do not change the legal status of psilocybin, and crossing jurisdictions or borders still involves federal legal risks.
- International legal approaches vary, with some countries allowing personal use or selective legality of certain product forms, but most still treat psilocybin as a controlled substance without broad legal access.
Table of Contents
- Is Psilocybin Legal Under Federal Law?
- Where Are Oregon and Colorado Different From Everywhere Else?
- What Does City Deprioritization Actually Change?
- How Do Other Countries Handle Psilocybin?
- What’s Driving Legal Change Right Now?
- What Are the Real Legal Risks of Using or Carrying Psilocybin?
- How Do You Check the Actual Law Where You Live?
- Publisher Resources for Safety and Education
- What Should Readers Watch for Next?
- Explore Fungipsilocybinmushroom’s Safety and Product Resources
- Sources
Is Psilocybin Legal Under Federal Law?
No. Psilocybin sits in Schedule I of the Controlled Substances Act, the same tier as heroin, reserved for substances the DEA considers to have a high potential for abuse and no accepted medical use. That classification makes possession, growing, selling, or transporting psilocybin mushrooms a federal offense in all 50 states, regardless of what your city council or state legislature has done. The DEA’s drug scheduling framework hasn’t budged on psilocybin, and as of September 2026, there’s still no FDA-approved psilocybin medicine on the market.
That last point matters more than people realize. Schedule I status isn’t just a label. It’s tied to a specific legal finding that a drug has no accepted medical use, and the primary way to overturn that finding is for the FDA to approve a drug containing it. Two things have to happen, in sequence, before psilocybin could move to a lower schedule or off the schedule entirely:
- A drug maker completes Phase 3 clinical trials and files a New Drug Application with the FDA.
- The FDA approves that application, which then gives the DEA legal grounds to reschedule the compound (or the DEA moves on its own through administrative rescheduling, a rarer and slower path).
Neither has happened yet. Compass Pathways and Usona Institute both have Phase 3 programs in progress, and their outcomes are the single biggest lever on federal change. The FDA’s drug approval process explains why this takes years rather than months: trial data has to hold up, manufacturing standards have to be locked in, and safety signals get scrutinized across thousands of patient hours before anything reaches a pharmacy shelf.
Federal Schedule I status means no FDA-approved psilocybin drug exists nationwide as of September 2026, and every state-level program operates as a carve-out, not a challenge to that federal baseline.
The practical fallout from Schedule I status goes beyond criminal exposure. Federal employees and contractors can face termination or security clearance denial for psilocybin use, even where a state has legalized it. Immigration consequences can be severe. A drug conviction, or in some cases even an admission of drug use, can affect a green card application or naturalization case. Crossing state lines with mushrooms, even from a legal-access state to another, is a federal transport issue because it treats the substance as contraband the moment it crosses a border the federal government controls.
Where Are Oregon and Colorado Different From Everywhere Else?
Oregon and Colorado are the only two states that have built regulated frameworks for legal psilocybin access, and they took different routes to get there.
Oregon passed Measure 109 in 2020, and the resulting service center model has been operating since January 2023. Adults 21 and older can book a supervised psilocybin session at a state-licensed service center, but there’s no prescription involved and no take-home product. You consume it on-site, under supervision, and leave without any mushrooms in your possession. More than 100 licensed centers were operating by 2026, and a typical session runs $1,800 to $3,500, a price point that reflects facilitator time, facility costs, and the multi-hour commitment a full session requires. The Oregon Health Authority regulates the program, and in 2026 it merged its psychedelic mushroom oversight with its medical marijuana regulatory arm, partly to address budget shortfalls. That merger came with proposed licensing fee increases, a reminder that these programs are still finding their financial footing years after voters approved them.
Colorado took a broader approach with Proposition 122 in 2022. It decriminalized personal possession, use, and limited home cultivation and sharing for adults, on top of building a licensed healing-center framework similar in spirit to Oregon’s. Licensed centers began opening in 2024 and 2025, regulated through the state’s Division of Professions and Occupations. The distinction that trips people up: decriminalization under Prop 122 applies broadly to personal use, while the licensed healing-center piece is the supervised, paid-session model, closer to what Oregon offers. Both tracks exist side by side under state law.
Outside these two states, the picture is a patchwork of pilot programs, research exemptions, and bills that haven’t crossed the finish line. Several states have introduced legislation modeled on Oregon or Colorado, and a growing number have adopted what’s called trigger law language, meaning a statute that only activates certain psilocybin allowances if and when the FDA approves a psilocybin drug or the DEA reschedules it. That drafting choice matters because it determines how fast a state could move if federal rules change. A state with a trigger law already on the books could have a functioning program within months of federal rescheduling. A state starting from zero would need years to write and pass new legislation.
Pro Tip: Before assuming any state “allows” psilocybin, check whether the law is a full decriminalization statute, a licensed-access program, or just a pending bill that hasn’t passed yet. All three get reported in the news using similar language, and conflating them is one of the most common mistakes readers make.
State law and federal law don’t cancel each other out. Oregon and Colorado residents using licensed programs are still technically violating federal law, even though federal prosecutors have shown little interest in pursuing individual users in states with regulated access. That gap between what’s tolerated and what’s technically illegal is the defining feature of psilocybin law in 2026.

What Does City Deprioritization Actually Change?
Not much, legally speaking. City deprioritization is a local government or district attorney’s decision to make psilocybin enforcement the lowest law enforcement priority, or to direct police and prosecutors not to pursue simple possession cases. It’s an administrative directive, not a change to the underlying statute. The mushrooms are still illegal under state and federal law in every deprioritized city. What changes is the likelihood that local police will make an arrest or that a local prosecutor will file charges.
More than 30 U.S. cities have passed some version of this policy, including well-known examples like Denver (which deprioritized psilocybin before Colorado’s statewide measure passed), Oakland, Santa Cruz, Ann Arbor, and Seattle. Each city’s policy language differs slightly. Some cover only personal possession; others extend to cultivation for personal use or gifting between adults.
Two limitations deserve attention:
- Deprioritization can be reversed by a new city council, a new district attorney, or a new police chief without any ballot measure or legislative vote.
- It provides zero protection outside city limits. A deprioritized city sitting inside a state where psilocybin is still fully criminalized doesn’t change your legal exposure the moment you cross into county jurisdiction, drive to a neighboring town, or get stopped by state or federal authorities rather than local police.
Reporters and advocates often blur the line between local deprioritization and actual decriminalization, and that confusion creates false expectations for people who assume “my city deprioritized it” means “it’s legal here.” It doesn’t. It means enforcement is a lower priority, which is a meaningfully different thing than the possession laws actually changing.
How Do Other Countries Handle Psilocybin?
International approaches to psilocybin fall into four rough categories: fully scheduled and criminalized, decriminalized for personal use, regulated medical access, and a gray zone where a specific product form (like fresh truffles) is tolerated while dried mushrooms remain illegal.
The Netherlands is the clearest example of that last category. Dried psilocybin mushrooms have been banned since 2008, but psilocybin-containing truffles remain legal for sale in licensed smartshops because they weren’t included in the original ban’s plant classification. Visitors to Amsterdam regularly buy truffles legally while assuming, incorrectly, that mushrooms carry the same status.
A few other notable examples:
- Jamaica has never scheduled psilocybin mushrooms, which has made it a hub for commercial retreat centers operating in a genuinely unscheduled legal environment rather than a gray area.
- Brazil doesn’t explicitly schedule psilocybin mushrooms, and that regulatory ambiguity has allowed retreat operators to run legally ambiguous but practically tolerated businesses.
- Canada doesn’t have broad legal access, but its Special Access Program allows physicians to request psilocybin for patients with serious or life-threatening conditions who haven’t responded to standard treatments, a narrow medical exception rather than general legalization.
- Many other countries, including most of the EU beyond the Netherlands’ truffle carve-out, still treat psilocybin as a fully scheduled controlled substance with no legal personal-use pathway.
If you’re planning to attend a retreat abroad, verifying legal status is only half the job. Retreat legitimacy and medical staffing vary enormously even within countries where the practice is tolerated. A center operating in a legal gray zone in Brazil or Jamaica may or may not have a physician on-site, may or may not screen for contraindicated medications or heart conditions, and may or may not carry any liability insurance. Country-level legality tells you whether you’ll get arrested. It tells you nothing about whether the facilitators know what they’re doing.
Access even within legal state programs isn’t as open as headlines suggest. Cost and geography limit uptake in both Oregon and Colorado, since licensed sessions aren’t covered by mainstream insurance and centers remain concentrated in a handful of metro areas rather than spread statewide.
What’s Driving Legal Change Right Now?
Three forces are shaping where psilocybin law goes next: ballot initiatives, trigger laws, and the clinical trials that could unlock federal rescheduling.
Ballot measures have had a mixed record. Oregon’s Measure 109 and Colorado’s Prop 122 both passed, but similar measures in other states have stalled at the signature-gathering stage or failed outright at the ballot box. That inconsistency reflects genuine public split on the issue rather than a clear national trend in one direction. Some states are instead moving through the legislature, introducing bills that mirror the Oregon service-center model or Colorado’s decriminalization-plus-licensing structure, with mixed success getting them out of committee.
Trigger laws are the quieter but arguably more important development. These are statutes drafted so that certain psilocybin allowances only activate once the FDA approves a psilocybin-based drug or the DEA reschedules the compound. States adopting this language are essentially pre-positioning themselves for a federal change they can’t control the timing of, so they can move quickly instead of starting the legislative process from scratch. Watching policy trackers is the most reliable way to see which states have this language on the books and which bills are actively moving.
The clinical trial pipeline is the piece that could reshape everything else. Compass Pathways’ COMP360 and Usona Institute’s IPR001 are both in Phase 3, the last stage before an FDA New Drug Application. Neither has produced an approved drug as of mid-2026, but a successful outcome for either program would be the strongest catalyst for federal rescheduling that currently exists. It would also likely accelerate every trigger law sitting on a state’s books, turning conditional statutes into active law almost overnight.
None of this means change is imminent. Phase 3 trials, FDA review, and any subsequent DEA rescheduling process typically take years even in a best-case scenario. Readers tracking this space should expect incremental movement, not a single announcement that flips the legal picture nationwide.

What Are the Real Legal Risks of Using or Carrying Psilocybin?
Federal prosecution of individual users for simple possession is uncommon in practice, but “uncommon” isn’t “impossible,” and the variables that push a case toward prosecution include quantity, intent to distribute, prior record, and whether the case intersects with another federal matter (a border stop, an immigration proceeding, a firearms investigation). Federal resources tend to focus on distribution and trafficking rather than personal use, but that pattern isn’t a guarantee, and it can shift with political priorities.
Collateral consequences often matter more than the criminal charge itself:
- Federal employees, contractors, and security-clearance holders can lose their jobs or clearance over psilocybin use, even in a legal-access state.
- Immigration consequences can include denial of a green card, naturalization, or reentry, since federal immigration law treats controlled substance violations harshly regardless of state legality.
- Federal benefits and firearms eligibility can both be affected by a drug conviction, since federal law prohibits firearm possession by unlawful drug users.
- Child custody proceedings sometimes treat psilocybin use as evidence of impaired judgment, even where the underlying use was legal under a state program.
Transporting psilocybin across any border, state or international, carries outsized risk compared to using it in a fixed location. Crossing state lines turns simple possession into a potential federal trafficking or transport issue, and crossing an international border adds customs law and the receiving country’s own statutes on top of that. Airports and ports of entry are federal jurisdiction by definition, which erases any state-level protection the moment you’re in that space.
Different product forms also get treated inconsistently. Spores are legal to possess in most U.S. states because they don’t contain psilocybin themselves, even though germinating them into mushrooms is illegal almost everywhere spores are sold. Edibles and concentrates sometimes fall into legal gray areas that dried mushroom possession doesn’t, simply because older statutes were written before those product forms existed.
Pro Tip: If you’re relying on a state’s licensed program, keep documentation of your session (receipts, facility licensing info) rather than any product. Oregon and Colorado programs are built around consumption on-site, and carrying product away from a licensed facility puts you outside the protection the program was designed to offer.
How Do You Check the Actual Law Where You Live?
Verifying psilocybin’s legal status where you live, or where you’re traveling, takes a few concrete steps rather than a single Google search.
- Start with the DEA’s scheduling page to confirm the federal baseline hasn’t changed.
- Check your state legislature’s official website for the actual statute text, not a news summary, and note its effective date.
- If your state has a licensed program (currently Oregon or Colorado), review the regulating agency’s site (Oregon Health Authority or Colorado’s Division of Professions and Occupations) for current licensing rules and any recent fee or policy updates.
- Cross-reference with a dedicated tracker, since these compile bill numbers, ballot text, and municipal measures in one place.
A few resources are worth bookmarking rather than searching for each time:
- The Psychedelic Alpha law and policy tracker for near-real-time updates on state bills and municipal measures.
- The Berkeley Center for the Science of Psychedelics law and policy map for a state-by-state legal overview.
- Your state’s official legislative website for primary statute text, which always outranks a news article’s summary of that text.
Practical risk reduction comes down to a short list: never transport psilocybin across state or international borders, consult an attorney before assuming any high-stakes use case (employment, custody, immigration) is safe, and if you’re using a licensed state program, keep records showing you followed its rules.
Publisher Resources for Safety and Education
A reputable supplier maintains lab-testing standards across its product catalog and publishes harm-reduction material because legal access and safe use are two separate problems that both deserve real answers. Readers researching dosing guidance will find practical, experience-level breakdowns rather than vague advice, and the site’s broader psilocybin education hub covers everything from strain differences to how psilocybin compares with other psychedelics.
None of this is legal advice. Nothing in this article should be read as a recommendation to violate any law in your jurisdiction. Laws vary by state and country, change over time, and carry consequences that a general information page can’t account for. If you’re facing a specific legal question, a licensed attorney in your jurisdiction is the only reliable source for advice you can act on.
What Should Readers Watch for Next?
Phase 3 results from Compass Pathways and Usona Institute are the single biggest variable to track over the next few years. A positive outcome would likely accelerate trigger laws already sitting in multiple state legislatures, turning conditional statutes into active programs faster than a normal legislative process would allow. Short of that, expect the current pattern to continue: more cities deprioritizing enforcement, a handful of states experimenting with pilot programs, and Oregon and Colorado working out the operational kinks in their licensing systems.
My advice is unglamorous but durable: verify the actual statute before you act, not a headline or a friend’s summary of one. Use trackers like Psychedelic Alpha for anything time-sensitive, and treat state-level access as narrower and more conditional than most coverage implies.
— Alex
Explore Fungipsilocybinmushroom’s Safety and Product Resources
Understanding where psilocybin stands legally is only useful once you’re also thinking about quality and safety; reputable vendors typically ensure their products ship with lab-testing so users know what they’re taking. That matters more in a legal landscape this fragmented, where the substance itself often isn’t the risky part of the equation, but an untested, unverified source can be.
For readers exploring options, the Copelandia Cyanescens listing shows what a rigorously tested, high-potency strain looks like on the market, and the therapeutic strains guide breaks down options by experience level rather than marketing hype. Fungipsilocybinmushroom ships discreetly worldwide and backs every order with the same testing standards discussed throughout this guide. Browse the current catalog and see which strain fits your experience level before you place an order.
This article is general information, not a substitute for advice from a qualified lawyer. Consult a qualified legal professional about your own circumstances before acting on anything here.
Sources
Recommended

0.05–0.5 g Microdosing Psilocybin: Science Informed Safety for Beginners
Microdosing means taking a sub-perceptual amount of psilocybin, typically somewhere between 0.05 and 0.5 grams of dried mushroom, often enough to notice subtle shifts in mood or focus but not enough to trip. The evidence for real benefit beyond placebo is still thin and mixed. If you’re going to try it anyway, the conservative starting points recommended by harm-reduction sources involve low doses taken on schedules such as the Fadiman one day on, two days off pattern, with medical consultation advised if you have any heart, mood, or psychiatric history.
TL;DR:
- Dosing doses around 0.1 grams of dried mushrooms roughly equal 1 milligram of psilocybin, but potency varies widely between batches.
- A week-long homogenous batch of ground mushrooms ensures accurate measurement, while pre-measured, lab-verified capsules reduce variability.
- The Fadiman schedule (one day on, two off) is common, but clinical trials often use once or twice weekly doses over 4 to 8 weeks, with deliberate breaks afterwards.
- People with psychosis, bipolar disorder, or unstable heart conditions should avoid microdosing without medical supervision due to significant health risks.
- Expectancy bias influences subjective effects; structured tracking and blinded testing help distinguish real benefits from placebo effects.
Table of Contents
- Quick Starter Checklist Before Your First Microdosing Psilocybin Guide Cycle
- Dosing Explained: Grams, Milligrams, and How to Find a Safe Starting Point
- Protocols and Schedules: Fadiman, Stamets, and What Clinical Trials Actually Test
- Safety, Contraindications, and Drug Interactions You Need to Know
- Legal Status Snapshot and How to Reduce Your Legal Risk
- How to Track Effects and Tell If Microdosing Is Actually Working
- Practical How-To: Sourcing, Preparing, Dosing, and Storing Your Supply
- What Beginners Consistently Get Wrong About Microdosing
- Fungi Psilocybin Mushroom: Lab-Tested Options for a Safer Microdosing Cycle
- Where to Go Next for the Research Behind This Guide
- Sources
Quick Starter Checklist Before Your First Microdosing Psilocybin Guide Cycle
Before you weigh out a single milligram, run through a short readiness check. Rushing this step is where most beginners create problems for themselves later.
- Check for red flags first. A personal or family history of psychosis, schizophrenia, or bipolar disorder is a reason to skip microdosing entirely, and anyone with unstable heart disease or on psychiatric medication should talk to a clinician before starting. If you take an MAOI or a serotonergic medication, stop here and get medical advice.
- Gather the right supplies. You need a precision scale accurate to at least 0.01 grams (10 mg), or pre-measured, lab-tested capsules if you’re buying finished product. Add a simple paper or app-based dosing log and a timer or calendar reminder so doses don’t get taken erratically.
- Set your baseline, then start small. Track your mood, sleep, and focus for a few days before your first dose. Pick the most conservative dose you can (0.05 to 0.1 g), choose a schedule like Fadiman’s one-on/two-off pattern, and begin.
A trusted source matters as much as the scale. Potency varies wildly between batches, and starting a dosing schedule with an unverified product undermines every other precaution on this list.
Dosing Explained: Grams, Milligrams, and How to Find a Safe Starting Point
Dried mushroom weight and psilocybin content are not the same measurement, and confusing them is the single most common beginner mistake. Dried Psilocybe cubensis potency swings from roughly 0.5% to over 1% psilocybin by weight depending on the strain, growing conditions, and how it was dried. That means a gram of one batch might carry twice the active compound of a gram from another source.
Community-reported microdose ranges run from about 0.05 to 0.5 grams dried mushroom, a wide spread that reflects just how inconsistent home dosing tends to be. A systematic review covering 11 studies and 3,262 adults found dried-mushroom microdoses reported across that same 0.05 to 1.0 gram range, with extreme heterogeneity in protocols and low certainty of evidence overall. Clinical trials, by contrast, tend to standardize around 2 mg of pure psilocybin, a dose chosen precisely because it removes the guesswork that plagues home dosing.
Here’s roughly how the two units relate, assuming an average potency batch:
- 0.1 g dried mushroom ≈ roughly 1 mg psilocybin, depending on strain potency.
- 0.2 to 0.25 g dried mushroom ≈ roughly 2 mg psilocybin, close to the dose used in several clinical trials.
- 0.5 g dried mushroom ≈ the dose used in a double-blind placebo-controlled study that found no consistent improvement in creativity or cognition at that level.
Because potency varies so much, weighing a single mushroom cap and guessing its strength is unreliable. The better approach is homogenizing an entire batch: grind multiple dried mushrooms from the same harvest into a fine, even powder, then weigh individual doses from that powder. This evens out the hot spots and weak spots that exist in any single mushroom.
If you’d rather skip the grinding and weighing altogether, pre-made extract or whole-mushroom capsules with lab-verified potency remove most of the variability. That’s the appeal of buying capsules with a batch test attached rather than eyeballing a dried cap from an unknown source.
Titration protocol, step by step:
- Start at the low end, 0.05 to 0.1 g dried (or the capsule equivalent), never higher on day one.
- Hold that dose for at least three to four dosing sessions before changing anything. One dose tells you almost nothing.
- If you notice no effect and no side effects after several sessions, increase by a small increment, no more than 0.05 g at a time.
- Never double a dose to “catch up” or chase a stronger effect. If a dose feels too strong (anxiety, restlessness, noticeable perceptual changes), scale back immediately.
- Keep every other variable steady while titrating. Sleep, caffeine, food timing, and stress levels all interact with how a dose feels, so changing several things at once makes it impossible to tell what caused what.
Pro Tip: Weigh out an entire week or cycle of doses in one sitting, right after you’ve homogenized your batch. Doing the math and measuring once, rather than eyeballing a fresh dose every dosing day, is where most measurement errors sneak in.
Protocols and Schedules: Fadiman, Stamets, and What Clinical Trials Actually Test
The Fadiman protocol, named for psychologist James Fadiman, follows a one-day-on, two-days-off rhythm: dose on day one, take two full days off, then repeat. The two off-days are meant to prevent tolerance buildup and give you a clear baseline to compare against on non-dosing days. It’s the most widely cited self-experimentation schedule in microdosing communities, largely because it’s simple to follow and easy to track.
The Stamets protocol, associated with mycologist Paul Stamets, runs a tighter cycle: four days on, three days off, often stacked with lion’s mane mushroom and niacin, based on a theory about neurogenesis that hasn’t been tested in controlled human trials. It’s more intensive than Fadiman’s approach and carries more cumulative exposure across a given month, which matters if you’re trying to minimize chronic dosing risk.
Clinical research looks different from either community protocol. Trials testing repeated low doses of psilocybin have used schedules ranging from once weekly to several times a week, generally over windows of 4 to 8 weeks, with some phase II trial designs extending follow-up monitoring out to two years to catch delayed or cumulative effects that a short study would miss.
Choosing and managing a schedule:
- If your goal is mood tracking with minimal exposure, Fadiman’s one-on/two-off pattern gives you the most rest days relative to dosing days.
- If you’re specifically trying to mirror clinical dosing patterns, a once or twice weekly 1 to 2 mg dose better resembles what trials actually test.
- Cap any cycle at 4 to 8 weeks before taking a deliberate break of at least two to four weeks. This mirrors the duration windows used in trial evidence rather than open-ended, indefinite use.
- Stop immediately, not just pause, if you notice mood worsening, sleep disruption, anxiety climbing, or any cardiovascular symptoms.
- Reassess after each cycle using your own tracked data before deciding to continue, adjust, or stop entirely.
There’s no clinically validated protocol that beats the others. What exists is a patchwork of anecdotal regimens that have never been directly compared in a controlled trial, which is exactly why the schedule you pick should be less important to you than the tracking you do while following it.
Safety, Contraindications, and Drug Interactions You Need to Know
Certain groups should not microdose, full stop. A personal or family history of psychosis, schizophrenia, or bipolar disorder puts you at meaningfully elevated risk, since psilocybin can trigger or worsen manic or psychotic episodes even at low doses. Unstable heart disease is a separate concern, discussed below in more detail.
Contraindications and interaction risks:
- Personal or family history of psychosis, schizophrenia, or bipolar disorder.
- Unstable or serious cardiovascular disease.
- Current use of MAOIs, which can interact dangerously with serotonergic compounds.
- Current use of SSRIs, SNRIs, lithium, or other psychiatric medications that affect serotonin signaling, where interactions are poorly studied at microdose levels.
- Pregnancy or breastfeeding, where no safety data exists at any dose.
- Active substance use disorder, where introducing another psychoactive substance complicates recovery and monitoring.
What the evidence actually shows: A phase II randomized trial of 39 adults with major depressive disorder tested repeated 2 mg psilocybin doses over 8 weeks and found symptom reductions comparable to placebo, a result that underscores how much of the reported benefit in open-label use may be expectancy rather than pharmacology.
The theoretical long-term risk that gets the least public attention is cardiovascular. Psilocybin and related compounds can stimulate the 5-HT2B serotonin receptor, the same receptor family implicated in valvular heart damage from other drugs that hit it chronically. Harvard’s Petrie-Flom Center has raised this concern directly, noting that repeated, chronic low-dose exposure introduces a different risk profile than an occasional full psychedelic dose, and that nobody has run the multi-year cardiac monitoring studies needed to rule this out definitively.
Monitoring for adverse effects while microdosing doesn’t require expensive equipment, just consistency. Track resting heart rate and blood pressure periodically if you have any cardiac risk factors at all. Note any new anxiety, irritability, sleep disruption, or mood swings in your log, and treat two or more consecutive bad sessions as a stop signal rather than something to push through.

Unblinding is a real confound worth taking seriously. Because you know you took a dose, your expectations color what you report feeling, and researchers studying microdosing point to expectancy bias as one of the biggest reasons open-label self-reports diverge so sharply from blinded trial results. A double-blind placebo-controlled study using 0.5 g dried mushroom found no consistent improvement in creativity or cognition, despite many participants subjectively feeling that something had changed. If you want a resource that lays out these safety considerations in more depth, Fungipsilocybinmushroom’s safety guide is a reasonable place to keep learning.
Legal Status Snapshot and How to Reduce Your Legal Risk
Psilocybin remains a Schedule I controlled substance under U.S. federal law as of 2026, which means possession, cultivation, and distribution are federally prohibited regardless of what any state has done. Two states have carved out regulated exceptions. Oregon’s Measure 109 created licensed service centers, operating since 2023, where adults can access supervised psilocybin sessions. Colorado’s Proposition 122 combined personal decriminalization with a healing center licensing structure that rolled out between 2024 and 2025. Outside those two frameworks, federal Schedule I status is the operative law almost everywhere in the country, and other jurisdictions worldwide vary just as widely, so what’s tolerated in one city or country can carry serious penalties in the next.
Practical steps to reduce legal exposure:
- Use a licensed service center where one legally exists, such as Oregon’s model, rather than assembling an unsupervised session on your own.
- Never ship psilocybin products across state or national borders, since that turns a possession issue into a trafficking-adjacent one under federal and international law.
- Check your specific state or country’s current statute before acting. Laws in this space are changing quickly and a guide written even a year ago may already be outdated.
- Keep any personal-use quantities and documentation minimal and private, and avoid any activity that could be construed as distribution.
None of this is legal advice for your specific situation. If you have real legal exposure concerns, a local attorney familiar with drug policy in your jurisdiction is the only reliable source, not a blog post.
How to Track Effects and Tell If Microdosing Is Actually Working
Expectancy bias is strong enough that you can talk yourself into feeling better from a dose that’s doing nothing pharmacologically. The only real defense is a structured tracking system you commit to before you start, not after you already have a hunch about the outcome.
- Establish your baseline for at least one week before dosing. Use a validated short scale like the PHQ-2 or PHQ-9 for mood, log your sleep hours and quality, rate your stress on a simple 1 to 10 scale, and time yourself on a basic focus task like a short reading or math drill.
- Log every dosing day and every off day the same way. Keep entries short: dose taken, time, mood score, sleep from the night before, any side effects, and a one-line note on anything unusual. A weekly summary that averages these daily entries will show trends a single day’s notes can’t.
- Run a blinded phase if you’re serious about separating real effect from expectancy. Have someone else prepare identical-looking capsules, some active and some inert, without telling you which is which on a given day, then compare your logged scores across both.
- Set decision rules in advance. Decide before you start what a meaningful improvement looks like on your chosen scale, what counts as a warning sign to pause immediately, and what counts as no-change data that means it’s time to stop and reassess with a clinician.
Pro Tip: Write your decision rules down on paper before your first dose, not in your head. It’s much harder to talk yourself out of a rule you already committed to in writing than one you’re deciding on in the moment, three weeks into a cycle that isn’t working.
If four to eight weeks pass with no measurable change on your tracked scores, that’s real data, not a reason to push the dose higher. Raising the dose to chase an effect that isn’t showing up is how sub-perceptual microdosing turns into something else entirely.
Practical How-To: Sourcing, Preparing, Dosing, and Storing Your Supply
Lab testing is the difference between knowing what you’re taking and guessing. A real test result shows potency (psilocybin and psilocin content by weight) and screens for contaminants like heavy metals, mold, or bacterial contamination that can grow on improperly dried or stored mushrooms. Skipping this step means every gram you measure afterward is built on an unknown.
- Start with a homogenized batch. Take your full dried supply from a single harvest or a single tested product, and grind it into a fine, even powder using a clean coffee grinder or mortar and pestle dedicated to this purpose. This step alone eliminates the hot-spot problem where one mushroom cap is far stronger than another from the same batch.
- Weigh individual doses with a precision scale. Use a scale accurate to 0.01 grams (10 milligrams), tare an empty container first, then measure each dose directly into that container rather than eyeballing a portion of a whole mushroom.
- Fill capsules for consistency and convenience. Standard-size capsules (00 or 0) hold most microdose amounts easily and remove the temptation to “just take a pinch” on a rushed morning.
- Label every batch clearly. Write the date, the source batch, and the estimated dose per capsule on the container. Memory is not a reliable label after the third or fourth batch.
- Store away from light, heat, and moisture. A dark, airtight container in a cool cabinet preserves potency far longer than a bag left near a stove or a sunny windowsill; potency can degrade meaningfully within months under poor storage conditions.
Dosing-day checklist:
- Take your dose at the same time each dosing day, generally with or shortly after breakfast, to control for how food affects absorption.
- Stay hydrated through the morning, since mild dehydration can amplify subjective side effects like headache or lightheadedness.
- Dose in a familiar, low-stress environment rather than before a high-pressure meeting or unfamiliar situation, especially in your first few sessions.
- Record your notes within an hour of dosing while the details are still fresh, not at the end of the day from memory.
Pro Tip: If you’re buying finished product rather than preparing your own, treat the batch certificate of analysis the same way you’d treat a nutrition label. If a seller can’t produce one, that’s your answer about whether to buy from them. Sourcing from a vendor that publishes lab results alongside its microdosing capsules removes the homogenizing and weighing steps entirely, at the cost of trusting someone else’s testing process instead of your own scale.
What Beginners Consistently Get Wrong About Microdosing
The evidence base for microdosing is genuinely weaker than most enthusiastic online communities let on, and that gap between hype and data is where most beginner mistakes start. People read anecdotal success stories, skip the baseline tracking, and jump straight to a dose that’s already at the high end of the community range instead of the low end. A double-blind trial and a large systematic review both point the same direction: self-reported benefits often shrink or vanish once expectancy is controlled for, which should temper how much weight you put on a single week of feeling “clearer.”
The three mistakes I see most often are dosing too high out of impatience, skipping any kind of log because “I’ll just notice if it’s working,” and ignoring a personal or family psychiatric history because a friend’s experience sounded fine. Each of those is fixable with about ten minutes of upfront planning. Weigh a conservative dose, write down a baseline before you start, and actually talk to a clinician if bipolar disorder or psychosis runs in your family. None of that is complicated. It’s just often skipped.
The habits that make the biggest difference aren’t exotic. A short daily journal entry, protected sleep, and a willingness to bring what you’re doing up with a therapist if you’re already in talk therapy all do more for outcome quality than switching between Fadiman and Stamets ever will. Microdosing works best as one input alongside those habits, not as a replacement for them.
— Alex
Fungi Psilocybin Mushroom: Lab-Tested Options for a Safer Microdosing Cycle
There are options available that include batch-level lab testing, which means the conversion math in this guide, grams to milligrams, dose to schedule, can hold up against what’s in the capsule you open.
When browsing a catalog, look for clear batch test disclosures, dose labeling that states milligrams per capsule rather than a vague “microdose” claim, and traceability back to a specific harvest or production run. The Seremoni psilocybin chocolate bar is a good example of a format that makes portioning simple without a scale, while strain pages like the Amazonian psilocybin mushroom guide walk through potency differences worth knowing before you pick a starting product. If you have a cardiac, psychiatric, or medication history covered in the safety section above, talk to a clinician before you order anything. Otherwise, browse the current lab-tested selection and start with the lowest dose option listed.
Where to Go Next for the Research Behind This Guide
The Frontiers in Psychiatry systematic review is the best single starting point for understanding how thin and heterogeneous the microdosing evidence base still is. Pair it with the double-blind placebo-controlled trial for a look at what happens when expectancy is controlled for, and the active phase II trial listing for what’s currently being tested with longer follow-up. For legal boundaries, check the DEA’s scheduling page directly rather than a secondhand summary. Anecdotal reports are useful for generating hypotheses, but treat trial data as the stronger signal whenever the two disagree.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
- DEA — Drug scheduling (psilocybin)
- Frontiers in Psychiatry — The subtle science: a systematic review of psilocybin microdosing
- Translational Psychiatry — Microdosing with psilocybin mushrooms: a double-blind placebo-controlled study
- Clinicaltrials
Recommended

Psilocybin and SSRIs for Clinicians: Why Half Report Blunted Effects
Combining psilocybin with SSRIs has not been linked to widespread severe harm in the medical literature, but it is not risk-free either. The most consistent finding is attenuation: many people on SSRIs report a noticeably weaker psychedelic experience, not a dangerous one. Serious interactions do exist, mostly in polypharmacy situations. Talk to your prescriber before changing anything, and never stop an SSRI cold to “clear the way” for a mushroom experience.
TL;DR:
- About half of SSRI users report weaker psilocybin effects, with SNRIs more likely to blunt and bupropion least likely to do so, but outcomes vary.
- Controlled trials suggest SSRIs may soften adverse effects while leaving some positive experiences intact, though the research data remains limited and caution is advised.
- Serotonin syndrome risks are rare with SSRIs alone but increase when combined with other serotonergic drugs like lithium or MAOIs, requiring careful medication review.
- Receptor adaptation from long-term SSRI use can prolong attenuation effects, sometimes lasting weeks or months after stopping the medication, depending on the specific drug.
- Always consult a healthcare professional before combining psilocybin with SSRIs, disclose your full medication list, and avoid abrupt discontinuation to prevent withdrawal or adverse interactions.
Psilocybin and SSRI Interaction: What the Research Actually Shows
Four types of evidence shape what clinicians and researchers currently know about mixing psilocybin with SSRIs: retrospective surveys, controlled trials, scoping reviews, and scattered case reports. None of them tell exactly the same story, and that mismatch is itself useful information for anyone weighing this decision.
The largest and most cited data point comes from a 2023 retrospective survey. that collected self-reports from people who used psilocybin mushrooms while on antidepressants. The survey found that concurrent SSRI use was associated with weaker-than-expected psilocybin effects in a substantial share of cases, with SNRIs showing an even higher rate and bupropion showing the lowest. This is the single dataset most people point to when they say “SSRIs blunt shrooms,” and it deserves a closer look because the numbers are more specific than most articles let on.
Those figures come with confidence intervals wide enough to remind you this is self-reported survey data, not a lab measurement. Still, the pattern holds up: serotonergic antidepressants blunt the experience for a meaningful minority, sometimes a slight majority, of users. The same survey noted something clinicians find more clinically relevant than the percentages themselves: attenuation can persist for up to three months after stopping the antidepressant, which challenges the common assumption that a two-week break resets everything.
Controlled trial data tells a more nuanced version of the same story. A randomized, double-blind, placebo-controlled crossover study pretreated healthy volunteers with escitalopram for 14 days before giving them psilocybin. The result was not simple blunting across the board. Escitalopram pretreatment reduced adverse physiological effects, including anxiety and cardiovascular symptoms, but the positive subjective effects were not eliminated. Psilocin pharmacokinetics stayed unchanged, meaning the drug reached the bloodstream the same way regardless of escitalopram exposure. The interaction looks less like “SSRIs cancel out mushrooms” and more like “SSRIs may take the edge off the rough parts while leaving the meaningful parts intact,” at least in this small sample of healthy subjects.
That distinction matters because it partially contradicts the survey data, which trends toward broad-strokes attenuation rather than selective softening of adverse effects. A 2025 scoping review synthesizing case reports, trials, and observational data tried to reconcile this gap and landed on a cautious middle ground. Concomitant use appears generally safe and tolerable, but the controlled-trial base is still thin, and more rigorous studies are needed before anyone should treat these findings as settled.
Case reports fill in the risk side of the picture, though rarely with psilocybin and SSRIs alone. Documented adverse events involving serotonin toxicity tend to appear when psychedelics are combined with other serotonergic or interacting drugs, particularly lithium or MAOIs, rather than SSRIs in isolation. That is not a reason to relax; it is a reason to be far more careful about your full medication list than about the SSRI-psilocybin pairing specifically.
A few practical points fall out of this evidence base:
- Attenuation is common but not universal. Roughly half of SSRI users notice weaker effects, so plan for either outcome rather than assuming complete blunting.
- SNRIs appear more likely to blunt effects than SSRIs, and bupropion appears least likely among the three.
- Controlled trials and naturalistic surveys don’t fully agree, and that gap should make anyone cautious about treating either dataset as the final word.
- Serious adverse events in the literature involve polypharmacy far more often than SSRI use alone.
- The NIDA psilocybin research summary gives useful context on mechanism and the current state of therapeutic investigation for readers who want a plain-language starting point.
Why SSRIs Change the Way Psilocybin Feels
The interaction between psilocybin and SSRIs comes down to receptor biology, not a direct chemical clash between the two drugs. Psilocybin itself is essentially inactive until your body converts it into psilocin, which is the molecule doing the real work. Psilocin binds primarily to the 5-HT2A serotonin receptor, and that binding is what drives the classic psychedelic effects: altered perception, mood shifts, and the sense of expanded or dissolved boundaries people describe after a session.
SSRIs work through an entirely different mechanism. They block the reuptake of serotonin at the synapse, which raises the amount of serotonin circulating in the brain over time. That sounds like it should amplify a serotonin receptor agonist like psilocin, but the opposite tends to happen. Chronic SSRI use triggers downstream adaptations, including downregulation and desensitization of certain serotonin receptors, as the brain tries to recalibrate to the elevated baseline. The 5-HT2A receptor is one of the receptors affected by this adaptation, and a desensitized receptor responds less strongly when psilocin arrives to activate it.

That is the leading explanation for attenuation: not a chemical standoff, but a receptor system that has already adjusted its sensitivity before psilocybin ever enters the picture.
Pro Tip: If you’ve been on an SSRI for years, your 5-HT2A receptor sensitivity has likely had a long time to adjust. That history matters more than the dose you’re currently taking, so mention how long you’ve been on the medication, not just the current dose, when discussing this with a prescriber.
Transporter occupancy, the mechanism that dominates conversations about MDMA and SSRIs, plays a smaller role here. MDMA depends heavily on serotonin transporters to produce its effects, so an SSRI occupying those transporters directly blocks MDMA’s mechanism of action. Classic psychedelics like psilocybin don’t rely on the transporter the same way, since psilocin acts directly on postsynaptic receptors rather than needing transporter-mediated release. That is one reason the psilocybin and SSRI interaction looks different, and generally milder, than the psilocybin and MAOI interaction or the MDMA and SSRI interaction.
Pharmacokinetics complicate the picture further, especially around timing. Different SSRIs clear the body at very different speeds:
- Sertraline and escitalopram have relatively short half-lives, generally clearing within days to about a week after the last dose.
- Paroxetine also clears fairly quickly but can produce more pronounced discontinuation symptoms.
- Fluoxetine is the outlier. Its long half-life and active metabolite, norfluoxetine, can remain pharmacologically active for several weeks after the last dose.
This is exactly why a blanket “two-week washout” rule, which shows up constantly in casual advice and even in some older trial protocols, does not hold up for every medication. Two weeks might clear sertraline from your system reasonably well. It barely dents fluoxetine’s active metabolite. Receptor-level adaptations add another layer on top of pharmacokinetic clearance: even after the drug itself is gone, the desensitized 5-HT2A receptors may take additional time, potentially weeks to months, to return to a baseline sensitivity. That is the biological basis for the persistence finding in the retrospective survey. The drug leaves faster than the receptor adaptation reverses.
None of this means SSRIs make psilocybin dangerous at the receptor level. It means the timeline for “clearing” an SSRI before expecting a full-intensity psilocybin experience is longer and more individualized than most casual guidance suggests, and it depends on which specific SSRI, how long you’ve taken it, and your own receptor biology.
Serotonin Syndrome and Other Documented Risks
Serotonin syndrome is the adverse event most people worry about when they hear “psilocybin and SSRI,” and it deserves a precise definition rather than vague alarm. It’s a cluster of symptoms caused by excess serotonergic activity, typically appearing within hours of a triggering exposure, and it spans three symptom categories:
- Autonomic instability: rapid heart rate, high blood pressure, elevated temperature, sweating, diarrhea.
- Neuromuscular abnormalities: tremor, muscle rigidity, involuntary muscle jerks (myoclonus), overactive reflexes.
- Altered mental state: agitation, confusion, restlessness, and in severe cases, delirium.
Mild cases can look like simple anxiety or an intense psychedelic experience, which is part of what makes this genuinely tricky to self-diagnose during a session. Severe cases involve high fever, seizures, and cardiovascular instability that require emergency treatment.
Here’s the reassuring part, backed by actual data rather than guesswork: serious adverse events in the trial and survey literature on psilocybin plus SSRIs specifically are rare. The scoping review covering concomitant antidepressant and classic psychedelic use found the combination generally safe and tolerable across the studies it synthesized, while still flagging the shortage of large controlled trials as a real limitation. The escitalopram pretreatment RCT found reduced adverse effects, not increased ones, when the SSRI was on board.
Where things get more serious is polypharmacy. Case reports and clinical literature describing serotonin toxicity with psychedelics tend to involve additional interacting drugs, most notably lithium and MAOIs, rather than SSRIs in isolation. Lithium combined with serotonergic psychedelics has produced documented seizure risk and toxicity in case reports. MAOIs prevent the breakdown of serotonin entirely, and stacking that mechanism with a serotonin receptor agonist is one of the more dangerous combinations described in the literature, distinct from and generally riskier than a straightforward SSRI pairing.
A 2024 case report documenting psilocybin-assisted psychotherapy alongside serotonergic antidepressants found the combination tolerated during concurrent use. What stood out in that same report was a complication after abrupt discontinuation of one antidepressant: the person experienced a withdrawal-like worsening. That single case reinforces a theme this article keeps returning to: stopping an SSRI carelessly is arguably a bigger practical risk than the drug interaction itself.
When symptoms warrant emergency evaluation:
- Fever above 100.4°F combined with agitation or confusion
- Muscle rigidity, uncontrolled shaking, or jerking movements that don’t resolve as the trip progresses
- A racing heart rate that keeps climbing rather than leveling off
- Any combination of these symptoms appearing hours after ingestion, since serotonin syndrome onset is typically fast and progressive
If any of these appear, that’s an emergency room situation, not a “wait it out” situation. Tell emergency staff the full medication list and the timing of psilocybin ingestion; that detail changes how quickly they can identify serotonin syndrome versus a purely psychological reaction.
People with cardiac conditions, or those taking any medication that prolongs the QTc interval on an EKG, need an added layer of caution. Psilocybin can produce transient increases in heart rate and blood pressure on its own, and stacking that with a QTc-prolonging medication (certain antipsychotics, some antibiotics, and select antiarrhythmics) raises the theoretical risk of dangerous heart rhythm changes. This is a conversation for a cardiologist or prescriber, not a forum thread, before any psilocybin use is considered.
How Long Attenuated Effects Last and What That Means for Treatment
The figure showing about half from the retrospective survey deserves unpacking, because a single percentage hides a lot of texture. That number reflects self-reported experiences pooled across a wide range of settings, doses, and personal expectations, and the data is vulnerable to recall bias and the influence of expectation itself. Someone who read online that SSRIs “kill the trip” may unconsciously interpret an ordinary experience as weaker than it actually was. That doesn’t invalidate the finding, but it means the true biological attenuation rate could sit somewhere different from the reported one.
The RCT data adds a genuinely useful complication rather than simple confirmation. In the escitalopram pretreatment study, the reduction showed up mainly in adverse and uncomfortable effects, not across the board in positive subjective effects. If you extrapolate that finding, it suggests SSRIs might smooth out the rough edges of a psilocybin experience more than they flatten the entire thing, at least over a 14-day pretreatment window in healthy volunteers. Survey respondents describing a broadly “weaker” experience and a controlled trial showing selective softening of bad effects are not necessarily describing the same phenomenon, and reconciling that gap is exactly the kind of work the scoping review says still needs to happen.
Persistence after discontinuation is where the survey data gets most clinically relevant. That timeline lines up with what’s known about fluoxetine’s extended half-life and active metabolite, but the persistence effect shows up even with shorter-acting SSRIs, which points back toward receptor-level adaptation rather than simple drug clearance as the main driver.
The therapeutic implication is where this gets genuinely important for anyone considering psilocybin for depression. A weaker subjective experience is not automatically a weaker therapeutic outcome. Some researchers and clinicians argue that the intensity of the acute experience and the durability of any mood benefit are not the same variable, even though clinical trial designs have historically assumed a strong “peak experience” is necessary for benefit. That assumption is part of why most current trials require an SSRI washout at all: researchers want a clean signal, unmuddied by attenuation, to measure the drug’s effect. But that same design choice creates a research gap. It excludes exactly the population, people currently stable on an SSRI, who are most likely to actually consider this treatment in real life.
This is one of the more overlooked tensions in the field. Trial protocols optimize for scientific clarity by requiring washout, while real-world patients optimize for staying mentally stable by staying on their medication. Those two goals point in opposite directions, and no amount of survey data alone will resolve which approach produces better outcomes until more trials specifically enroll people who remain on SSRIs throughout.

What to Discuss With Your Prescriber Before Combining Psilocybin and SSRIs
Nothing in this article substitutes for an actual conversation with the person managing your medication, but you can walk into that conversation prepared. A clinician can only give you useful guidance if you hand over complete information, not a filtered version of your history.
- Full medication list, including over-the-counter supplements. St. John’s Wort, certain migraine medications (triptans), and some supplements carry their own serotonergic activity and compound the risk picture beyond SSRIs alone.
- Exact SSRI or SNRI name and how long you’ve taken it. Fluoxetine’s washout timeline looks nothing like sertraline’s, and duration of use affects receptor adaptation more than current dose does.
- Prior response to the antidepressant, including whether you’ve had side effects, partial relief, or treatment resistance. This shapes whether a prescriber sees continuing the SSRI as protective or as an obstacle to a meaningful experience.
- Cardiac history, especially arrhythmia, prior heart attack, or use of any QTc-prolonging medication.
- History of suicidal ideation or psychiatric hospitalization. This affects how a clinician weighs the risk of medication changes, not just the psilocybin decision itself.
Abrupt SSRI discontinuation carries its own well-documented risk profile independent of psilocybin entirely: discontinuation syndrome, rebound anxiety, and in some cases a genuine relapse into depressive symptoms. The case report describing withdrawal-like worsening after abrupt antidepressant discontinuation during psilocybin therapy is a small but pointed illustration of this exact risk. Clinical taper strategies are individualized based on the specific drug, dose, and duration of use, and they should always involve the prescribing clinician rather than a self-directed schedule pulled from an online forum.
Whether a clinician recommends continuing the SSRI or requires a washout period typically depends on a few factors: how psychiatrically stable you currently are, whether this is happening inside a formal clinical trial (where FDA guidance shapes strict protocol requirements) versus a personal decision outside a trial setting, and your personal history of relapse risk when medications change.
For anyone using psilocybin outside a supervised clinical setting, a few harm-reduction basics apply regardless of where you land on the SSRI question:
- Never combine psilocybin with MAOIs or lithium; these carry the most serious documented interaction risk in the literature.
- If you’re uncertain how your body will respond, start with a lower dose than you’d otherwise consider. Careful dosing guidance matters even more when medication interactions are a variable.
- Have a sober, trusted person present, and know where the nearest emergency care is located before you start.
- Don’t make any medication changes, starting, stopping, or adjusting doses, in the days immediately surrounding a planned psilocybin session without prescriber input.
Pro Tip: Write down your exact medication, dose, and last-taken date before your appointment. Prescribers can give faster, more specific guidance with concrete numbers in front of them instead of “I’m on some antidepressant.”
Where Fungipsilocybinmushroom Fits Into This Conversation
Fungipsilocybinmushroom exists to supply lab-tested psilocybin products and the education people need to use them thoughtfully, not to replace medical care. The product range spans a variety of strains, providing options rather than a one-size-fits-all product.
That range matters in the exact context this article covers. Someone who suspects their SSRI will blunt the experience has different considerations than someone with no medication history at all, and having strain and format options, including dosing guidance built for exactly this kind of decision, gives people room to make an informed choice rather than a guess.
A few things worth being direct about:
- Fungipsilocybinmushroom is an information and product supplier, not a medical provider, and nothing here replaces a conversation with a licensed prescriber.
- Educational resources on the site, including safety considerations beyond psychotropic medications, are built to complement clinical guidance, not substitute for it.
- Lab testing addresses product purity and potency; it does not, and cannot, screen for how your personal medication history will interact with a given dose.
If you’re on an SSRI and considering psilocybin, the product and the medical decision are two separate conversations. Get the second one settled with a clinician first.
A Frank Take on Access Versus Caution
The honest position here isn’t a comfortable middle ground, it’s a recognition that both sides of this debate are right about something. The people pushing for more accessible psilocybin research are right that mandatory SSRI washout excludes the exact population most likely to seek this treatment in real life. The people urging caution are right that the controlled-trial data is still thin, and thin data deserves humility, not confidence.
What frustrates me most about how this topic gets discussed online is the flattening. It’s not “SSRIs kill the trip” and it’s not “SSRIs are irrelevant.” It’s a receptor system that adapts over months, a drug interaction that’s mild for most people and genuinely dangerous in specific polypharmacy situations, and a research field that hasn’t caught up to the number of people already making this decision on their own. More trials that actually enroll people currently on SSRIs, rather than requiring washout as a default, would tell us far more than another survey of self-reported intensity ever could.
Until that data exists, the responsible path is unglamorous: read the actual studies, bring your full medication history to a real conversation with your prescriber, and don’t stop a medication that’s keeping you stable just to chase a stronger trip.
— Alex
Lab-Tested Products Built for an Informed, Careful Choice
Products are lab tested before delivery, so the variable being managed is medication history and dosing plan, not product purity. That distinction matters most for readers seeking a psilocybin experience without uncertainty about product contents.
If you’ve read this far and you’re weighing whether to combine psilocybin with your current SSRI, start with the dosing and safety guidance built specifically to help people calibrate dose against personal risk factors, including medication history. From there, browse strains suited to a therapeutic, lower-intensity approach if attenuation is a concern for you. Always follow your local laws on psilocybin possession and use, and loop your prescriber into any decision before you place an order.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
- Concomitant use of antidepressants and classic psychedelics: A scoping review
- Attenuation of psilocybin mushroom effects during and after SSRI/SNRI antidepressant use
- Acute Effects of Psilocybin After Escitalopram or Placebo Pretreatment in a Randomized, Double-Blind, Placebo-Controlled, Crossover Study in Healthy Subjects
- FDA issues first draft guidance on clinical trials for psychedelic drugs
- NIDA: Psilocybin (Magic Mushrooms)
Recommended
- Psilocybin Depression Treatment California: Your Complete Guide to Legal Mushroom Delivery Services and Therapeutic Options 2025
- Mushrooms for Anxiety – Natural, Calming, and Powerful Support for a Healthier Mind 2025
- Microdosing Psychedelics: Unveiling Remarkable Health Benefits and Therapeutic Potential 2026
- Discover the 5 Best Magic Mushroom Strains for Therapy – Transform Your Mind Today!