
Psychedelic Today
Clinicians: Which Psilocybin Mechanism Links Are Proven in Humans

Psilocybin itself does almost nothing. Once swallowed, it converts to psilocin, which binds cortical 5-HT2A receptors and triggers a fast cascade: cortical excitability rises, the default mode network loses its usual coherence, and signal entropy climbs across the brain. That acute disruption appears to open a window for molecular plasticity, involving BDNF and related signaling, that may outlast the trip itself and help explain why a single dose can shift mood and outlook for weeks.
TL;DR:
- Psilocybin is rapidly converted into psilocin in the gut, with peak plasma levels reaching around two hours after dosing, but subjective effects often peak slightly later.
- Differences in metabolism due to genetic variations in UGT, CYP2D6, and CYP3A4 enzymes lead to significant individual variability in psilocin levels, even with identical doses.
- Activation of 5-HT2A receptors on cortical pyramidal neurons causes acute brain network disruptions, including loss of default mode network coherence and increased inter-network connectivity.
- Neuroplasticity markers like BDNF and mTOR increase after dosing, but their role in long-term clinical benefits is still less certain than receptor-level and network effects.
- Combining precise pharmacokinetic, imaging, and electrophysiological data is critical for understanding psilocybin’s mechanisms and optimizing clinical protocols.
Psilocybin Mechanism 101: From Prodrug to Psychedelic Effect
Every explanation of the psilocybin mechanism starts with a simple pharmacological fact: psilocybin is a prodrug. It has to be converted before it does anything to the brain. That conversion, receptor activation, and the downstream neural reorganization it triggers form a chain with three well-supported links and at least two genuine gaps, and understanding where solid data ends and hypothesis begins matters if you’re trying to reason about this substance rather than just repeat talking points about it.
The first link is metabolic: dephosphorylation of psilocybin into psilocin, largely completed in the gut before the molecule ever reaches systemic circulation. The second is receptor pharmacology: psilocin’s affinity for 5-HT2A on cortical pyramidal neurons, which drives the acute subjective and electrophysiological effects. The third is network-level reorganization, visible on functional MRI as a marked loosening of the default mode network (DMN) and a corresponding increase in connectivity between networks that normally stay segregated. Layered on top of all three is a slower, less understood process: molecular plasticity that may persist long after psilocin has cleared the bloodstream.
Each of these stages has a different evidentiary weight. The metabolism and receptor pharmacology are grounded in decades of pharmacokinetic and radioligand-binding data. The network effects have strong, recent human imaging support. The plasticity story is compelling in animal models but still largely inferential in humans. That distinction runs through everything below.
Metabolism and Pharmacokinetics: How Psilocybin Becomes Psilocin
Psilocybin doesn’t cross into the brain as psilocybin. Non-specific alkaline phosphatases and esterases in the intestinal wall strip a phosphate group almost immediately after ingestion, a process largely completed in the jejunum and colon before the drug reaches systemic circulation in meaningful amounts. What arrives in the bloodstream, and eventually the brain, is psilocin, the actual psychoactive molecule.
Human PK-PD studies give a fairly consistent kinetic picture. Oral psilocin typically reaches peak plasma concentration (Tmax) around two hours after dosing, with concentrations rising in a dose-proportional fashion. A controlled dosing study using 15, 25, and 30 mg doses recorded mean peak psilocin concentrations of 11, 17, and 21 ng/mL, respectively, with elimination half-lives clustering between 1.4 and 1.8 hours and subjective effects lasting roughly 5.5 to 6.4 hours. Notably, body weight didn’t significantly shift these numbers in that cohort, which runs counter to the common assumption that dosing should scale tightly with body mass.
Pro Tip: If you’re trying to map a session’s timeline against the pharmacokinetics, remember Tmax and peak subjective intensity don’t align perfectly. Subjective effects tend to build for another 30 to 60 minutes after psilocin peaks in plasma, which is one reason session planning benefits from a dosing guide rather than a flat mg-per-kg formula.
Psilocin doesn’t just disappear once metabolized. It’s cleared through two main routes, and where those routes diverge is where individual variability enters the picture.
- Phase II glucuronidation by UGT enzymes, particularly UGT1A9 and UGT1A10, is the dominant clearance pathway, producing psilocin glucuronide as the major inactive metabolite.
- CYP2D6 and CYP3A4 contribute smaller Phase I oxidative pathways, and genetic polymorphisms in these enzymes can meaningfully shift exposure in either direction.
- A minor fraction of psilocin metabolism may involve monoamine oxidase, though this pathway is far less characterized than glucuronidation.
A systematic review of psilocybin pharmacokinetics confirms this UGT-dominant, CYP-assisted metabolic profile and flags substantial interindividual variability in clearance rates as a real confound in dose-response research. Two people taking an identical dose can land in noticeably different plasma ranges, which complicates any effort to standardize psilocybin dosing purely by weight or milligrams.
The pharmacodynamic payoff of all this kinetic detail is straightforward: plasma psilocin level correlates with the intensity of the experience. Studies pairing plasma sampling with subjective ratings and imaging find that as plasma psilocin rises, so does self-reported drug intensity, alongside measurable reductions in brain network integrity. The kinetics aren’t just pharmacological trivia; they’re a direct predictor of what’s happening in the network data covered further down.
Receptor Pharmacology: Why 5-HT2A Sits at the Center
Psilocin binds a handful of serotonin receptor subtypes, but 5-HT2A agonism is the receptor interaction that matters most for the acute psychedelic state. That’s not a guess; it’s demonstrated through pharmacological blockade experiments where pretreatment with 5-HT2A antagonists blunts or eliminates the subjective effects almost entirely, which is about as close to causal proof as receptor pharmacology gets.
Psilocin also binds 5-HT1A and 5-HT2C with meaningfully lower affinity than 5-HT2A. These secondary interactions likely modulate the overall response, particularly aspects of mood and anxiety during the session, but they don’t drive the core hallucinogenic signature the way 5-HT2A does.
The anatomical detail worth knowing: 5-HT2A receptors are densely expressed on layer V pyramidal neurons in the cortex, the large excitatory neurons that project both locally within cortical columns and to distant regions. Activating these receptors increases cortical excitability and appears to disrupt normal top-down signaling patterns, the kind of predictive, expectation-driven processing the cortex normally relies on to interpret sensory input efficiently. That disruption is a plausible cellular basis for why the psychedelic state feels less filtered and more raw.
- 5-HT2A agonism is the proximal, pharmacologically validated driver of acute hallucinogenic effects.
- 5-HT1A and 5-HT2C contribute secondary modulation, likely affecting mood and anxiety responses rather than perceptual intensity.
- Layer V pyramidal neurons carry the highest cortical density of 5-HT2A, making them the anatomical hub for psychedelic drug action.
- Activation here increases excitability and appears to loosen normal predictive, top-down cortical processing.
The frontier research question is whether all of this needs to happen together. 5-HT2A signals primarily through Gq protein coupling, but receptors like it can also engage alternative intracellular pathways, sometimes called biased signaling. Emerging work explores whether the Gq pathway can be pharmacologically separated from whatever downstream signaling drives lasting plasticity, essentially asking whether a molecule could trigger the therapeutic cascade without producing hallucinations at all.
That question isn’t academic curiosity. If biased signaling at 5-HT2A really does separate perceptual effects from plasticity-driving effects, it opens the door to non-hallucinogenic drug candidates built on the same receptor target. Whether that’s a net positive for psychedelic medicine, given how much of the therapeutic literature ties subjective intensity to outcome, is genuinely unresolved and worth watching over the next several years of pharmacology research.
Network-Level Disruption: The Default Mode Network Comes Apart

The clearest, most reproducible imaging finding in psychedelic neuroscience is what happens to the default mode network under psilocybin. The DMN, the set of interconnected regions active during self-referential thought and mind-wandering, loses internal coherence, while connectivity between networks that normally operate somewhat independently spikes upward.
A recent longitudinal high-frequency MRI study put actual numbers on the scale of this disruption: functional connectivity changes under high-dose psilocybin were more than three times greater than those observed under methylphenidate, a striking magnitude for a single-session pharmacological intervention. That same study tracked participants over weeks and found reduced hippocampus–DMN connectivity persisting well beyond the acute drug window, a detail with real clinical weight given the hippocampus’s role in memory and mood regulation.
- Within-network coherence in the DMN drops sharply during acute psilocin exposure.
- Between-network connectivity rises, effectively blurring boundaries that are normally well maintained.
- Hippocampus–DMN connectivity reductions have been observed persisting for weeks post-dose.
- The magnitude of connectivity change correlates with plasma psilocin level and subjective intensity ratings.
This is where the pharmacokinetics and the imaging data connect directly. Studies pairing plasma sampling with resting-state fMRI find that plasma psilocin level correlates negatively with DMN integrity and positively with the degree of network desegregation, giving researchers a rare direct line from a measurable blood concentration to a measurable brain-state change.
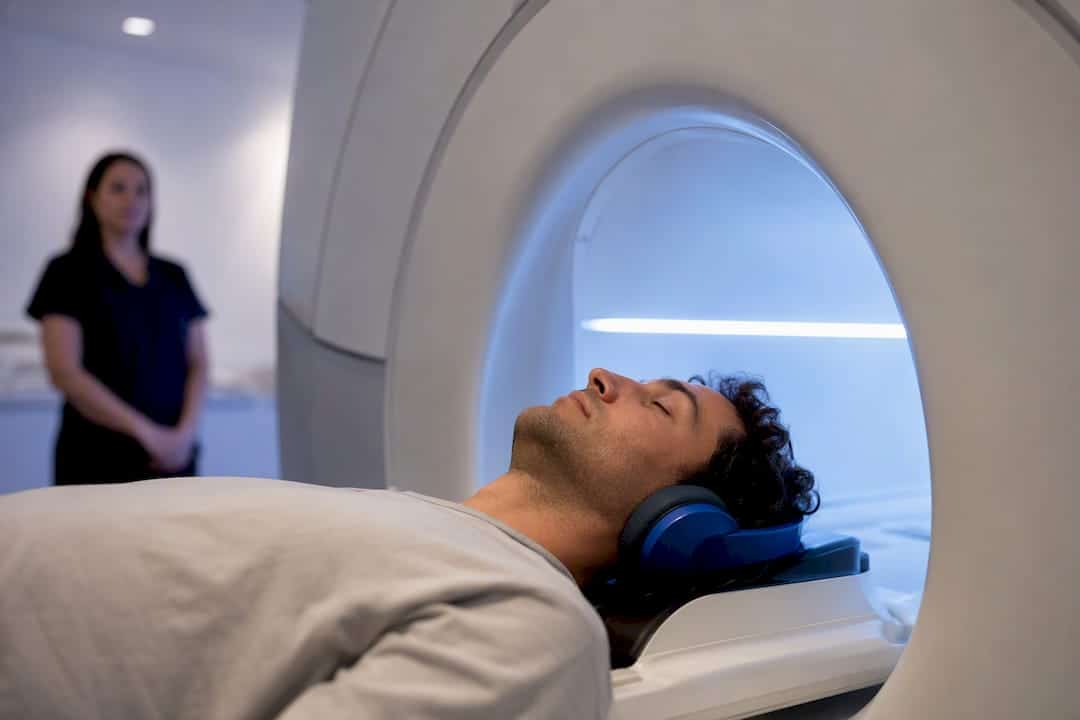
None of this happens in a vacuum, though. Task state, prior expectation, and the physical and social environment (the “set and setting” language common in psychedelic research) modulate how large these connectivity shifts turn out to be. A person lying still in an MRI scanner with headphones and a research assistant nearby is not experiencing the same context as someone in an unfamiliar setting, and network-level effects appear sensitive to that context in ways researchers are still working to quantify precisely.
Brainwave and Electrophysiology Signatures Under Psilocybin
Functional MRI shows where connectivity changes; electrophysiology shows how fast they happen. EEG and MEG studies of the acute psilocybin state consistently report broadband reductions in alpha power, the dominant resting rhythm typically strongest over posterior cortical regions during relaxed wakefulness. Alongside that, measures of neural signal complexity and entropy tend to rise, a pattern some researchers interpret as the brain moving away from its usual, more predictable oscillatory patterns toward a less constrained state.
Preclinical electrophysiology fills in cellular-level detail that human scalp recordings can’t capture. Local field potential and single-unit recordings in animal models show altered firing patterns and disrupted synchrony following 5-HT2A receptor activation, generally consistent with the desynchronization seen at the network level in human imaging. This is where the temporal resolution advantage of electrophysiology earns its place in the mechanistic story: fMRI captures network states averaged over seconds, while LFP recordings can track millisecond-scale shifts in firing and phase relationships that plausibly explain how a receptor-level event cascades into a network-level one so quickly.
- Alpha power reductions are among the most consistently replicated EEG findings during acute psilocybin effects.
- Increases in signal entropy and complexity metrics accompany that alpha suppression.
- Animal LFP and single-unit studies show altered firing synchrony tied directly to 5-HT2A activation.
- Electrophysiology’s fine temporal resolution helps bridge millisecond receptor events to slower network-level imaging findings.
The gap here is translational rather than conceptual. Researchers have a reasonably clear picture of what 5-HT2A activation does to cortical neurons and a reasonably clear picture of what happens to large-scale networks, but the precise electrophysiological signature that predicts a specific subjective experience, ego dissolution versus visual distortion versus emotional release, remains largely unmapped. Closing that gap is one of the more tractable near-term research goals in the field.
Neuroplasticity Beyond the Trip: BDNF and Synaptic Growth
The acute hallucinogenic signaling described above is fast and receptor-driven. What may sustain benefits after the drug clears is a slower, molecular process, and this is where the psilocybin mechanism story shifts from electrophysiology to cell biology.
Animal studies and some human biomarker proxies point toward increased brain-derived neurotrophic factor (BDNF) expression and mTOR pathway activation following psychedelic dosing, both associated with synaptic growth and dendritic spine formation. Reviews synthesizing this literature describe these neurotrophic cascades as mechanistically distinct from the acute 5-HT2A signaling that produces the trip itself, meaning the molecule that gets someone high and the molecule pathway that potentially helps their depression may not be the same thing wearing different hats.
That distinction matters for a practical reason: sustained mood improvement likely depends on more than the biology alone. Structured psychotherapeutic integration around the dosing session appears to compound whatever plasticity window the drug opens, which is consistent with why most clinical protocols pair dosing with preparation and follow-up therapy rather than treating the substance as a standalone intervention.
- Preclinical studies report elevated BDNF and mTOR activity following psychedelic exposure, both linked to synaptic growth.
- These neurotrophic mechanisms appear distinct from the acute 5-HT2A hallucinogenic pathway.
- Durable mood benefits likely depend on plasticity cascades combined with psychotherapeutic integration, not the drug alone.
- Dose and frequency thresholds required for lasting plastic change in humans remain undefined.
Pro Tip: Don’t conflate “neuroplasticity” with “the trip felt profound.” The molecular plasticity markers researchers track (BDNF expression, dendritic spine density) are measured independently of subjective reports, and the two don’t always move in lockstep in animal models, a reminder that intensity of experience and depth of biological change aren’t guaranteed to be the same thing.
What’s genuinely unresolved is dosing frequency for durable change. A single high dose, repeated moderate doses, and microdosing regimens likely engage these plasticity pathways differently, and human data mapping dose and frequency directly onto structural brain change is still thin. That gap sits near the top of most researchers’ priority lists.
What Animal Models and PBPK Simulations Reveal
Physiologically based pharmacokinetic (PBPK) models take PK data a step further by simulating drug concentration across multiple body compartments simultaneously rather than just tracking plasma levels. A recent PBPK model spanning mice, rats, and humans structures the simulation around eight compartments, including brain, liver, kidney, gut, and adipose tissue, and incorporates UGT-mediated metabolic parameters fitted from in vitro enzyme kinetics data.
One notable output from that modeling: predicted brain psilocin concentrations can exceed plasma concentrations, consistent with psilocin’s lipophilicity and its efficient crossing of the blood-brain barrier. That’s a useful correction for anyone assuming plasma levels are a direct proxy for brain exposure; the model suggests brain tissue may actually be more concentrated than blood at certain time points.
- PBPK models use multi-compartment structures to simulate concentration in brain, liver, kidney, and other tissues simultaneously.
- Predicted brain concentrations of psilocin can exceed plasma concentrations at relevant time points.
- Cross-species scaling relies on allometric adjustments, which introduce real uncertainty when extrapolating rodent findings to human dosing.
- Several minor Phase I metabolic pathways remain undercharacterized, leaving gaps in even well-built PBPK frameworks.
Translation from animal to human data always carries a cost, and psilocybin research is no exception. Allometric scaling and in vitro to in vivo extrapolation (IVIVE) are standard pharmacology tools, but they’re approximations, not certainties, and the metabolic and receptor-density differences between rodent and human cortex mean behavioral findings in mice need to be read as mechanistically suggestive rather than directly predictive of human dosing outcomes.
From Receptor to Recovery: How Mechanism Shapes Clinical Protocols
The pharmacokinetic timeline maps directly onto how therapeutic sessions get structured. Subjective onset typically begins within one to two hours of dosing, aligning closely with psilocin’s Tmax, peak effects cluster around the two-hour mark, and the overall subjective experience commonly runs five to six hours before resolving. That timeline is why clinical and guided protocols block out a full day for a dosing session rather than a couple of hours, and it’s the same logic behind structured dosing guidance built around realistic session windows rather than rushed timing.
The more interesting clinical hypothesis is that the acute network desynchronization described earlier creates a temporary window of heightened plasticity, one where a person’s usual cognitive patterns and self-referential narratives are less rigidly enforced by the DMN. If that window is real and clinically exploitable, psychotherapy delivered during or shortly after that period may help consolidate insight into something that outlasts the drug’s pharmacokinetic clearance.
Whether the subjective experience itself is a necessary ingredient for the clinical benefit, or just a side effect of the biology that actually does the work, is one of the most contested open questions in the field. It’s the exact question biased-signaling research is trying to answer at the receptor level: if a compound could activate the plasticity-relevant signaling cascade at 5-HT2A without producing the perceptual disruption, would the therapeutic outcome hold up? Nobody has a confirmed answer yet.
- Onset of subjective effects generally begins one to two hours post-dose, tracking psilocin’s Tmax.
- Peak subjective intensity clusters around the two-hour mark, slightly trailing peak plasma concentration.
- Total subjective effect duration commonly runs five to six hours in controlled dosing studies.
- Acute network desynchronization may open a transient plasticity window that structured psychotherapy could help consolidate.
Given all of this, the strongest clinically relevant research designs pair pharmacokinetic sampling with imaging and standardized outcome measures in the same cohort, rather than studying PK, brain imaging, and clinical results in separate, disconnected samples. That kind of paired design is still the exception rather than the rule in published psychedelic trials.
Safety Profile, Individual Variability, and Drug Interactions
Mechanistic understanding of psilocybin carries direct safety implications, particularly around what else is in someone’s system when they dose. A handful of interaction classes deserve specific attention from anyone researching or overseeing psilocybin use.
- SSRIs and other 5-HT2A-relevant medications can blunt subjective intensity and shift the physiological response to psilocin, since these drugs compete for or downregulate the same receptor system psilocin depends on.
- Lithium and certain mood stabilizers carry case-report-level associations with serious adverse events, including seizures, when combined with psychedelics, which is a strong argument for conservative exclusion criteria rather than case-by-case judgment calls.
- CYP2D6 and CYP3A4 polymorphisms shift individual exposure levels meaningfully. A systematic review of psilocybin pharmacokinetics documents this variability directly, and it means two people at an identical dose can end up with different effective exposure based on genetics alone.
- UGT enzyme activity differences compound the CYP-related variability, since glucuronidation is the dominant clearance pathway for psilocin and differs across individuals.
For researchers and clinicians, the practical takeaway is straightforward: a thorough medication review before any planned dosing session isn’t optional caution, it’s a mechanistic necessity given how many common psychiatric medications intersect with the same serotonergic and metabolic systems psilocin relies on. Anyone weighing safety questions in more depth should consult dedicated safety-focused resources alongside a qualified medical provider, particularly when other medications are already part of the picture.
Grading the Evidence: What We Know and What’s Still Guesswork
Not every piece of the psilocybin mechanism rests on equally solid ground, and it’s worth being explicit about the hierarchy.

The strongest evidence sits at the receptor level. 5-HT2A agonism as the driver of acute effects is about as well established as pharmacology gets for a psychoactive compound, backed by blockade studies and decades of binding data. Human imaging showing DMN desegregation and increased network entropy is nearly as solid, replicated across multiple independent cohorts and imaging modalities.
The middle tier covers pharmacokinetics and PBPK modeling. PK-PD relationships linking dose to plasma psilocin and subjective intensity are well characterized in humans, and PBPK models predicting tissue-level exposure are methodologically sound but still carry the inherent uncertainty of cross-species extrapolation.
The weakest tier, and the most clinically important, is the causal chain connecting molecular plasticity markers to durable clinical outcomes in humans, and the question of whether hallucinogenic and therapeutic signaling can be cleanly separated. Priority research should focus on biased-signaling ligand development, longitudinal studies pairing PK sampling with repeated imaging in the same subjects, and standardized electrophysiological protocols that can be compared across labs rather than each using bespoke methods.
What the Evidence Actually Adds Up To
Three things stand out after working through this mechanism end to end. First, the chain from prodrug conversion to receptor binding to network disruption is genuinely well supported by human data, not just animal extrapolation dressed up as consensus. Second, the plasticity story, while biologically plausible and consistent with animal findings, is still the weakest empirical link when it comes to humans, and anyone treating BDNF-driven synaptogenesis as a settled explanation for lasting clinical benefit is overstating the evidence. Third, biased signaling research deserves more attention than it currently gets in public discussion, because it’s the one research direction that could eventually answer whether the trip and the treatment are actually the same thing.
If I were setting research priorities, paired PK-imaging designs and conservative medication screening protocols would sit at the top of the list, not because they’re novel, but because too much existing work still studies these pieces in isolation. Mechanistic claims about psilocybin move fast in public conversation; the underlying data should get equal scrutiny before those claims get translated into clinical promises.
— Alex
Key Studies and Reviews Worth Reading
For readers who want to verify the claims above directly, these sources carry the primary weight of the evidence discussed:
- Psilocybin desynchronizes the human brain: longitudinal MRI mapping of connectivity change and persistent hippocampus-DMN effects.
- Pharmacokinetics and Pharmacodynamics of Oral Psilocybin Administration in Healthy Participants: dose-proportional Cmax, Tmax, and half-life data.
- Pharmacokinetics of Psilocybin: A Systematic Review: metabolic enzyme pathways and interindividual variability.
- Development of a PBPK model of psilocybin/psilocin from Psilocybe cubensis in mice, rats, and humans: compartmental modeling and cross-species scaling.
- Biased signaling at 5-HT2A receptor: separating hallucinogenic and therapeutic pathways: emerging receptor-signaling research.
- Neural mechanisms underlying psilocybin’s therapeutic potential: review synthesizing receptor and plasticity mechanisms.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
- Psilocybin desynchronizes the human brain
- Pharmacokinetics and Pharmacodynamics of Oral Psilocybin Administration in Healthy Participants
- Pharmacokinetics of Psilocybin: A Systematic Review
- Development of a PBPK model of psilocybin/psilocin from Psilocybe cubensis in mice, rats, and humans
- Biased signaling at 5-HT2A receptor: separating hallucinogenic and therapeutic pathways
Recommended
- Psilocybin Depression Treatment California: Your Complete Guide to Legal Mushroom Delivery Services and Therapeutic Options 2025
- Microdosing Psychedelics: Unveiling Remarkable Health Benefits and Therapeutic Potential 2026
- Can Psychedelic Mushrooms Help With Anxiety | Psychedelic Mushrooms For Sale 1 0z | Where to buy Mushrooms for sale online

2:1:1 PF Tek Substrate Ratio for Beginners That Colonizes Reliably
The classic PF Tek substrate ratio is 2 parts vermiculite to 1 part brown rice flour to 1 part water. For a standard half-pint jar, that works out to about 1/2 cup vermiculite, 1/4 cup brown rice flour, and 1/4 cup water. Mix the wet vermiculite first, fold in the flour, fill jars loosely, cap with a 1/2 inch dry vermiculite layer, sterilize, cool completely, inoculate, and let the jars sit in the dark.
TL;DR:
- Using organic brown rice flour reduces the risk of fungicide residue that can halt colonization, making it worth the extra cost.
- Proper mixing involves soaking vermiculite, testing its moisture, then folding in the flour gradually to avoid clumps and dead zones.
- Sterilization with a pressure cooker at 15 psi for 45 minutes is more reliable than steaming, which risks contamination due to uneven heat.
- Inoculate with 1 to 2 cc of spores per jar, working in a sterile environment, and seal injection sites with micropore tape for optimal results.
- Full colonization typically takes 2 to 4 weeks at 70°F to 80°F, with healthy mycelium appearing as fluffy white growth and contamination showing as colored patches.
What Goes Into a PF Tek Substrate Recipe?
That 2:1:1 ratio isn’t arbitrary. Vermiculite holds water and creates air pockets mycelium needs to breathe; brown rice flour (BRF) supplies the nutrient base fungi actually digest. Get the water content wrong in either direction and you’re either drowning the substrate or starving it, both of which stall colonization before it starts. This exact recipe and its per-jar breakdown show up consistently across step-by-step PF Tek guides, which is why it’s become the default starting point for anyone new to jar cultivation.
Here’s the exact breakdown for a single half-pint (8 oz) wide-mouth jar:
- Vermiculite: 1/2 cup (roughly 120 ml)
- Brown rice flour: 1/4 cup (roughly 60 ml)
- Water: 1/4 cup (roughly 60 ml), plus a bit more for the wet vermiculite portion before mixing
- Dry vermiculite for the top layer: an additional 2 to 3 tablespoons per jar, kept separate and never wetted
Most beginners don’t stop at one jar. Once you know you’ll be running a batch, scale the recipe up rather than mixing single jars over and over.
A few ingredient notes make a real difference in outcome. Organic brown rice flour is worth the extra cost when you can find it, since some growers report conventional flour occasionally carries trace fungicide residue that can slow or inhibit colonization. Use coarse or medium vermiculite rather than the fine horticultural grade sold for seed starting; it holds structure better and won’t compact into mud. Tap water is fine in most municipal systems, but if your water is heavily chlorinated, let it sit out overnight or use filtered water instead.
Gypsum and coffee grounds show up in some advanced PF Tek variations as small nutrient boosters. Neither is required, and for a first run, skip both. Get the base recipe working before you start experimenting with additives. Jar shape matters more than most beginners realize, too. Half-pint, wide-mouth jars without shoulders release finished cakes cleanly; jars with a lip or shoulder near the top tend to trap the cake and cause tearing when you try to dunk and roll it later.

Pro Tip: Measure your dry ingredients before adding water, not after. Once vermiculite is wet, it’s nearly impossible to eyeball how much BRF you’re actually adding by volume.
How Do You Mix and Fill PF Tek Jars?
Mixing order matters more than most first-timers expect, and getting it backward is one of the most common reasons a batch never colonizes.
- Wet the vermiculite first. Combine your measured vermiculite with the water in a bowl and let it sit for a couple of minutes so it absorbs evenly.
- Run the squeeze test. Grab a handful and squeeze firmly. You want only a few drops of water to escape, no more. If water streams out, you’ve added too much; add a spoonful of dry vermiculite to correct it. If nothing comes out at all and the mix feels crumbly, add water a teaspoon at a time.
- Fold in the brown rice flour gradually. Add it in two or three stages, mixing between each addition, rather than dumping it all in at once. This avoids the dense flour clumps that create dead zones mycelium can’t colonize.
- Fill jars loosely. Spoon the mixture in without pressing or tamping. Packing substrate tightly is one of the most common beginner mistakes because compacted substrate blocks gas exchange and mycelium simply stalls inside a jar that looks fine from the outside.
- Leave headspace and wipe the rims. Stop filling about 1/2 inch below the jar’s shoulder, then wipe any substrate off the rim and threads with a clean, damp cloth. Substrate on the rim becomes a contamination bridge once the lid goes back on.
- Add the dry vermiculite cap. Spoon a 1/2 inch layer of dry (unwetted) vermiculite on top and level it gently. Don’t compress this layer either; it needs to stay loose to do its job.
- Prepare the lids. Drill or punch three to four holes around the lid, about 1/4 inch in diameter, spaced evenly. Cover each hole with a small piece of micropore tape or a folded strip of aluminum foil before sterilizing, then screw the lids on loosely, not fully tight, to allow steam to enter during the cook.
Pressure Cooker vs. Steam Pot: Which Sterilization Method Works Better?
A pressure cooker running at 15 psi for 45 minutes is the preferred sterilization method for PF Tek jars, and for good reason: it hits a temperature and pressure combination that reliably kills contaminant spores throughout the substrate, not just on the surface.
Stovetop steaming is the low-equipment fallback. Set jars on a rack or folded towel inside a large pot, so they never touch the metal bottom directly, add a few inches of water, cover tightly, and steam for 60 to 90 minutes. It works, but it carries a higher contamination risk because steaming doesn’t reach the same sustained internal temperature a pressure cooker does. If you go this route, check the water level periodically; a pot that runs dry mid-cook is one of the most common causes of a failed steam sterilization.
A few operational details separate a clean cook from a wasted batch:
- Never let jars touch the pressure cooker or pot’s metal bottom directly. Temperature shock is the leading cause of cracked jars.
- Let pressure release naturally after the timer ends. Venting too fast causes a sudden pressure drop that can crack glass or blow substrate through the lid holes.
- Let jars cool completely to room temperature before inoculating. Warm substrate creates condensation inside the jar, and that moisture is exactly what contaminants need to establish.
- Loosely cover cooling jars with foil to keep airborne dust and mold spores off the lids while they sit.
Colonization timelines run 2 to 4 weeks under ideal conditions, and ideal incubation sits between 70°F and 80°F (21°C to 27°C). Cooking your substrate properly is what makes that window achievable instead of aspirational.
How Much Spore Solution Do You Inject Per Jar?
Inoculation is the step where sterile technique either pays off or falls apart, so treat it with the same care you gave sterilization.
- Sterilize your needle. Flame it with a lighter until it glows, then let it air cool for 10 to 15 seconds. A hot needle will kill your spores on contact.
- Shake the syringe. Spores settle at the bottom of the solution, so agitate the syringe well before drawing or injecting to distribute them evenly.
- Inject 1 to 2 cc per jar, split across the available holes so mycelium establishes from multiple points rather than one corner.
- Work in a still-air box or a draft-free room. A dedicated still-air box (SAB) cuts down airborne contamination significantly compared to open-air inoculation, though a clean, closed room with no fans running is workable for a first attempt.
- Reseal each injection hole with a fresh piece of micropore tape immediately after injecting.
The dry vermiculite cap you added earlier isn’t just filler. It functions as a physical filter and humidity buffer, trapping airborne contaminants before they reach the substrate below while keeping the surface consistently humid for mycelium to push through. That’s also why disturbing it, tapping the jar hard, or scraping the top layer during handling is a leading contamination vector for beginners. Leave it alone once it’s in place.
How Long Does PF Tek Take to Colonize?
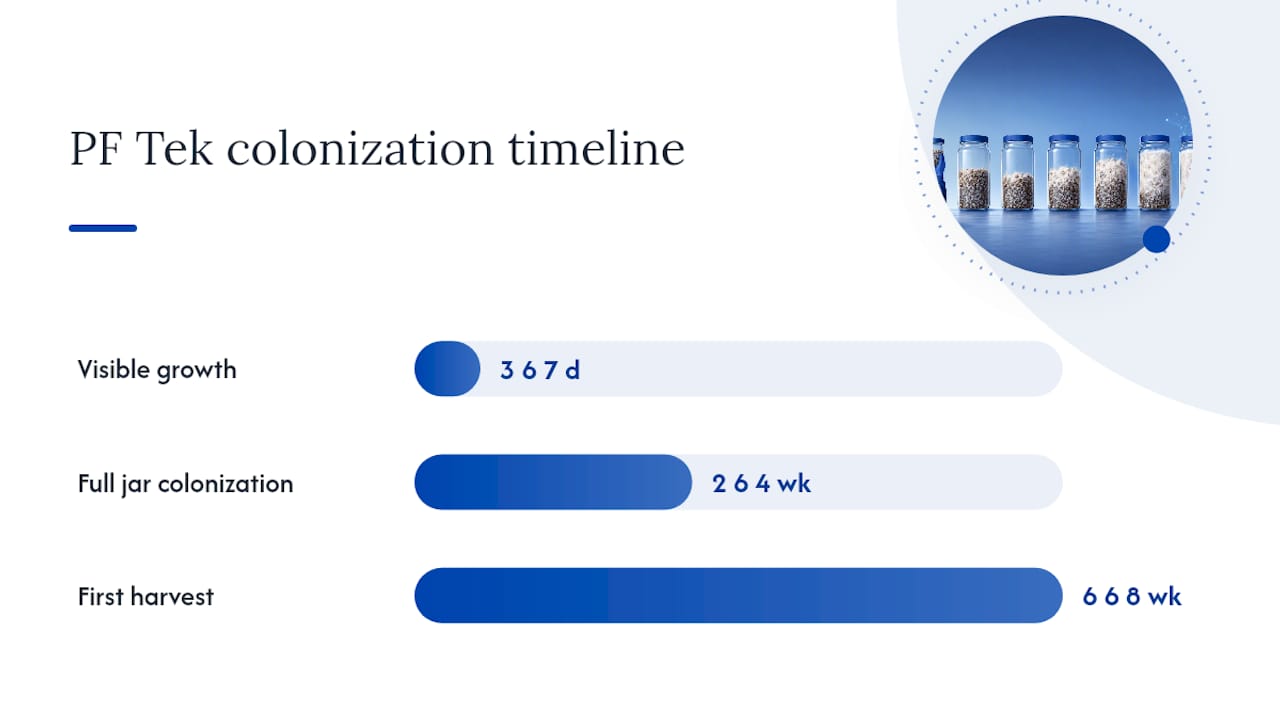
Expect visible white growth around the injection sites within 3 to 7 days. Full colonization of the jar typically takes 2 to 4 weeks, and the entire process from inoculation to first harvest usually runs 6 to 8 weeks when temperatures stay in range.
That temperature range, 70°F to 80°F (21°C to 27°C), isn’t a suggestion. Colder incubation slows growth and gives contaminants more time to establish before mycelium can outcompete them. Hotter than 80°F speeds colonization but raises the odds of bacterial issues, especially in a substrate that’s slightly too wet.
Healthy colonization looks like consistent, fluffy white growth radiating outward from each injection point, eventually connecting into a solid white mass. You’ll often see thicker white cords called rhizomorphs pushing through the substrate; that’s a strong sign of vigorous growth, not a problem.
Contamination shows up as color, and color is the tell:
- Green, blue-green, or black fuzzy patches usually mean Trichoderma or Penicillium mold.
- Bright pink or orange slime typically signals bacterial contamination, often from a substrate that was too wet.
- Gray, web-like growth that spreads fast and thin is cobweb mold, a common but usually manageable contaminant if caught early.
If a jar shows no growth and no contamination after two weeks, check your temperature and moisture before assuming the jar failed. Colonies that stall from cold or dryness often resume once conditions are corrected. Never open the jar to “help” mycelium along; that’s an open invitation for contamination. If you see any spreading color, discard that jar rather than trying to salvage it.
Dunking, Rolling, and Setting Up for Fruiting
Once a jar is fully colonized, white mycelium wall to wall with no dry substrate visible, it’s ready to come out and become a fruiting cake.
- Dunk the cake for 12 to 24 hours in cool, non-chlorinated water, refrigerating it during the soak. This rehydrates the cake and typically improves yield on later flushes. If the cake floats, weigh it down gently with a clean plate; don’t force it under with pressure that could crack it.
- Roll the wet cake in dry vermiculite, coating it evenly on all sides, about 1/8 inch thick. This holds moisture at the surface without smothering it.
- Set up a shotgun fruiting chamber. A clear plastic tote with a few inches of moist perlite in the bottom, holes drilled around the sides, provides the humidity and fresh air exchange cakes need to pin. Mist the chamber walls once or twice daily and fan it briefly to exchange stale air.
- Give it indirect light on a normal day/night cycle; mushrooms don’t need bright light, but a schedule helps trigger pinning.
Most cakes produce two to three flushes, with each flush a week or two apart. Dunk again between flushes to rehydrate.
What Should You Do When Something Goes Wrong?
Most PF Tek failures trace back to one of a handful of repeatable mistakes, and catching them early saves the rest of your batch.
- See green, black, or pink growth? Isolate that jar immediately, seal it in a bag before opening anywhere near your other jars, and discard it. Don’t try to cut out contamination and save the substrate; PF Tek jars are small enough that it’s rarely worth the risk.
- Substrate feels compacted or waterlogged? Use less water next batch and stop tamping the substrate down while filling. This is one of the most frequently repeated errors among first-time growers.
- Growth has stalled with no contamination visible? Check incubation temperature first, then moisture. A jar sitting in a chilly closet will colonize far slower than one held at 75°F.
- Cobweb mold (gray, thin, fast-spreading) is manageable if you catch it in the first day or two; some growers scrape it out carefully, though isolating the jar is the safer call for beginners.
- Bacterial blotch (yellow or orange wet-looking patches with a sour smell) almost always means the substrate was too wet going into sterilization. Adjust your water ratio down slightly next time.
A few hygiene habits reduce contamination rates across the board: wipe down your work surface with isopropyl alcohol before every session, wash hands thoroughly, and avoid working near open windows, fans, or high-traffic areas of the house.
Pro Tip: Keep a simple log of your water measurements and sterilization times for each batch. When something goes wrong, that log is the fastest way to figure out what changed.
Why PF Tek Still Beats Fancier Methods for Beginners
PF Tek gets dismissed by more advanced growers who’ve moved on to monotubs and bulk substrate, and for higher-volume growing, they’re right to make that switch. But writing off PF Tek as outdated for a beginner misses the actual point of the method. It’s forgiving. Low-nutrient substrate, small jar volumes, and basic kitchen equipment mean a mistake in ratio or timing costs you one jar, not an entire tub of substrate.
The mistake I see repeated most isn’t a measurement error. It’s impatience. People check jars daily, tap the glass, hold jars up to grow lights every few hours looking for progress, and in doing so they introduce far more contamination risk than a slightly-off water ratio ever would. Colonization on a good jar looks almost boring for the first ten days. That’s normal.
The other thing worth saying plainly: laws around psilocybin cultivation and possession vary significantly by country, state, and even city, so check your local regulations before starting any grow. Fungipsilocybinmushroom’s grow kit guide and lab-tested product line exist precisely because plenty of home growers want a proven, quality-controlled starting point rather than reinventing the wheel with each batch.
— Alex
Want Fewer Steps and Higher Success Odds?
If measuring vermiculite and babysitting a pressure cooker sounds like more equipment risk than you want on your first run, a ready-to-fruit grow kit skips the substrate prep entirely. Fungipsilocybinmushroom’s 100% mycelium grow kit ships fully colonized, so you’re starting at the fruiting stage instead of the inoculation stage, with far less exposure to the contamination risks that trip up first-time PF Tek growers.
The kit arrives with clear setup instructions and the accessories needed to get your first flush going, and it’s built specifically for beginners who want a tested, consistent result without troubleshooting a failed jar mid-batch. If you’ve already run PF Tek and want to compare notes on colonization speed and flush size, the B+ mycelium grow guide walks through what a faster-colonizing strain looks like in practice. Check current availability and place your order through the grow kit product page to get your next batch started with less guesswork than a first PF Tek run typically involves.
Where to Read More on PF Tek Technique
The PF Tek v2 thread on Shroomery remains the most detailed original source for troubleshooting stalled jars and reading incubation timelines correctly. DoubleBlind Magazine’s guide adds historical context on why the method became the standard entry point for home cultivation. For side-by-side photos of substrate consistency and jar setups, Mushroom Growing Tips’ PF Tek walkthrough is worth bookmarking, and SporeLab’s technique page covers sterilization variations in more depth than most beginner guides attempt.
This article is general information, not a substitute for advice from a qualified lawyer. Consult a qualified legal professional about your own circumstances before acting on anything here.
Sources
- Shroomery
- A Mycologist’s Guide to the PF Tek Method — DoubleBlind Magazine
- PSILOCYBE CUBENSIS GROWING TECHNIQUES (PF TEK) — SporeLab
- Growing mushrooms at home — Mother Earth News
Recommended

Psilocybin and PTSD: A Consumer’s Safety and Dosing Guide
Consumer psilocybin and PTSD self-care, taken outside a clinical setting, can be a reasonable option for some adults managing symptoms through self-directed healing—but only after ruling out serious health risks first. If you have a personal or family history of psychosis, bipolar disorder, or you take lithium or an MAOI, psilocybin and PTSD recovery is not a safe combination right now, full stop. For everyone else, three powerful steps unlock your path forward:
Screen yourself honestly against the contraindications below, and talk to a doctor if anything applies to you. Use a lab-tested product with a certificate of analysis, or wait until you have one. Plan your set and setting in advance, including who (if anyone) will be with you.
TL;DR:
Individuals with a personal or family history of psychosis, bipolar disorder, or taking lithium or MAOIs should avoid psilocybin and PTSD treatment entirely due to severe mental health risks. Microdosing doses are generally 0.1 to 0.3 grams, but current research shows limited evidence of consistent benefits for psilocybin and PTSD or anxiety symptom relief. Ensuring a lab-tested product with a certificate of analysis and a safe, private setting with a trusted sitter are crucial steps before any psilocybin and PTSD journey.
High blood pressure, heart arrhythmias, seizure disorders, pregnancy, or breastfeeding raise significant safety concerns and require medical consultation before exploring psilocybin and PTSD options. Dosing accuracy relies on dry weight measurement with a precise scale, and home-grown mushrooms can vary significantly in potency, risking unpredictable effects that undermine safe psilocybin and PTSD self-care.
Psilocybin PTSD Safety: Contraindications and Medication Risks

Some adults with PTSD-related symptoms should not use psilocybin under any circumstances. A personal or family history of psychosis, schizophrenia, or bipolar I disorder tops that list. Psilocybin can trigger a manic episode or a psychotic break in someone predisposed to either, and that risk does not shrink at a low dose.
Medication interactions matter just as much. Lithium combined with psilocybin is considered a severe interaction risk and should be avoided, and clinicians flag it as one of the more dangerous pairings in psychedelic use, according to Psychiatric Times. MAOIs carry similar severity. SSRIs and SNRIs, common first-line PTSD medications, tend to blunt psilocybin’s effects rather than cause acute danger, but the interaction is still unpredictable enough that stopping cold on your own is a bad idea. Tramadol raises seizure risk when mixed with psilocybin and should be avoided entirely during a session.
A few more flags worth knowing:
- Uncontrolled high blood pressure or a history of heart arrhythmia (psilocybin transiently raises heart rate and blood pressure).
- A seizure disorder of any kind.
- Pregnancy or breastfeeding, where there’s no safety data at all.
Watch for a racing heart that doesn’t settle, chest pain, or a panic response that isn’t resolving with grounding techniques. Those are reasons to stop, call for help, and treat it as a medical event, not just a rough trip. The NCCIH notes that psilocybin’s effects are genuinely variable person to person, and supervised clinical dosing is a different context entirely from taking it alone at home.
Dosing Psilocybin for PTSD Symptom Relief: Ranges and Microdosing Evidence
Dry weight is the only unit that matters for dosing dried Psilocybe cubensis. Fresh mushroom weight is meaningless because moisture content varies wildly between batches. Common consumer ranges break down roughly like this, according to harm-reduction dosing guides from Rave Wellness:
- Threshold dose: 0.25 to 0.5 grams dried, enough to notice subtle mood or perceptual shifts.
- Common/moderate dose: 1 to 2.5 grams dried, the range most people associate with a full experience.
- Strong dose: 3.5 grams and above, reserved for experienced users in a controlled setting.
- Microdose: 0.1 to 0.3 grams dried, sub-perceptual by design.
Potency swings dramatically by species and even by batch within the same species, so treat any chart as a starting point, not gospel. A milligram scale accurate to 0.01 to 0.1 grams is non-negotiable if you’re microdosing. Start at the lowest end of any range, wait at least two hours before deciding whether to redose, and never stack doses out of impatience.
On the evidence: microdosing for anxiety or PTSD symptoms is popular, but the science is thin. A randomized, placebo-controlled trial found subjective effects without consistent cognitive or wellbeing benefits, meaning people felt something, but measurable improvement in mood or thinking didn’t hold up against placebo. A 2026 systematic review reached a similar conclusion: heterogeneous practices and low-certainty evidence across studies. If you microdose, favor an encapsulated product with a certificate of analysis so your dose is at least consistent, even if the benefit remains unproven. Our dosing guide covers measurement tools and schedules in more depth.
Set, Setting, and Integration for a PTSD-Focused Session
Preparation matters more for someone processing trauma than for a recreational user, because psilocybin can intensify whatever emotional material is already close to the surface. Set your intention beforehand: what are you hoping to work through, and what would a “good enough” outcome look like? Choose a day with nothing scheduled after, and check that your baseline mood is stable rather than in active crisis.
Setting checklist:
- A private, familiar indoor space with a lock on the door.
- Water, a blanket, snacks, and a calm playlist queued up in advance.
- Phone off or in another room, except for an emergency contact method.
- A trusted sitter present, ideally someone who has done this before or at least knows basic grounding language.
A sitter’s job is mostly to stay quiet and available. If things get difficult, a simple script works better than improvised comfort: “You’re safe. This is temporary. I’m right here.” Crowdsourced research on first psychedelic experiences found that exactly this kind of preparation, dose measurement, and sitter presence correlates with fewer challenging experiences and better outcomes overall.
Pro Tip: If a wave of fear or grief hits hard, don’t fight it. Harm-reduction counselors call this “surrender, don’t fight” for a reason: resisting a difficult emotion during the experience tends to intensify it, while sitting with it usually lets it pass faster.
Integration is not optional. Journal within 24 hours while the material is fresh, then again weekly for two to four weeks. If you’re already in therapy, bring specific memories or images from the session into your next appointment rather than letting them fade. Peer integration circles, even informal ones, help normalize what came up.
Sourcing Safer Psilocybin Products: Lab Testing and Legal Checks
A real certificate of analysis (COA) lists psilocybin and psilocin content by weight percentage, plus a screen for heavy metals, pesticides, and microbial contamination. If a seller can’t produce one, or the COA looks generic and undated, treat that as a hard pass.
Product form changes your risk profile. Whole dried mushrooms let you weigh your own dose but vary in potency stalk to stalk. Edibles and capsules standardize the dose per unit, assuming the manufacturer’s testing is legitimate, but onset can be slower and less predictable than a mushroom eaten on an empty stomach.
Harm-reduction basics worth building into every purchase:
- Use reagent test kits when a COA isn’t available, especially for anything sold as a blend.
- Avoid products marketed as mystery “trip mixes” with undisclosed ingredients.
- Store dried product in an airtight container, away from light and moisture, to preserve potency.
- Check your local jurisdiction’s laws before ordering, growing, or possessing psilocybin. Rules shift by country and by state or province, and enforcement varies even within legal gray zones.
Harm-reduction organizations consistently recommend testing your substance, sticking to one substance per session, and skipping alcohol or cannabis on top of psilocybin, according to guidance from Here to Help.
Growing Your Own: Cultivation Basics and When to Buy Instead
A grow kit is the lowest-effort entry point into cultivation. Spores and live culture demand more sterile technique and patience, and in many places the legal status of spores differs from that of the mushrooms themselves, so check local law before ordering either.
- Sterilize everything that touches your substrate: pressure cook grain or use a still-air box for any open transfers.
- Keep humidity around 90 percent during fruiting and maintain fresh-air exchange, since stale, high-CO2 air produces long, thin stems instead of healthy caps.
- Watch for green or black mold, which almost always means a contamination during setup, not a fixable growing condition.
- Harvest just before the cap fully flattens, then dry thoroughly with a fan or dehydrator before storage.
Beginner failures trace almost entirely to sloppy sterile technique, according to Fungi Academy’s cultivation guide. If you want a consistent, known dose without troubleshooting mold, a vendor-tested product beats a first grow kit every time. Our grow kit FAQ walks through the common failure points in more detail.
Psilocybin and PTSD Medications: What Else Can Interact
Beyond the lithium and MAOI red flags, several PTSD medications interact with psilocybin in subtler ways that are easy to miss. SSRIs and SNRIs, the most commonly prescribed class for PTSD, tend to dampen psilocybin’s subjective effects because both act on serotonin pathways. Someone on a stable SSRI dose may find a typical dose barely registers, which sometimes tempts people to take more, and that’s where things get risky. Escalating dose to compensate for medication blunting removes the predictability that makes dosing charts useful in the first place.

Prazosin, frequently prescribed for PTSD-related nightmares, works on a different receptor system and doesn’t carry the same acute interaction risk, but it can lower blood pressure, and psilocybin’s own cardiovascular effects stack on top of that. Benzodiazepines, sometimes used short-term for PTSD anxiety, can blunt or shorten a psilocybin experience if taken close together, and combining the two to “manage” anxiety during a session works against the process rather than helping it.
Atypical antipsychotics, occasionally prescribed off-label for PTSD nightmares or hypervigilance, share mechanisms with the psychosis-risk contraindications mentioned earlier and deserve the same caution.
None of this is a complete list, and drug interactions vary by individual metabolism and dose. If you’re on any prescribed medication for PTSD, the responsible move is a conversation with the prescribing clinician before introducing psilocybin, not a forum post or a guess. Stopping a psychiatric medication abruptly to “clear it out” before a session carries its own withdrawal risks and should never be done without medical guidance.
Is Psilocybin Right for You? A Personal Readiness Checklist
Suitability comes down to three questions answered honestly, not optimistically. First: does anything on the contraindication list apply to you, directly or in your immediate family? If yes, this isn’t the right avenue, at least not without a clinician’s involvement.
Second: is your current life stable enough to absorb an intense emotional experience? PTSD symptoms can flare unpredictably during and after a session. If you’re in active crisis, mid housing move, freshly grieving, or otherwise stretched thin, wait. A psilocybin session doesn’t pause for convenient timing once it starts.
Third: do you have the actual infrastructure in place? That means a tested product, a private and safe setting, at least 6 to 8 hours with nothing else demanding your attention, and ideally someone available if things get hard. “I’ll figure it out in the moment” is not a plan.
A useful gut check: if you wouldn’t feel comfortable telling a doctor you’re planning to do this, that discomfort is worth examining before you proceed, not after. It usually points to either a contraindication you’re minimizing or a lack of preparation you already sense. None of this requires perfection. It requires that you can answer all three questions with a real yes, not a hopeful one.
Integration Techniques for PTSD Symptom Management After a Session
Generic integration advice (“journal about it”) undersells what actually helps when the material involves trauma specifically. In the first 24 to 48 hours, write down concrete images, memories, or body sensations that surfaced, not just your overall impression of the experience. Trauma-related insights during psilocybin sessions often arrive as fragments, and those fragments fade fast if not captured close to the source.
Over the following two to four weeks, revisit those notes on a set schedule, weekly works for most people, rather than only when symptoms flare. If a specific memory became less charged during the session, test that gently in daily life: does the trigger that used to spike your heart rate still hit as hard? Tracking that shift, or lack of one, gives you real data instead of a vague sense that “something changed.”
Bring the material into existing therapy if you have a therapist, even if they don’t specialize in psychedelics. EMDR practitioners and trauma-focused CBT clinicians can often work with what surfaced without needing to be a psychedelic specialist themselves. Peer integration groups fill the gap when professional support isn’t accessible, and simply saying the experience out loud to someone who won’t flinch has value on its own.
Watch for a rebound effect: some people feel a temporary low in the days after a session, sometimes called an “afterglow” that swings the wrong direction. That’s a normal part of the process for some, but if low mood persists past two weeks or intensifies, that’s a signal to loop in a mental health professional rather than wait it out alone.

Home Cultivation Reality Check: Yield and Potency Variability
Home-grown mushrooms are inherently less predictable than a tested product, and that unpredictability is the single biggest risk factor cultivation adds to self-care use. Two flushes from the same grow kit can differ in potency by a meaningful margin, driven by substrate quality, temperature swings, and even which flush number you’re harvesting (later flushes often run weaker).
This matters enormously for dosing accuracy. A gram of home-grown Psilocybe cubensis from flush one might hit noticeably harder than a gram from flush three off the same kit. If you’re using home-grown product for anything beyond casual exploration, weigh each batch separately, start at the very low end of your usual range with new material, and treat every fresh harvest as an unknown quantity until you’ve calibrated against it.
Drying technique adds another variable. Under-dried mushrooms mold in storage; over-dried or inconsistently dried batches can throw off your dry-weight dosing math entirely. A food dehydrator with a consistent low setting gives more reliable results than air drying, which depends heavily on ambient humidity.
If consistent, predictable dosing matters for your self-care routine, a lab-tested vendor product removes this variability entirely. Cultivation rewards patience and a tolerance for trial and error; it doesn’t reward anyone who needs to know exactly what they’re taking.
What the Research Actually Supports, and What Doesn’t Hold Up
The honest read on psilocybin and PTSD self-care is less exciting than most headlines suggest, and that’s not a bad thing. The strongest evidence in this space isn’t about psilocybin’s effects at all. It’s about harm reduction working: preparation, dose measurement, and having a sober person present measurably reduce challenging experiences. That’s a boring, unsexy finding, and it’s also the most actionable one in this entire guide.
Microdosing gets oversold constantly, often by people selling microdosing products. The controlled research doesn’t back the wellness claims circulating online, and conflating “I felt different” with “this measurably helped my PTSD symptoms” is where a lot of well-meaning advice goes wrong. That doesn’t mean microdosing is worthless for every individual, only that nobody can promise it will work for you specifically.
What the reader should prioritize first isn’t dose size or mushroom strain. It’s the screening step everyone wants to skip. Contraindications aren’t bureaucratic caution, they’re the difference between a difficult session and a genuinely dangerous one. Get that right before anything else on this list.
— Alex
Buying Tested Psilocybin Products Through Fungipsilocybinmushroom
Once you’ve screened for contraindications and mapped out your set and setting, the next real decision is where the product itself comes from. Fungipsilocybinmushroom exists for exactly that step: every product ships with lab-testing documentation instead of a seller’s word, which is the single biggest variable this guide keeps coming back to.
The catalog covers the range this guide walks through: microdose capsules for readers who want a standardized, low-dose option; edibles like the Seremoni chocolate bar line for consistent per-piece dosing; whole dried strains for readers who prefer to weigh their own dose; and grow kits for anyone choosing the cultivation route instead. Discreet worldwide shipping means the product arrives without drawing attention, and the site’s dosing resources, including a detailed dosing guide, stay available after purchase, not just before it.
If dosing precision is where you’re stuck, start there. Check the dosing guide, pick a product with a certificate of analysis attached, and order with your set and setting already planned.
Key Takeaways
Consumer psilocybin can support PTSD-related self-care for some adults, but only when medical screening, lab-tested sourcing, and structured integration all happen in that order.
| Point | Details |
|---|---|
| Screen contraindications first | Rule out psychosis history, bipolar disorder, and lithium or MAOI use before considering any dose. |
| Dose by dry weight only | Use a 0.01 to 0.1 gram scale and start at the threshold range, since potency varies by batch. |
| Treat microdosing claims cautiously | Controlled trials show subjective effects but no consistent cognitive or wellbeing benefit over placebo. |
| Plan integration, not just the session | Journal within 24 hours and revisit weekly for two to four weeks to make insights durable. |
| Choose tested products over guesswork | Fungipsilocybinmushroom provides lab-tested capsules, edibles, dried strains, and grow kits with dosing guidance included. |
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
- Psilocybin for mental health and addiction: what you need to know | NCCIH
- Controlled microdosing study — subjective effects without clear cognitive benefits | PMC9346139
- Psilocybin: A clinician’s guide to pharmacological interactions | Psychiatric Times
- Systematic review of psilocybin microdosing (Frontiers in Psychiatry, 2026)
Recommended
- How to Dose Magic Mushrooms – Fungi Psilocybin Mushroom 2026
- The Ultimate Guide to Finding Quality Psilocybin Mushrooms in California: Top 5 Trusted Sources
- Importance of San Diego Psilocybin Society: Community, Healing & Conscious Growth | 1 oz Psilocybin Mushroom
- Psilocybin Depression Treatment California: Your Complete Guide to Legal Mushroom Delivery Services and Therapeutic Options 2025 | mushroom delivery San Diego | mushroom for sale

Set and Setting: A Harm-Reduction Guide to Safer Trips
Set and setting means your mindset (set) and your physical, social, and cultural environment (setting) together determine whether a psychedelic experience is beneficial or harmful. Get either one wrong and even a moderate dose can turn frightening. Get both right and you dramatically improve your odds of a safe, meaningful session.
Before any session, three things matter more than the substance itself: screen yourself or the person you’re sitting for, secure a calm and private environment, and have a sober, capable person present who knows what to do if things go sideways. A systematic review of clinical trials confirms that participant screening, environmental management, and monitor presence are the components researchers consistently flag as essential, even though they’re not always reported consistently.
- Screen for psychiatric history, medications, and mental state before dosing.
- Prepare a private, comfortable, hazard-free physical space.
- Arrange a sober sitter or guide who is briefed on your intentions and limits.
Pro Tip: Agree on a “trip killer” protocol before you start, not during. Decide in advance what substance or intervention you’ll use if distress becomes unmanageable, who administers it, and at what threshold. Deciding this mid-session, when judgment is already altered, is how simple problems become emergencies.
Key Takeaways
Set and setting together determine psychedelic outcomes more reliably than dose alone, and deliberate preparation of both is the strongest safety intervention available to you.
| Point | Details |
|---|---|
| Definitions matter | “Set” is your internal mindset; “setting” is your physical, social, and cultural environment. |
| Screening comes first | Assess medications, psychiatric history, and current mood before any session, not during. |
| Consensus is forming | The 2025 ReSPCT Delphi identified 30 setting variables experts agree deserve standard reporting. |
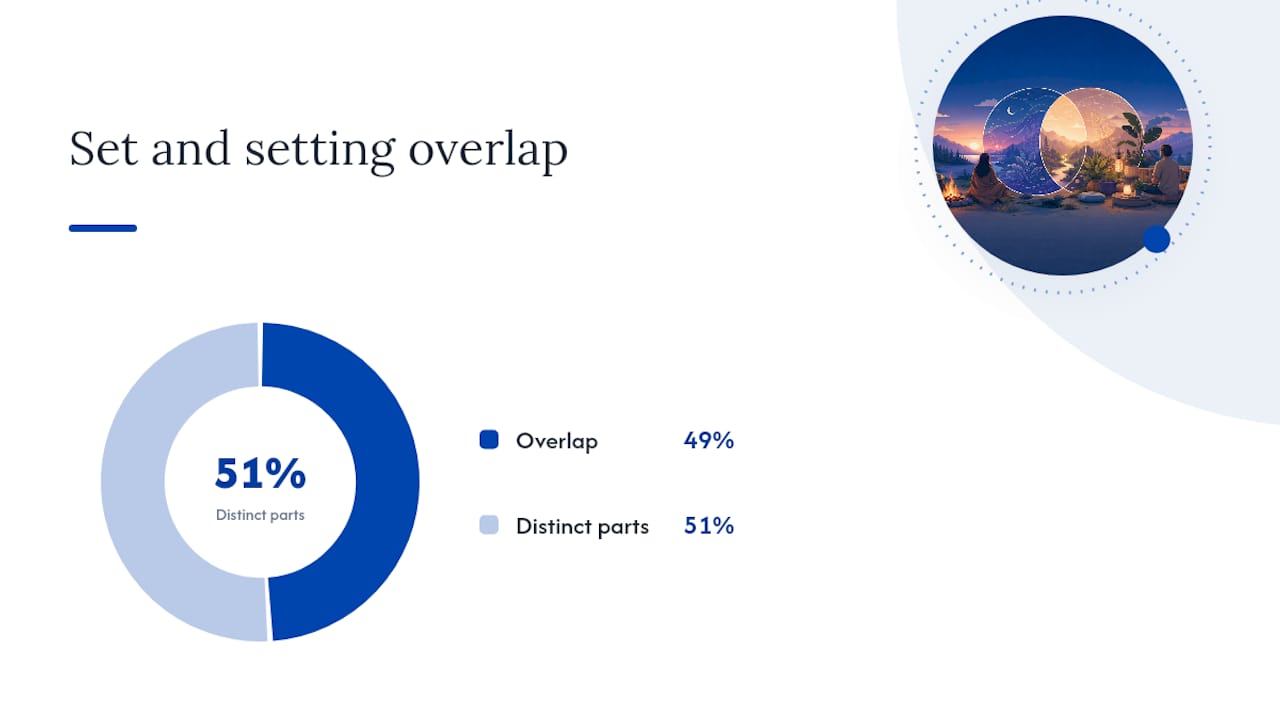
| Overlap is real | Experts estimate roughly 49 percent conceptual overlap between set and setting, so plan both together. |
| Integration extends the benefit | Journaling, professional support, and concrete behavior changes convert insight into lasting change. |
Ready to apply these principles with a product you can trust? Explore lab-tested mushroom strains chosen for therapeutic use and pair careful sourcing with the preparation steps above for the safest possible experience.
What Is Set and Setting, Exactly?
“Set” refers to everything you bring into the experience internally. That includes your mood going in, your expectations about what will happen, your personality traits, your intentions for the session, and any recent life stress or trauma that might surface. Someone grieving a loss, going through a divorce, or nursing untreated anxiety carries a very different “set” than someone who is rested, curious, and emotionally stable. According to the conventional definition popularized through decades of psychedelic research, set is the psychological frame the substance acts on, not a passive backdrop.
“Setting” covers the external world during the experience: the physical room, who else is present, the music playing, the lighting, and the broader cultural context in which the session takes place. A sterile hospital room communicates something different to your nervous system than a softly lit living room with familiar objects around you.
- Set includes mood, expectations, intentions, personality, screening history, and recent stressors.
- Setting includes physical space, social company, sensory design, and cultural framing.
- The boundary between them blurs constantly. A loud, chaotic setting can generate anxious expectations before the substance even takes effect.
These two forces don’t operate in separate lanes. They interact continuously across three phases: preparation, the session itself, and integration afterward.
Experts who study this field don’t even fully agree on where set ends and setting begins. When surveyed for the ReSPCT Delphi consensus, researchers estimated the conceptual overlap between the two terms at roughly 49 percent on average. That’s not a footnote. It means even the people writing clinical guidelines treat this as a blended, not binary, concept.
Where Did the Term “Set and Setting” Come From?
The phrase entered common use in the 1960s, largely through psychologist Timothy Leary and his collaborators at Harvard, who observed that identical doses of the same substance produced wildly different outcomes depending on who took it and where. Al Hubbard, an early and unconventional figure in psychedelic research, independently emphasized environmental design decades before it became standard clinical language, favoring natural settings and careful preparation for his subjects. The concept was later formalized in Norman Zinberg’s 1984 book Drug, Set, and Setting, which remains a foundational reference in addiction and harm-reduction literature.
- Timothy Leary and Harvard-era researchers popularized the terminology in the 1960s.
- Al Hubbard’s early sessions emphasized deliberate environmental design before the term was widely used.
- Norman Zinberg’s Drug, Set, and Setting gave the concept its lasting academic framework.
- Indigenous and shamanic traditions used structured ritual, music, and communal roles long before Western researchers named the phenomenon, a continuity documented in evolutionary analyses of psychedelic ritual.
The idea persisted because it kept proving true in practice. Every generation of researchers who tried to isolate the pharmacological effect of psilocybin or LSD from context found that context refused to stay separate. That stubborn fact is why modern clinical trials now build screening, room design, and therapist presence directly into their protocols instead of treating them as background detail.
What Does the Research Actually Show?
The evidence for set and setting isn’t anecdotal folklore passed down from festival culture. It’s increasingly formalized in clinical research, and the biggest recent development is a 2025 international consensus effort that tried to pin down exactly which environmental variables matter enough to report.
A systematic review of setting components across clinical trials found that researchers consistently track four things: how participants are selected and screened, how the physical environment is managed, whether a trained monitor or guide is present, and what post-session support looks like. The problem is that reporting on these variables remains inconsistent from study to study, which makes it hard to compare outcomes across trials or build firm clinical recommendations. One team’s “comfortable room” might mean a hospital suite with art on the walls; another’s might mean an unremarkable exam room with a couch.
That inconsistency is exactly what prompted the ReSPCT Delphi consensus, published in Nature Medicine in 2025. Researchers convened an international panel of experts and worked toward agreement on which extra-pharmacological variables actually deserve standardized reporting in psychedelic trials. The panel reached consensus on 30 distinct items, ranging from room design to therapist training to music protocols, that they classified as “important” or “very important” to document.
The overlap number worth remembering: when the same Delphi panel was asked how separable “set” and “setting” really are as concepts, their average estimate put the conceptual overlap at approximately 49 percent. Nearly half. That’s a striking admission from the people writing the field’s guidelines: the terms are useful shorthand, but the line between them is genuinely blurry even to specialists.
Separately, a mechanism-first research proposal argues that the field’s biggest weakness isn’t disagreement about definitions. It’s vagueness. Instead of studying “setting” as one giant, undifferentiated variable, researchers are increasingly pushing to isolate specific, testable components, music choice, ambient lighting, degree of therapist directiveness, and measure each one’s effect independently. That shift matters for you as a reader because it means the checklist-style guidance later in this article isn’t guesswork. It reflects where the actual research is heading.
- Clinical trial reporting on set/setting variables remains inconsistent across studies.
- The 2025 ReSPCT Delphi consensus identified 30 reportable setting components.
- Experts estimate roughly 49 percent conceptual overlap between “set” and “setting.”
- A mechanism-first approach is replacing vague, catch-all definitions with testable variables.
How Should You Prepare Your Mindset Before a Session?
Preparing your “set” isn’t about hyping yourself up or forcing a specific emotional state. It’s an honest inventory of where you currently stand, mentally and physically, before you introduce a substance that will amplify whatever is already there.
- Assess your current mood. Are you anxious, depressed, grieving, or unusually stressed this week? Strong negative states don’t disqualify you outright, but they change how much support you need on hand.
- Review medications and psychiatric history. Certain antidepressants, mood stabilizers, and a personal or family history of psychosis or bipolar disorder are serious red flags that warrant professional consultation before proceeding.
- Clarify your intention. Are you seeking insight, processing grief, exploring curiosity, or something else? Vague or absent intentions tend to produce more confusing, harder-to-integrate experiences.
- Check for major life disruptions. A recent breakup, job loss, or unresolved conflict will surface during the session whether you plan for it or not.
- Identify recent substance use. Alcohol, stimulants, and certain prescription drugs can interact unpredictably; if you’re researching how dosing works, review interaction risks as part of that process, not as an afterthought.
If you’re screening someone else as a sitter or guide, ask directly: Have you ever experienced psychosis or mania? Are you currently on psychiatric medication? Has anything happened recently that you’re still processing? Answers that suggest active suicidal ideation, unmanaged psychosis, or a personal history of severe dissociation are reasons to pause and refer to a mental health professional instead of proceeding. Mood disorders and anxiety are common reasons people seek these experiences in the first place, and understanding how mushrooms interact with anxiety is worth doing before, not during, a session.
- Write your intention down the day before, not the morning of.
- Avoid scheduling a session during an already high-stress week.
- Don’t ignore anticipatory anxiety; naming it out loud to your sitter reduces its grip.
Pro Tip: If you notice anticipatory anxiety spiking the night before, don’t suppress it or try to “push through.” Name it to your sitter or write it down as its own intention: “I want to understand why I’m afraid of this.” Fear you acknowledge tends to soften; fear you fight tends to escalate mid-session.
How Do You Design a Safe Physical and Social Setting?
The room you’re in does more psychological work than most people realize. A cluttered, unfamiliar, or exposed space primes the nervous system for vigilance, which is the opposite of what supports a beneficial psychedelic state.
Start with the physical basics: choose a private space where you won’t be interrupted, control the temperature so you’re neither shivering nor overheated, remove sharp objects, breakable items, and anything you could trip over, and make sure a bathroom and water are easily accessible without navigating stairs or unfamiliar hallways. Soft, adjustable lighting beats harsh overhead fixtures. Comfortable seating and the option to lie down both matter more than people expect.

Social setting requires equal attention. Decide in advance who will be present and why. A qualified sitter isn’t necessarily someone with clinical credentials, but they should be sober, emotionally steady, familiar with what psychedelics can do, and someone you trust enough to be vulnerable in front of. Supportive presence during a session measurably shapes its course, and a poorly chosen sitter, someone anxious, judgmental, or unfamiliar with the substance, can inject exactly the kind of social tension that turns a manageable experience into a distressing one. Establish consent and boundaries beforehand: can the sitter touch you if you’re distressed? Are they allowed to play music without asking? Small unspoken assumptions become large problems when someone is in an altered state.
Music deserves its own planning. Curated playlists are a standard part of favorable session design, and the research increasingly treats music as a specific, testable lever rather than incidental atmosphere. Some sessions benefit from sensory minimization, such as an eye mask and instrumental music that blocks external distraction. Others benefit from sensory augmentation, natural light, art, or nature sounds that ground the experience in the present. Neither approach is universally correct; it depends on your intention and your history with anxiety or dissociation. If you’re drawing on cultural or ceremonial traditions for inspiration, do so with awareness that those practices carry meaning beyond aesthetics, and borrowing surface elements without context can feel hollow or even disrespectful.
- Remove hazards, secure privacy, and control temperature and lighting before dosing.
- Choose a sitter based on emotional steadiness and familiarity with the substance, not just availability.
- Set explicit consent boundaries around touch, conversation, and music before the session starts.
- Build a playlist in advance rather than choosing music in the moment.
Pro Tip: Do a “dry run” walk through your space sober, the day before. Sit in each spot you might occupy during the session and ask whether it feels safe and comfortable. What seems fine in an ordinary state of mind can feel completely different once perception shifts.
How Does Set and Setting Differ Across Therapeutic, Ritual, and Recreational Use?
The same core principles apply everywhere, but the emphasis shifts dramatically depending on context. A harm-reduction framework covering these modalities maps out how goals and safety priorities change from one setting to the next.
In therapeutic or clinical contexts, screening is rigorous and often involves formal psychiatric evaluation, the environment is deliberately controlled, and licensed or trained facilitators guide the session with structured preparation and integration built into the protocol. Medical oversight and emergency planning aren’t optional here; they’re the infrastructure the entire model depends on.

In ritual or ceremonial contexts, communal roles and shared cultural framework do much of the work that a clinical protocol would otherwise handle. Participants often defer to an experienced facilitator or elder whose role is partly spiritual and partly practical, managing group energy, timing, and individual distress within a tradition-specific structure.
In recreational or social contexts, screening is frequently informal or skipped entirely, and this is where the highest proportion of preventable bad experiences occurs. Recreational settings still benefit enormously from applying the same core discipline, a trusted sitter, a safe space, and basic screening, even without formal infrastructure behind it.
- Therapeutic settings require medical oversight, structured screening, and formal integration support.
- Ritual settings rely on communal roles, tradition, and an experienced facilitator’s judgment.
- Recreational settings carry the highest risk from skipped screening but still benefit from basic harm-reduction discipline.
- Any context involving a participant with psychiatric risk factors needs professional infrastructure regardless of the setting’s informality.
What Should Your Pre-Session Checklist Look Like?
Preparation works best as a timeline, not a single burst of planning the night before.
Days before:
- Confirm your intention in writing and share it with your sitter.
- Review medications with a doctor or pharmacist if you take anything that could interact, particularly SSRIs, lithium, or MAOIs.
- Choose your strain or product thoughtfully. Potency varies significantly, and understanding differences between mushroom strains helps you calibrate dose to your experience level.
- Arrange transportation for after the session; you should not drive for the remainder of the day.
- Notify one person outside the session (a friend or family member) of your general plans and timing, without necessarily disclosing details, as a safety backstop.
Day of:
- Eat a light meal several hours beforehand; a completely empty stomach can worsen nausea.
- Clear your calendar entirely. Nothing should be scheduled for the following 12 to 24 hours.
- Do a final space check: hazards removed, temperature comfortable, water and snacks accessible.
- Confirm your sitter is sober, present, and briefed on your trip-killer protocol.
Immediately before dosing:
- Weigh or measure your dose carefully rather than eyeballing it; dosing guidance matters more than most people assume, especially with potent strains.
- State your intention out loud one more time.
- Confirm your sitter knows your emergency contact and has a phone charged and accessible.
Medication interactions deserve special weight here. Combining psilocybin with lithium carries a documented seizure risk, and MAOIs can dangerously potentiate certain substances. If you’re on any psychiatric medication, pausing the session and consulting a prescriber first isn’t overcaution, it’s the responsible default. Laws governing psychedelic substances vary enormously by country and even by state or region, so understand your local legal status before proceeding; this article isn’t legal guidance, and ignorance of local law doesn’t reduce your actual legal exposure.
Build a recovery day into your plan. Block the day after the session for rest, gentle food, and no major obligations. Trying to jump straight back into work or high-stakes decisions the next morning undermines the entire preparation you just did.
- Never combine sessions with alcohol or unplanned recreational substances.
- Keep a written emergency contact list accessible to your sitter, not just yourself.
- Document dosage and timing in case medical questions arise later.
What Should Happen During the Session Itself?
A sitter’s job is presence, not performance. The most useful thing they can do most of the time is simply stay calm, stay nearby, and resist the urge to talk unless spoken to or unless something requires intervention.
- Maintain calm, quiet presence for the bulk of the session. Over-talking or over-managing tends to pull people out of valuable internal experiences unnecessarily.
- Check in periodically with simple, low-demand questions: “How are you doing?” rather than open-ended prompts that require complex thought.
- Watch for physical safety issues, unsteady movement, choking risk, or attempts to leave the space, and intervene only when necessary.
- Use grounding techniques for acute distress: slow the breathing pace out loud together, adjust lighting or temperature, offer a hand to hold if consented to beforehand, or shift music to something calmer.
- Deploy the trip-killer protocol if distress escalates beyond what grounding resolves, exactly as agreed upon in advance. Effective use depends entirely on prior training, not improvisation in the moment.
Red flags requiring emergency medical attention include chest pain, seizure activity, loss of consciousness, or signs of serotonin syndrome such as high fever combined with muscle rigidity, especially in anyone who may have combined substances against advice. Document the timeline of doses, symptoms, and interventions if a medical response becomes necessary; that information helps responders act faster.
Pro Tip: Resist the instinct to fix a difficult moment immediately. Sitting quietly alongside someone in distress, without rushing to solve it, often resolves more than active intervention. Reserve directive action for genuine safety concerns, not emotional discomfort that’s simply part of processing. For a deeper breakdown of de-escalation specifics, see this guide on avoiding a bad trip.
How Do You Integrate the Experience Afterward?
The hours immediately following a session call for rest, not analysis. Hydrate, eat something gentle, and avoid jumping into major decisions or difficult conversations while your nervous system resettles.
In the days that follow, journaling becomes one of the most useful tools available. Write down what you remember, including images, emotions, and any insights, even if they feel incomplete or strange in the light of ordinary consciousness. Patterns often become clearer a few days out than they did in the moment.
Over the following weeks, consider whether professional integration support makes sense, particularly if the session surfaced trauma, grief, or material that feels too heavy to process alone. A therapist familiar with psychedelic integration can help translate insight into actual behavioral change, which is where a lot of potential benefit otherwise gets lost.
- Hours after: rest, hydrate, eat lightly, avoid major decisions.
- Days after: journal freely, talk with your sitter about what came up, avoid over-analyzing too quickly.
- Weeks after: identify one or two concrete behavior changes suggested by the experience and schedule an integration session with a professional if the content was difficult.
- Ask yourself: What is one thing I want to do differently because of this?
- Revisit your written intention and compare it to what actually happened.
- Build a support routine, whether that’s therapy, a trusted friend, or a community integration group, rather than processing entirely alone.
What Mistakes and Red Flags Should You Watch For?
The most common mistake isn’t dosing error. It’s skipping screening entirely because the session feels casual or the substance feels familiar. Familiarity breeds complacency, and complacency is where preventable harm creeps in.
A persistent myth worth debunking directly: the idea that the substance alone determines the outcome regardless of context. That belief is precisely what the entire body of set and setting research contradicts. Identical doses in different environments with different mindsets produce measurably different experiences, which is the whole reason this framework exists.
Other frequent errors include choosing a sitter based on convenience rather than emotional steadiness, dosing in an unfamiliar or high-traffic location, and ignoring warning signs like active suicidal ideation or a personal history of psychosis because “it’s just mushrooms.” These aren’t minor oversights.
- Red flag: active suicidal ideation or recent self-harm, regardless of how stable someone otherwise seems.
- Red flag: personal or close family history of psychosis, schizophrenia, or bipolar disorder.
- Red flag: an unpredictable environment, public spaces, unreliable sitters, or unclear legal risk in your jurisdiction.
- Red flag: combining substances, especially alcohol, stimulants, or MAOIs, without professional guidance.
If any of these apply, pause and consult a mental health professional before proceeding rather than adjusting the dose or setting to compensate.
What Questions Are Researchers Still Trying to Answer?
The field is moving away from treating “setting” as one vague, catch-all variable and toward isolating specific, measurable components, music, lighting, therapist directiveness, that can each be tested independently for their actual causal effect.
The push toward mechanism-first research exists because vagueness has real costs: when “setting” means everything, it’s nearly impossible to say which specific ingredient actually produced a given outcome, or to replicate it reliably in a new trial.
The ReSPCT Delphi’s 30-item consensus gives researchers a shared checklist for what to report, which should make future trials far easier to compare against each other. Open questions remain substantial: how much does music specifically contribute versus general sensory calm? Do therapeutic outcomes generalize across cultures with very different ritual traditions? And how much of the “49 percent overlap” between set and setting reflects genuine conceptual blur versus simply imprecise measurement tools.
- Which specific setting components causally drive outcomes, independent of others?
- How well do findings from controlled clinical settings generalize to ritual or recreational contexts?
- Can standardized reporting reduce the current inconsistency across trials?
A Practical Note From Someone Who Has Watched This Field Evolve
The research on set and setting keeps confirming something that harm-reduction communities have argued for decades before it became academically fashionable: context isn’t decoration around the substance, it’s a variable you can actually control. That’s the empowering part often lost in more sensational coverage of psychedelics. You can’t change how a compound binds to a receptor, but you can absolutely change who’s in the room, what the lighting looks like, and whether you’ve thought through your intention beforehand.
What frustrates me most about casual psychedelic culture is how often the “setting” half of the equation gets treated as an afterthought, music playlists thrown together an hour before, sitters chosen because they happened to be free that weekend. The research increasingly rewards people who treat preparation as seriously as the dose itself. Fungipsilocybinmushroom’s educational resources on psilocybin exist precisely because informed preparation, not just product quality, determines whether an experience helps or harms.
Frequently Asked Questions
What does “set and setting” actually mean in simple terms?
Set is your mindset going into a psychedelic experience: mood, expectations, and intentions. Setting is the physical and social environment you’re in during the experience. Both shape the outcome as much as the substance itself.
Who coined the term “set and setting”?
Timothy Leary and colleagues popularized the phrase in the 1960s, though early researchers like Al Hubbard emphasized environmental design before the term became standard. Norman Zinberg’s 1984 book Drug, Set, and Setting later formalized the concept academically.
How much does setting really affect a psychedelic experience?
Substantially. Research consistently links environment, screening, and social support to outcome quality, and the 2025 Delphi consensus identified 30 distinct setting variables experts consider important enough to standardize in clinical reporting.
Do I need a professional guide, or can a trusted friend serve as a sitter?
For recreational or personal use, a sober, emotionally steady, and well-informed friend can serve well as a sitter. For anyone with psychiatric history, current medication concerns, or trauma they intend to process, a trained therapist familiar with psychedelic integration is strongly advisable instead.
What’s a “trip killer” and when should it be used?
It’s a pre-agreed intervention or substance used to reduce the intensity of a difficult psychedelic experience.
Is set and setting equally important for microdosing?
Mindset and environment matter less dramatically at sub-perceptual microdosing levels than during a full session, but consistent routine, mood tracking, and avoiding stressful triggers still support better outcomes.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
For readers who want to go deeper than this guide, a few sources stand out as genuinely worth your time.
- An international Delphi consensus for reporting of setting in psychedelic clinical trials | Nature Medicine
- What are set and setting: Reducing vagueness to improve research and clinical practice – PMC
- Set and Setting for Psychedelic Harm Reduction
- Set and setting
Recommended
- How to Avoid a Bad Mushroom Trip: Complete Guide to Safe Psychedelic Experiences 2026
- Psilocybin Mushroom – Powerful Insights on DMT, Shrooms, LSD & More | Buy Psilocybin Mushroom Online 2026
- How to Dose Psilocybin Safely | Psilocybin Dosing Guide for Magic Mushrooms 5-10mg
- The Ultimate Guide to Finding Quality Psilocybin Mushrooms in California: Top 5 Trusted Sources

Psilocybin for Cluster Headaches: What the Trials Actually Show
Psilocybin Cluster Headaches research represents one of the most promising frontiers in pain medicine, though it remains investigational. The strongest controlled evidence for psilocybin cluster headaches treatment comes from a blinded extension trial where a repeat psilocybin pulse regimen cut attack frequency by roughly 50%, from 18.4 to 9.8 attacks per week. That result carried real statistical weight (p=0.013)—a rare achievement in a headache disorder this brutal and difficult to study.
That said, “promising” and “proven” are different words for a reason. Every trial behind psilocybin cluster headaches data is small, exploratory, and short in follow-up.
Bottom line: Psilocybin cluster headaches research shows a real signal for reducing attacks, but it remains investigational, not standard care.
Strongest evidence: the blinded extension study, with a nearly 50% drop in weekly attacks under repeat dosing.
Safety and legal note: Psilocybin cluster headaches trial dosing was medically supervised, and legal status varies by country and region. Self-treating outside research or clinical settings carries risks these studies were specifically designed to control for.
If you’re living with cluster headache and searching for options beyond what your neurologist has offered, this article walks through what the science says, what a dosing “pulse” or “busting” protocol actually looks like, and how to think about psilocybin cluster headaches access without stepping outside safe, informed decision-making boundaries.
Key Takeaways
Psilocybin cluster headaches trials show a real, statistically significant reduction in attack frequency, but treatment remains investigational and requires medical supervision.
| Point | Details |
|---|---|
| Strongest trial result | A repeat psilocybin pulse cut attacks from 18.4 to 9.8 per week (p=0.013) in a blinded extension study. |
| Regimen tested | Three oral doses of 0.143 mg/kg or a fixed ~10 mg, spaced about five days apart, under supervision. |
| Safety profile | No unexpected serious adverse events reported, but long-term data and larger samples don’t exist yet. |
| Where it fits in care | Studied as a preventive option for refractory chronic cluster headache, not as an acute attack treatment. |
| Product access | Fungipsilocybinmushroom offers lab-tested psilocybin products and educational resources for adults in legal contexts, separate from clinical treatment. |
What the Clinical Trials on Psilocybin Cluster Headaches Found
Two trials anchor most of what is currently known about psilocybin for cluster headaches, and a systematic review ties the wider picture together.
The first was an exploratory randomized, double-blind, placebo-controlled pilot testing a weight-based dose of 0.143 mg/kg (roughly equivalent to 10 mg per 70 kg of body weight) against placebo in chronic cluster headache patients. Researchers gave three oral doses as a “pulse,” and measured changes in attack frequency and intensity. In the chronic-patient subgroup, the effect size was large, d=1.25, meaning the difference between psilocybin and placebo was substantial in practical terms. But the sample was tiny, around 14 evaluable patients, and the overall efficacy outcome across the full study population did not reach statistical significance. Small numbers make it hard to separate a real drug effect from noise, even when the effect looks big on paper.
The second study, a blinded extension of that same trial, is where the evidence gets more compelling. Patients who received a repeat psilocybin pulse saw attack frequency drop from an average of 18.4 attacks per week down to 9.8, a reduction of about half, with a p-value of 0.013 and an effect size (d’) of 0.97. Those are strong numbers for any headache trial, let alone one testing a psychedelic. What makes this finding particularly interesting: some patients who did not respond to their first pulse still improved on a repeat dose, suggesting nonresponse the first time around does not necessarily predict failure on a second attempt.
A 2023 systematic review pulled together the available studies on psilocybin and headache disorders, cluster headache included. Its conclusion was measured: several small studies reported decreases in attack frequency or intensity, but the overall body of evidence is limited and inconsistent in design. That’s an honest summary, not a dismissal.
Key limitations across all of this research:
- Sample sizes are small, often fewer than 20 patients per arm.
- Study designs are exploratory, meaning they’re built to generate hypotheses, not confirm them.
- Follow-up periods are short, so nobody yet knows how durable the benefit is beyond a few months.
- Results may not generalize to every cluster headache subtype (episodic vs. chronic) or to patients with complex psychiatric or cardiac histories.
The headline statistic worth remembering: attacks per week fell from 18.4 to 9.8 in the blinded extension, the single most statistically robust number in the current literature on psilocybin for headaches.
The Pulse or Busting Regimen Tested in Research
Patients researching mushrooms for cluster headaches often encounter the term “busting,” a patient-coined phrase for using low, spaced doses of psilocybin (or LSD) to interrupt a cluster cycle. Clinical trials formalized this idea into what researchers call a pulse regimen, and the protocol details matter if you want to understand what’s actually been studied versus what’s discussed anecdotally online.
- Dose: either a weight-based dose of 0.143 mg/kg or a fixed dose around 10 mg, both intended to produce a moderate, not maximal, psychedelic effect.
- Number of doses: three oral doses per pulse, matching the protocol registered on Clinicaltrials.
- Spacing: doses were given approximately five days apart, not daily and not weekly.
- Setting: every dose was administered in a supervised clinical environment with vitals monitoring and psychiatric screening beforehand, not at home.
- Outcome tracking: researchers measured time to first attack, time to last attack, and percent change in both frequency and intensity, exactly the outcomes listed in the trial’s own registered protocol.
The dosing details in these trials were partly informed by patient reports of self-directed busting protocols, which is part of why researchers describe them as “patient-informed.” But there’s a meaningful gap between a supervised, monitored dose in a research setting and the same substance taken alone, without cardiovascular or psychiatric screening.
Pro Tip: If you’re trying to understand the numbers behind these protocols before talking to a specialist, our guide on how to dose magic mushrooms covers general dosing math, but it is not a substitute for the screening and monitoring built into a clinical trial. Cluster headache dosing decisions belong in a supervised setting, not a solo experiment.
Is Psilocybin Safe for Cluster Headache Patients?
Tolerability data from the trials is genuinely reassuring, with a caveat: reassuring at small scale is not the same as reassuring at large scale.
Across the pilot RCT and its extension, researchers did not report unexpected serious adverse events. Patients experienced the expected acute effects of a moderate psilocybin dose, altered perception, transient anxiety, nausea in some cases, but nothing outside what’s typically seen in supervised psilocybin research for other conditions.

One of the more counterintuitive findings: clinical benefit did not track with how intense the psychedelic experience felt. Patients who had a milder trip did not necessarily see less benefit than those who had a more intense one. That hints at a possible separation between psilocybin’s acute psychotropic effects and whatever is driving the drop in attack frequency, though researchers stop short of calling this settled science.
What trial-based screening typically checks for:
- Personal or family history of psychosis or bipolar disorder, both considered contraindications for psilocybin exposure.
- Cardiovascular risk factors, given psilocybin’s mild effects on heart rate and blood pressure.
- Current medications, particularly SSRIs, SNRIs, and MAOIs, which can interact with psilocybin’s serotonergic activity.
- Baseline psychiatric evaluation before any dosing session.
Pro Tip: If you’re on a daily preventive migraine or headache medication, don’t assume it’s compatible with psilocybin just because it’s common. Bring your full medication list to any specialist or trial coordinator conversation before considering psilocybin for headaches in any form.
What remains unknown is arguably more important than what’s been confirmed: long-term safety data doesn’t exist yet, and tolerability in larger, more diverse populations hasn’t been tested.
Why Might Psilocybin Help Cluster Headache? The Neuroscience So Far
Cluster headache has long been linked to the hypothalamus, the brain region that regulates circadian rhythms, which explains why attacks often cluster at the same time of day or year. Imaging research offers a plausible reason psilocybin might interrupt that cycle.
- Studies have found that changes in hypothalamic-diencephalic functional connectivity after psilocybin correlate with reductions in attack frequency. The more connectivity shifted, the bigger the drop in attacks.
- Preclinical research on psilocybin points to increased neuroplasticity, the brain’s capacity to form new connections, as a possible reason effects might outlast the drug’s presence in the body.
- None of this proves causation. These are correlations observed in small imaging studies, suggestive of a mechanism rather than confirmation of one.
The honest takeaway is that psilocybin appears to interact with the same hypothalamic circuitry implicated in cluster headache pathophysiology, but nobody has proven exactly how that translates into fewer attacks.
Where Psilocybin Fits Alongside Standard Cluster Headache Care
Psilocybin research is aimed at a preventive or transitional role, not an acute one. That distinction matters when you’re weighing it against what’s already available.
For an active attack, high-flow oxygen and subcutaneous sumatriptan remain the fastest, most established abortive options. Psilocybin pulse regimens are not designed to stop an attack in progress. They’re studied as a way to reduce how often attacks happen in the first place, more comparable in intent to preventive medications like verapamil or CGRP-targeting drugs than to a rescue treatment.
- Consider psilocybin research primarily if standard preventives have failed. Refractory chronic cluster headache, meaning verapamil, CGRP therapies, and other standard preventives haven’t worked, is the population most trials have focused on.
- Get a cardiac evaluation first. Verapamil itself carries cardiac considerations, and any new intervention should be screened against your cardiovascular baseline.
- Complete psychiatric screening before considering enrollment. A personal or family history of psychotic disorders is a common exclusion criterion in psilocybin trials.
- Ask your neurologist directly about ongoing trial opportunities rather than assuming none exist in your region.
- Flag any medication that affects serotonin. SSRIs and MAOIs in particular need a specialist’s review before any psilocybin research trial will consider you.
Pro Tip: If a clinician dismisses the question of psilocybin for headaches outright without discussing the trial data, consider getting a second opinion from a headache specialist at an academic center, where awareness of this research tends to run higher.
Red flags that should stop the conversation entirely: unstable psychiatric illness, active substance use disorder, or medications with known dangerous interactions with serotonergic compounds.
How to Find Legitimate Psilocybin Cluster Headache Trials
ClinicalTrials.gov is the primary public registry for finding active or completed studies, including protocols like NCT02981173, which outlines the exact pulse dosing and outcome measures used in published research.
- Check that a trial lists a named academic or hospital affiliation, not just a private clinic.
- Confirm the protocol references institutional review board (IRB) or ethics committee approval.
- Look for a published or registered protocol you can cross-reference against the trial’s actual claims.
- Contact the listed study coordinator directly rather than a third-party recruiter.
Legal status of psilocybin varies significantly by country, and in some places by state or region. Nothing in this article should be read as encouragement to source or use psilocybin outside a legal, supervised research context. Cluster headache is severe enough that self-experimentation carries real risk, both medical and legal.
What Cluster Headache Patients Should Take From This Research
The gap between what psilocybin promises for cluster headache and what’s actually confirmed is wide, and that gap is exactly where informed patients get the most value out of paying close attention.
Here’s the part that gets underplayed: the most statistically solid finding in this entire body of research came from a repeat dose, not a first attempt. That’s a detail patient communities have known intuitively for years through informal busting reports, but it took a blinded extension trial to actually put a number on it. If you tried a single psilocybin pulse once, years ago, and felt nothing, that outcome doesn’t necessarily predict how you’d respond to a properly repeated, monitored regimen.
The other underappreciated point is the dissociation between trip intensity and clinical benefit. A lot of psychedelic-curious patients assume a bigger, more intense experience means a stronger therapeutic effect. The cluster headache data doesn’t support that assumption, and it’s a useful corrective for anyone tempted to self-escalate a dose hoping for more relief.
None of this changes the fact that psilocybin for cluster headaches is still investigational. But “investigational” doesn’t mean ignore it. It means the smartest move for a patient with refractory disease is pushing your neurologist for a real conversation about trial referral, not quietly experimenting alone based on a forum post.

A Note on Product Quality From Fungipsilocybinmushroom
Fungipsilocybinmushroom focuses on lab-tested psilocybin products and educational resources for adults exploring psychedelics, including detailed guides on dosing, strain selection, and safe use practices. None of that changes the core message of this article: cluster headache is a severe neurological condition, and psilocybin’s role in treating it is still being defined through supervised clinical research, not personal experimentation. If you’re weighing psilocybin as part of a broader conversation about therapeutic use, our guide on strains selected for therapeutic contexts offers useful background, but a cluster headache diagnosis calls for a specialist and, ideally, a registered trial first.
Buying Lab-Tested Psilocybin Responsibly
If you’re an adult in a legal jurisdiction exploring psilocybin for wellness or research literacy rather than as a cluster headache treatment, product quality is where most of the real risk hides. Unregulated markets are full of mislabeled potency and unknown contamination, which is a very different problem than what any clinical trial is testing for.
Fungipsilocybinmushroom lab-tests every batch before it ships, giving you a verified potency and purity profile instead of a guess. That distinction is the whole reason lab testing exists: a trial-grade dose only means something if you actually know what’s in it. Browse the Amazonian psilocybin mushroom collection to see verified lab results and strain details, and use that information to have a more informed conversation with your clinician, not as a replacement for one. If cluster headache is what brought you here, the right next step is still a referral to supervised research. But if you’re learning about psilocybin more broadly, that page is where to start.
Frequently Asked Questions
Does psilocybin actually reduce cluster headache attacks?
Controlled trial data shows a significant reduction in attack frequency with a repeat psilocybin pulse regimen, roughly a 50% drop in one blinded extension study. The evidence is promising but comes from small samples and needs replication in larger trials.
What dose of psilocybin was used in cluster headache research?
Trials used either a weight-based dose of 0.143 mg/kg or a fixed dose around 10 mg, given as three oral doses roughly five days apart under clinical supervision.
Is psilocybin legal to use for cluster headaches?
Legal status varies by country and, in some places, by state or region. Access to psilocybin for cluster headache currently exists mainly through registered clinical trials, not general medical prescription.
How does psilocybin compare to standard cluster headache treatments?
Standard acute treatments like high-flow oxygen and sumatriptan stop an attack in progress. Psilocybin pulse regimens are studied as a preventive approach, more comparable to preventives like verapamil, aimed at reducing how often attacks occur.
Who should not consider psilocybin for cluster headache research?
Trial screening typically excludes people with a personal or family history of psychosis or bipolar disorder, unmanaged cardiovascular risk, or current use of serotonergic medications like SSRIs or MAOIs without specialist clearance.
Sources
- Psilocybin pulse regimen reduces cluster headache attack frequency in the blinded extension phase of a randomized controlled trial
- Exploratory investigation of a patient-informed low-dose psilocybin pulse regimen in the suppression of cluster headache: Results from a randomized, double-blind, placebo-controlled trial
- A systematic review to assess the use of psilocybin in the treatment of headaches
- Clinicaltrials
Recommended
- How to Dose Magic Mushrooms – Fungi Psilocybin Mushroom 2026
- Mushrooms for Anxiety – Natural, Calming, and Powerful Support for a Healthier Mind 2025 | mushrooms for anxiety relief for sale
- Psilocybin Depression Treatment California: Your Complete Guide to Legal Mushroom Delivery Services and Therapeutic Options 2025 | mushroom delivery San Diego | mushroom for sale
- Microdosing Psychedelics: Unveiling Remarkable Health Benefits and Therapeutic Potential 2026

Psilocybin Anxiety Relief: What the Evidence Actually Shows
Psilocybin Anxiety Relief has produced rapid, sustained results in clinical settings, according to the landmark 2016 Griffiths et al. randomized trial. A single supervised dose, combined with psychotherapy, delivered dramatic drops in anxiety among people facing serious illness. A later systematic review of mechanistic and clinical literature backs the same conclusion, and Johns Hopkins has built an entire research program around replicating and extending those psilocybin anxiety relief outcomes.
That is the real headline: this is not folk medicine dressed up in new language. It is a compound with actual trial data behind psilocybin anxiety relief, tested mostly in people facing cancer-related distress or treatment-resistant depression.
The caution matters just as much as the promise. Most of the strong evidence for psilocybin anxiety relief comes from small, tightly screened trials—not from someone buying mushrooms online and dosing alone in a bedroom. The research applies specifically to:
- Anxiety tied to a life-threatening diagnosis, particularly cancer
- Treatment-resistant depression with a significant anxiety component
- Patients who underwent psychiatric screening and received supervised, in-person sessions with trained clinicians
Roughly 60 to 80% of participants in the Griffiths trial maintained clinically significant psilocybin anxiety relief at 6.5 months. That is a striking number for psychiatry, where relapse is the norm rather than the exception. It is also a number earned inside a controlled clinical setting, with medical oversight and careful preparation—not a casual trip.
Key Takeaways
Psilocybin anxiety relief shows a consistent, replicated anxiolytic signal in supervised clinical trials for illness-related anxiety, but it is not a proven treatment for generalized anxiety disorder used outside medical supervision.
| Point | Details |
|---|---|
| Trial evidence is real but narrow | The Griffiths 2016 trial showed 60 to 80% of cancer patients maintained anxiety relief at 6.5 months, but the population was illness-specific. |
| Mechanism centers on the DMN | Psilocybin binds 5-HT2A receptors and appears to downregulate default mode network activity, which is linked to reduced rumination. |
| Acute anxiety is a real risk | The 2024 iScience study found psilocybin can trigger acute anxiety and amygdalar changes during the session itself. |
| Screening is non-negotiable | Personal or family history of psychosis, unstable bipolar disorder, and MAOI use are established contraindications requiring clinician review. |
| Fungipsilocybinmushroom supports informed use | The site offers lab-tested products and educational resources so readers researching psilocybin for anxiety can make better-informed decisions. |
Key Primary Sources and Further Reading
- NCCIH psilocybin overview: federal guidance on risks and research status
- Johns Hopkins Center for Psychedelic and Consciousness Research: ongoing clinical trial summaries
- PMC mechanistic review: neuroplasticity, serotonin, and microdosing evidence gaps
- University of Wisconsin School of Pharmacy explainer: academic framing of anxiolytic mechanisms
Does Psilocybin Help Anxiety? The Clinical Trial Evidence
The strongest data on psilocybin for anxiety comes from a small number of trials, most of them built around people facing serious illness rather than generalized anxiety disorder as most readers experience it. That distinction shapes everything else in this section.
The 2016 Griffiths trial at Johns Hopkins remains the reference point. Researchers gave a single moderate dose of psilocybin to patients with cancer-related psychological distress, paired with psychotherapy before and after the session. Anxiety and depression scores dropped fast, often within a day or two, and the effect held up at follow-up months later. A parallel trial at NYU used a similar design and found comparable results in a separate patient group, reinforcing that the Hopkins findings were not a fluke tied to one research team.
Systematic reviews since then have tried to pool this data and ask a harder question: how big is the effect, really, and how confident should we be in it? A comprehensive review of psilocybin’s neurobiological and clinical evidence found consistent signals for anxiolytic and antidepressant effects across the macrodose trials, while flagging that microdosing research remains thin, mostly self-reported, and not powered the same way. That gap between macrodose and microdose evidence quality comes up again and again in the literature, and it is worth holding onto as you read claims elsewhere.
Here is how the key trials compare on design and outcome:
| Trial | Year | Population | Design | Primary outcome | Follow-up |
|---|---|---|---|---|---|
| Griffiths et al. (Johns Hopkins) | 2016 | Cancer patients with anxiety/depression | Randomized, double-blind, crossover | Rapid, sustained drop in anxiety and depression scores | 6.5 months |
| NYU cancer-distress trial | 2016 | Cancer patients with existential distress | Randomized, double-blind, crossover | Reduced anxiety and depression, improved quality of life | 6.5 months |
| Open-label depression studies | Various | Treatment-resistant depression | Open-label, no placebo control | Reduced depressive symptoms, secondary anxiety improvement | Weeks to months |
| Systematic review synthesis | Ongoing | Pooled trial populations | Meta-analytic and narrative review | Consistent anxiolytic signal in macrodose studies | Varies by trial |

A few things jump out when you sit with that table. First, almost every rigorous trial uses a crossover or waitlist design rather than a true parallel-group placebo comparison, because blinding is nearly impossible when one group visibly experiences a psychedelic state and the other does not. Second, follow-up periods rarely extend past six or seven months, so claims about multi-year durability are not yet backed by the data. Third, populations skew heavily toward people already facing a life-threatening or treatment-resistant condition, which means results do not automatically generalize to someone with generalized anxiety disorder and no comorbid illness.
The limitations are not minor footnotes. They shape what a responsible reader should take from this evidence:
- Sample sizes in the landmark trials run from a few dozen to around a hundred participants, small by pharmaceutical standards.
- Nearly all rigorous data comes from people with cancer-related distress or treatment-resistant depression, not generalized anxiety in otherwise healthy adults.
- Blinding is compromised because participants and researchers can usually tell who received the active dose.
- Long-term data beyond six to twelve months is sparse, so claims about permanent remission outrun what trials have actually measured.
None of this erases the signal. It just means the honest claim is “promising and repeatedly replicated in narrow populations,” not “proven cure for anxiety.” You can read more about how these findings apply specifically to anxiety relief from psilocybin and how researchers frame the evidence for psychedelic mushrooms and anxiety more broadly.
How Does Psilocybin Reduce Anxiety in the Brain?
Psilocybin works by binding to the 5-HT2A serotonin receptor, which triggers a cascade of downstream effects tied to mood and cognition. Once metabolized into psilocin, it acts as a serotonin agonist that appears to increase neuroplasticity and quiet the default mode network, a network of brain regions associated with self-referential thought and rumination, according to a detailed mechanistic review.
Picture it this way: the default mode network (DMN) is the brain’s inner narrator, the voice that loops over worries, replays past mistakes, and rehearses future catastrophes. Anxiety disorders are, in part, a hyperactive version of that loop. Imaging research suggests psilocybin temporarily quiets DMN activity, and when that quieting happens inside a supportive, well-prepared session, patients often report a shift away from rigid, anxious thought patterns toward something more flexible. Reduced DMN chatter appears to translate into less rumination, which in turn seems to open space for the kind of emotional flexibility that anxious minds struggle to access.
The mechanisms researchers point to fall into a few overlapping categories:
- Serotonergic agonism at 5-HT2A receptors, which appears to be the primary trigger for psilocybin’s acute subjective and neurological effects.
- Increased neuroplasticity, giving the brain more capacity to form new associative patterns rather than defaulting to entrenched anxious ones.
- Default mode network downregulation, linked to reduced rumination and a looser grip on habitual, anxious self-narratives.
- Changes in amygdala reactivity, the brain’s threat-detection center, though a 2024 iScience study found some of these amygdalar molecular changes happen independently of 5-HT2A activation, meaning the full mechanistic picture is more tangled than a single-receptor story.
- Possible anti-inflammatory effects, an emerging area of interest that remains less established than the serotonergic and neuroplasticity pathways.
There is also a psychological layer that pure neuroscience cannot fully explain. Patients who experience what researchers call a “mystical” or peak experience, a sense of unity, ego dissolution, and transcendence during the session, tend to report stronger and longer-lasting anxiety relief. Patients who have a difficult or fragmented session, without that peak quality, often see weaker or shorter-lived benefit. This correlation between subjective experience and outcome is one reason clinicians treat the session itself, not just the molecule, as the active ingredient.
Microdosing sits outside almost all of this evidence because sub-perceptual doses do not typically produce the ego-dissolution experience linked to durable outcomes, and because microdosing research relies heavily on self-report rather than controlled trials, the mechanistic story above mostly does not apply to it. If you are curious how the two approaches diverge in evidence and intent, the microdosing psychedelics comparison breaks down where the data is thin.
What Are the Short-Term Risks of Taking Psilocybin?
Psilocybin sessions commonly produce nausea, headache, elevated heart rate and blood pressure, and in some cases a wave of transient anxiety or paranoia rather than the calm, insightful state people expect. The NCCIH lists these as recognized short-term effects, alongside a rare risk of persistent psychosis in vulnerable individuals.
The paradox here deserves attention: a substance studied for its anxiety-reducing potential can also cause acute anxiety during the experience itself. A 2024 study published in iScience documented exactly this, finding that psilocybin triggered acute anxiety in a subset of participants and identified molecular changes in the amygdala that help explain why. Some of these changes occurred independently of the 5-HT2A receptor pathway usually credited with psilocybin’s therapeutic effects, suggesting the anxiety-relief and anxiety-inducing pathways may not be as separable as clinicians would like.
Common short-term effects reported across trials and reviews include:
- Nausea and occasional vomiting, especially in the first 30 to 60 minutes
- Headache, both during and in the hours after the session
- Elevated heart rate and blood pressure, generally mild and self-limiting
- Transient anxiety, fear, or paranoia during the peak of the experience
- Perceptual distortions that can feel disorienting without proper preparation
Severity in supervised trials tends to be manageable. Clinicians trained in psychedelic-assisted therapy use grounding techniques, verbal reassurance, and a calm, low-stimulation environment to help a participant move through a frightening wave rather than escalate it. This is precisely why unsupervised use carries more risk: there is no trained person present to recognize a challenging reaction early and intervene before it spirals into panic or unsafe behavior.
Pro Tip: A “bad trip” during a clinical session is often managed successfully within the room through breathing, reassurance, and a change in music or lighting. Outside a supervised setting, that same reaction has no safety net.
Who Should Avoid Psilocybin for Anxiety?
Psilocybin is contraindicated for people with a personal or family history of psychosis or schizophrenia, and for those with unstable bipolar disorder, because the drug’s disruption of ordinary cognitive filtering can trigger or worsen psychotic symptoms. The NCCIH explicitly flags this population as higher risk.
Cardiovascular conditions matter too. Because psilocybin can raise heart rate and blood pressure, people with uncontrolled hypertension or certain heart conditions need clinician evaluation before considering a session, supervised or otherwise.
Medication interactions add another layer of complexity. Combining psilocybin with MAOIs can produce dangerous, unpredictable reactions, and mixing it with certain SSRIs or SNRIs may blunt the psychedelic effect or interact in ways that are not yet fully mapped out in the research. This is not a case where a quick internet search substitutes for a conversation with a prescribing clinician who knows the full medication history.
A responsible screening process, the kind used in clinical trials, typically covers:
- Full psychiatric history, including any personal or family history of psychosis, schizophrenia, or bipolar disorder
- Complete medication review, with particular attention to MAOIs, SSRIs, and SNRIs
- Cardiovascular assessment, including blood pressure and any history of heart disease
- Informed consent covering the nature of the experience, potential for acute anxiety, and the limits of what the research actually shows
- Assessment of current life stressors and readiness, since an unstable personal situation can amplify a difficult session
This is the part of the conversation that gets skipped in casual online discussion, and it is the part that separates a clinical protocol from a gamble.
How Is Psilocybin Delivered in a Therapeutic Setting?
Clinical psilocybin therapy follows a three-phase structure: preparation, the supervised dosing session, and integration afterward. Skipping any one of these phases is where most of the risk in “solo” psilocybin use for anxiety actually comes from.
- Preparation. Patients meet with a therapist beforehand to build rapport, discuss intentions, and get a clear picture of what the experience might involve. This phase is also where screening happens, ruling out contraindications and setting expectations honestly.
- The supervised session. Doses in trials for anxiety and depression have typically fallen in the range associated with a strong but manageable psychedelic effect, administered in a calm, controlled room with one or two trained sitters present throughout, often four to six hours.
- Integration. Follow-up sessions help patients process what happened, connect insights from the experience to daily life, and work through anything unresolved, including a difficult or frightening moment during the session itself.
Dosing in the landmark trials was deliberately conservative relative to recreational use, aimed at producing a meaningful psychedelic experience without pushing into territory more likely to cause overwhelming distress. Higher doses generally correlate with a stronger mystical-type experience and, per the correlational data mentioned earlier, potentially stronger anxiolytic outcomes, but they also raise the odds of a challenging psychological reaction. This is the tradeoff clinicians manage directly rather than leaving to chance. Readers curious about how these ranges compare to typical recreational use can review dosing guidance for magic mushrooms.
Microdosing takes a fundamentally different approach: small, sub-perceptual amounts taken on a schedule, often aiming for subtle mood or focus benefits rather than a full psychedelic experience. The evidence gap matters here. Full supervised doses have real randomized trial support behind their anxiety outcomes; microdosing has enthusiastic self-report but no equivalent controlled trial base. People drawn to microdosing chocolate formats, for example, are often chasing a gentler, everyday-life-compatible experience rather than the intensive clinical protocol described above, a distinction worth understanding before assuming the research applies equally to both.
What actually makes a session safe has less to do with the mushroom and more to do with who is in the room. Therapist training, a clear emergency protocol for medical or psychiatric complications, and a physically comfortable, low-stimulation environment are the three pillars every credible clinical program builds around, echoing what Johns Hopkins researchers describe as central to their protocol design.

Is Psilocybin Legal for Treating Anxiety?
Legal status varies enormously by country and even by region within a country, and nothing here should be read as legal advice for your specific location. Some places have decriminalized personal possession, a small number have regulated therapeutic or supervised-use programs, and in most of the world psilocybin remains a controlled substance with no legal therapeutic pathway at all.
Access generally falls into a few categories:
- Clinical trials, run through universities or research institutions, which offer supervised access but require meeting strict enrollment criteria
- Licensed therapy or supervised-use programs, available in a limited number of jurisdictions and typically requiring medical screening
- Private clinics, operating legally only where local law explicitly permits them
- Informal or unregulated access, which carries no medical oversight, no screening, and no emergency protocol if something goes wrong
Where legal supervised programs do exist, cost and availability are real barriers. A resource-intensive model involving trained therapists, extended session times, and follow-up integration care is expensive to run, which keeps many programs limited in capacity and out of reach for people without significant financial resources or trial access. Readers exploring regional programs, such as those covered in the California psilocybin treatment guide, should confirm current local law directly, since regulations shift.
How Can You Reduce Risk If You’re Exploring Psilocybin?
If you are researching psilocybin for anxiety outside a formal clinical trial, the gap between a safe experience and a dangerous one usually comes down to preparation, not the substance itself.
Start by evaluating any provider or facilitator with the same scrutiny you would apply to any other health decision:
- Confirm licensing or formal training in psychedelic-assisted therapy, not just general wellness credentials.
- Ask directly about medical oversight, including whether a physician reviews health history and current medications beforehand.
- Ask what the emergency protocol is if someone has a severe psychological or physical reaction.
- Confirm that informed consent covers realistic risks, including the chance of acute anxiety or a difficult psychological experience.
Beyond provider vetting, a handful of practical steps reduce risk regardless of setting:
- Review your current medications with a clinician, especially MAOIs, SSRIs, and SNRIs, before any session.
- Arrange for a sober, trusted person to be physically present the entire time.
- Control the environment: a quiet, comfortable, familiar space lowers the odds of a frightening reaction.
- Eat lightly beforehand and stay hydrated, since nausea is common in the first hour.
If a session takes a difficult turn, the immediate priorities are the same ones used in clinical settings: recognize the warning signs (severe confusion, chest pain, extreme agitation, or loss of physical control), keep the environment calm and low-stimulation, offer verbal reassurance rather than argument, and call emergency services without hesitation if physical symptoms suggest a medical emergency rather than a psychological one.
What Don’t We Know Yet About Psilocybin and Anxiety?
The honest answer is that researchers are still working out how far these findings generalize. Key open questions include:
- How psilocybin performs in generalized anxiety disorder specifically, separate from illness-related or existential anxiety
- Head-to-head comparisons against standard treatments like SSRIs or cognitive behavioral therapy, which barely exist yet
- Long-term relapse rates beyond the six to twelve month window most trials cover
- Optimal dosing schedules, including whether repeated sessions outperform a single high dose
- Whether microdosing has any measurable clinical effect beyond placebo, given the current lack of large double-blind trials
- Safety and efficacy in people with common comorbidities, such as substance use history or complex medication regimens
Future trials need larger sample sizes, better blinding strategies despite the inherent challenge of blinding a psychedelic experience, and follow-up windows stretching well past a year. Watch for Phase 3 trial results and any regulatory shifts tied to the FDA’s breakthrough therapy designations for psilocybin-assisted psychotherapy, which signal where the clinical pathway is likely headed next.
What the Landmark Cancer-Anxiety Trial Really Proved
The 2016 Griffiths trial remains the single most cited piece of evidence in this entire field, and it deserves a closer look on its own terms.
- A single moderate dose of psilocybin, combined with psychotherapy, produced rapid reductions in anxiety and depression among patients facing cancer-related distress.
- Between 60% and 80% of participants maintained clinically significant improvement at the 6.5-month follow-up mark, an unusually durable result for a single-session psychiatric intervention.
- The effect sizes reported were large by psychiatric research standards, though the sample size was modest, consistent with an early-phase trial rather than a large-scale confirmatory study.
What this trial does prove: a single supervised psilocybin session, embedded in psychotherapy, can produce a lasting reduction in anxiety tied to a life-threatening diagnosis. What it does not prove: that the same protocol works the same way for generalized anxiety disorder in someone without a serious illness, or that the benefit holds indefinitely beyond the studied window. Existential anxiety tied to mortality and illness is psychologically distinct from chronic, free-floating anxiety, and conflating the two is one of the more common misreadings of this research floating around online. The original trial data, available through Griffiths et al., 2016, remains the primary source anyone citing this study should actually read rather than paraphrase secondhand.
A Publisher’s Note on This Research
Fungipsilocybinmushroom approaches this topic from an evidence-first, harm-reduction stance: we would rather readers understand the real limits of the data than oversell what psilocybin can do. As a retailer of lab-tested Amazonian mushrooms and other psychedelics, we have a direct stake in this conversation, which is exactly why we point readers toward licensed clinicians and legitimate research before anything else. Nothing here replaces a conversation with a qualified medical or mental health provider.
Get Lab-Tested Psilocybin Products From Fungipsilocybinmushroom
Reading the clinical evidence is one thing. Finding a product you can actually trust is another problem entirely, and it is where most people researching psilocybin for anxiety hit a wall: sketchy sourcing, no lab verification, and zero transparency about potency. Fungipsilocybinmushroom solves that specific problem. Every product ships with lab testing behind it, discreet worldwide delivery, and a catalog built for both first-timers and people with years of experience, from milder Golden Teacher varieties to more intense options for experienced users.
If dosing precision matters to you, which it should given everything the research says about dose and outcome, the Seremoni psilocybin chocolate bar offers consistent, measurable dosing in an edible format, useful for anyone trying to replicate a controlled, deliberate approach rather than guessing at a dried mushroom’s potency. Pair that with our educational guides on strains suited to therapeutic use to match a product to your goals. Browse the current catalog and place an order through our secure checkout to get started.
Frequently Asked Questions
Does psilocybin actually help anxiety, or is that overstated online?
Clinical trials show real, measurable anxiety reduction, particularly in people facing cancer-related distress, but the strongest data comes from supervised sessions with psychotherapy, not casual use.
How long does psilocybin’s anxiety relief typically last?
In the Griffiths trial, most participants who improved held that improvement at 6.5 months. Data beyond that window remains limited.
Can psilocybin make anxiety worse instead of better?
Yes. Acute anxiety and paranoia during the session are recognized short-term risks, documented in both NCCIH guidance and a 2024 iScience study.
Is microdosing effective for anxiety?
The evidence is much weaker than for supervised full doses. Microdosing research relies mostly on self-report rather than controlled trials, according to a comprehensive mechanistic review.
Who should never take psilocybin for anxiety?
People with a personal or family history of psychosis or schizophrenia, unstable bipolar disorder, certain cardiovascular conditions, or those taking MAOIs should avoid it without direct clinician guidance.
How does psilocybin compare to SSRIs or CBT for anxiety?
Direct head-to-head trials against SSRIs or cognitive behavioral therapy are still lacking. Current evidence suggests psilocybin can work faster in specific populations, but standard treatments have far more long-term safety data.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
- Mushrooms, microdosing, and mental illness: The effect of psilocybin on neurotransmitters, neuroinflammation, and neuroplasticity (PMC review)
- Psilocybin for mental health and addiction: What you need to know (NCCIH)
- Johns Hopkins Center for Psychedelic and Consciousness Research — summary page
Recommended

How to Grow Magic Mushrooms at Home
How to Grow Magic Mushrooms at Home: The Secret Method Experts Don’t Want You to Know

How to Grow Magic Mushrooms at Home: The Secret Method Experts Don’t Want You to Know
So you want to grow magic mushrooms at home—but every guide you’ve found either glosses over the important details or assumes you already have a lab setup. You don’t need either.
This guide is for complete beginners who want real, actionable steps without the guesswork. No prior experience required, no fancy equipment to start, and no wasted money on methods that don’t actually work.
Here’s what you’ll walk away knowing:
-
Which mushroom variety to pick first—because the wrong choice kills your motivation before you even start
-
Exactly what supplies you need and what you can skip until you’re ready to scale up
-
How to control your growing environment—the one factor most beginners get wrong that leads to mold, failed flushes, and frustration
By the end, you’ll have a clear path to your first successful harvest.
Choose the Right Mushroom Variety for Beginners

Best Starter Varieties: Oyster and Shiitake Mushrooms
When you’re just beginning your journey to grow magic mushrooms at home, choosing the right variety can make the difference between a thriving harvest and a frustrating failure. Two varieties consistently stand out as the best entry points for beginners: Oyster mushrooms and Shiitake mushrooms.
Oyster Mushrooms (Pleurotus ostreatus) are widely regarded as the single easiest mushroom for home cultivators to grow. They colonize quickly, tolerate a relatively wide range of environmental conditions, and produce generous flushes in a short amount of time. Their forgiving nature means that even small mistakes in humidity or temperature are less likely to ruin your entire crop.
Shiitake Mushrooms (Lentinula edodes) are the ideal second step. They take slightly longer to colonize and fruit than oyster mushrooms, but they reward patience with rich, meaty yields and exceptional flavor. Shiitake also teaches you valuable lessons about managing moisture levels and fruiting triggers — skills you’ll carry forward into more advanced cultivation.
Key reasons beginners gravitate toward these two varieties:
-
Fast colonization times reduce the window for contamination
-
Widely available spawn and substrate materials keep startup costs low
-
Well-documented growing guides make troubleshooting straightforward
-
High success rates build confidence for tackling harder species
Advanced Varieties to Explore Later: Lion’s Mane, Morels, and Wine Caps
Once you’ve successfully completed a few grow cycles with oyster or shiitake, you’ll be ready to level up. With this in mind, next, we’ll look at three advanced varieties that experienced cultivators love to pursue.
Lion’s Mane (Hericium erinaceus) produces striking, cascading white formations and is prized both for its culinary value and its widely studied cognitive health properties. However, it demands precise humidity levels and is highly sensitive to CO₂ buildup, making good air exchange absolutely critical.
Morels (Morchella spp.) are perhaps the most challenging mushrooms on this list. They require a complex relationship with soil organisms and specific environmental cues — including a simulated cold period — to fruit reliably. Even experienced mycologists find them unpredictable.
Wine Caps (Stropharia rugosoannulata) sit in an interesting middle ground. They’re grown outdoors in wood chip beds, making them a great option for gardeners looking to expand beyond indoor cultivation. They’re hardy and productive but require outdoor space and seasonal timing.
| Variety | Difficulty | Growing Environment | Colonization Time |
|---|---|---|---|
| Lion’s Mane | Intermediate | Indoor, high humidity | 2–4 weeks |
| Morels | Advanced | Outdoor/soil-based | Months to years |
| Wine Caps | Intermediate | Outdoor, wood chips | 4–8 weeks |
Understanding Each Variety’s Unique Growing Requirements
Previously, we covered which varieties suit beginners and which reward more experienced growers. Now that we have covered the landscape of options, it’s essential to understand that no two mushroom varieties share identical growing requirements. Treating them as interchangeable is one of the most common mistakes home cultivators make.
Here’s a breakdown of the core growing parameters that differ significantly between varieties:
Substrate Preferences
-
Oyster mushrooms thrive on straw, coffee grounds, and hardwood sawdust
-
Shiitake performs best on supplemented hardwood logs or sawdust blocks
-
Lion’s Mane favors hardwood sawdust with wheat bran supplementation
-
Wine Caps prefer layered wood chips mixed into garden beds
Temperature Ranges
| Variety | Colonization Temp | Fruiting Temp |
|---|---|---|
| Oyster | 70–75°F (21–24°C) | 55–65°F (13–18°C) |
| Shiitake | 70–80°F (21–27°C) | 50–65°F (10–18°C) |
| Lion’s Mane | 65–75°F (18–24°C) | 60–70°F (15–21°C) |
| Wine Caps | 60–75°F (15–24°C) | 50–65°F (10–18°C) |
Humidity and Air Exchange
-
Most varieties require 85–95% relative humidity during fruiting
-
Lion’s Mane is uniquely sensitive — even slight CO₂ buildup causes elongated, deformed fruiting bodies
-
Shiitake benefits from a cold water soak or temperature drop to trigger pinning
Understanding these distinctions early saves you countless hours of troubleshooting. Matching the right variety to your available equipment, space, and climate is the foundation of a genuinely successful home mushroom growing operation.
Gather Essential Supplies Before You Start

Mushroom Spawn: Where to Buy or How to Make Your Own
When you decide to grow magic mushrooms at home, sourcing quality mushroom spawn is one of the most critical first steps you will take. Spawn is essentially the “seed” of your mushroom cultivation journey — it contains the live mycelium culture that will eventually produce your fruiting bodies.
Where to Buy Spawn
Reputable online vendors and specialty mycology suppliers are your best starting points. Look for suppliers that offer:
-
Verified culture strains with documented genetics
-
Contamination-free guarantees backed by lab-tested batches
-
Positive community reviews from trusted mycology forums and groups
-
Multiple spawn formats such as grain spawn, sawdust spawn, or liquid culture syringes
Always prioritize vendors who store and ship their spawn under temperature-controlled conditions, as heat and moisture exposure during transit can render spawn useless before it even reaches your door.
Making Your Own Spawn
Experienced cultivators often prefer to produce their own spawn to save costs and maintain genetic consistency. Common DIY spawn methods include:
-
Agar culture plates — used to isolate and expand mycelium from a healthy mushroom sample
-
Liquid culture (LC) — mycelium suspended in a nutrient-rich liquid solution, ideal for inoculating grain jars
-
Grain spawn jars — sterilized whole grains such as rye, wheat, or popcorn inoculated with a liquid culture or agar transfer
Making your own spawn requires a sterile work environment, a pressure cooker for sterilization, and ideally a still air box or laminar flow hood to minimize contamination risks.
Choosing the Right Substrate: Sawdust, Straw, or Wood Chips
With your spawn secured, the next decision that will significantly impact your harvest is selecting the appropriate growing substrate. The substrate is the nutrient-rich material on which your mycelium colonizes and from which your mushrooms ultimately fruit. Choosing the wrong substrate can severely limit yields, while the right one creates the ideal biological foundation for explosive growth.
Here is a breakdown of the three most popular substrate options for home cultivators:
| Substrate | Best For | Key Advantages | Potential Drawbacks |
|---|---|---|---|
| Sawdust | Wood-loving species | Dense nutrition, supports heavy flushes | Requires sterilization, longer colonization |
| Straw | Fast-colonizing species | Inexpensive, widely available, easy to pasteurize | Lower nutrient density than sawdust |
| Wood Chips | Outdoor beds or log-based grows | Long-lasting, mimics natural habitat | Very slow colonization, unpredictable yields |
Sawdust is widely considered one of the most productive substrates for indoor cultivation. Hardwood sawdust — particularly from oak, alder, or maple — provides a rich carbon source that mimics the natural environment of wood-decomposing fungi. It is typically combined with wheat bran or rice bran to increase nitrogen levels and boost yields.
Straw is the go-to choice for beginners who want fast results at a minimal cost. It pasteurizes easily using hot water immersion rather than high-pressure sterilization, making it far more accessible. However, because straw is lower in nutrients compared to sawdust, it generally produces lighter yields over fewer flushes.
Wood chips are best suited for outdoor cultivation setups or long-term garden bed projects. They decompose slowly, which means the substrate can remain productive for multiple seasons, but they are not ideal for indoor grows where you need predictable, controlled results.
Substrate Preparation Tips:
-
Always pasteurize or sterilize your substrate before inoculation to eliminate competing organisms
-
Maintain a substrate moisture content of approximately 60–70% — the substrate should feel damp but not dripping when squeezed
-
Consider supplementing your base substrate with nutrients like wheat bran, oat bran, or gypsum for improved yields
Must-Have Tools: Spray Bottles, Containers, and Monitoring Equipment
Now that we have covered spawn sourcing and substrate selection, it is time to assemble the physical toolkit that will support every stage of your grow. Having the right equipment on hand before you begin eliminates avoidable setbacks and allows you to maintain the precise environmental conditions that mushrooms demand.
Essential Growing Containers
Your choice of container will depend on the growing method you plan to use, but the following are universally useful:
-
Quart and half-pint mason jars — ideal for grain spawn inoculation and small-scale grows
-
Polypropylene grow bags — heat-resistant bags designed for sterilization, widely used for bulk substrate grows
-
Monotub containers — large, clear plastic storage bins used for fruiting chambers, offering ample space for colonized substrate
-
Shotgun fruiting chambers (SGFC) — perforated plastic bins that rely on passive airflow and manual fanning for fresh air exchange
Humidity and Moisture Tools
Maintaining consistent humidity is non-negotiable when you grow magic mushrooms at home. You will need:
-
Pump spray bottles — used multiple times daily to mist the interior walls of your fruiting chamber and maintain surface moisture without waterlogging your substrate
-
Digital hygrometer — measures relative humidity levels inside your growing space, ensuring they remain within the optimal 80–95% range during fruiting
-
Ultrasonic humidifier — for larger grows or automated setups, a humidifier can maintain humidity levels without constant manual intervention
Temperature Monitoring Equipment
Mushroom mycelium and fruiting bodies are highly sensitive to temperature fluctuations. Equip yourself with:
-
Digital thermometer — a dual-probe model that allows you to monitor both ambient room temperature and substrate temperature simultaneously
-
Heat mat with thermostat controller — provides gentle, consistent warmth during the colonization phase, particularly important in cooler climates
-
Infrared thermometer — useful for quickly checking surface temperatures of substrate blocks or jars without disturbing the growing environment
Sterilization and Contamination Prevention Tools
Contamination is the single greatest threat to any home mushroom grow. Stock these items before your first inoculation:
-
Pressure cooker (15 PSI minimum) — essential for sterilizing grain spawn and supplemented substrates
-
Isopropyl alcohol (70%) — used to sterilize work surfaces, tools, and glove-covered hands before any sterile procedure
-
Nitrile gloves and a face mask — minimize the introduction of bacteria and mold spores into your sterile materials
-
Still air box (SAB) — a clear plastic tote with arm holes that creates a low-turbulence environment for inoculation tasks when a laminar flow hood is not available
Quick-Reference Toolkit Checklist:
-
Mason jars or polypropylene grow bags
-
Monotub or shotgun fruiting chamber
-
Pump spray bottle (at least two)
-
Digital hygrometer
-
Digital thermometer with dual probes
-
Ultrasonic humidifier (optional but recommended)
-
Heat mat with thermostat controller
-
Pressure cooker (15 PSI)
-
Isopropyl alcohol (70%)
-
Nitrile gloves and face mask
-
Still air box
With this toolkit fully assembled, you will be positioned to maintain the clean, controlled conditions that separate successful harvests from failed attempts. With this in mind, next, we’ll see how to prepare your growing medium to set the stage for maximum colonization success.
Prepare Your Growing Medium for Maximum Success
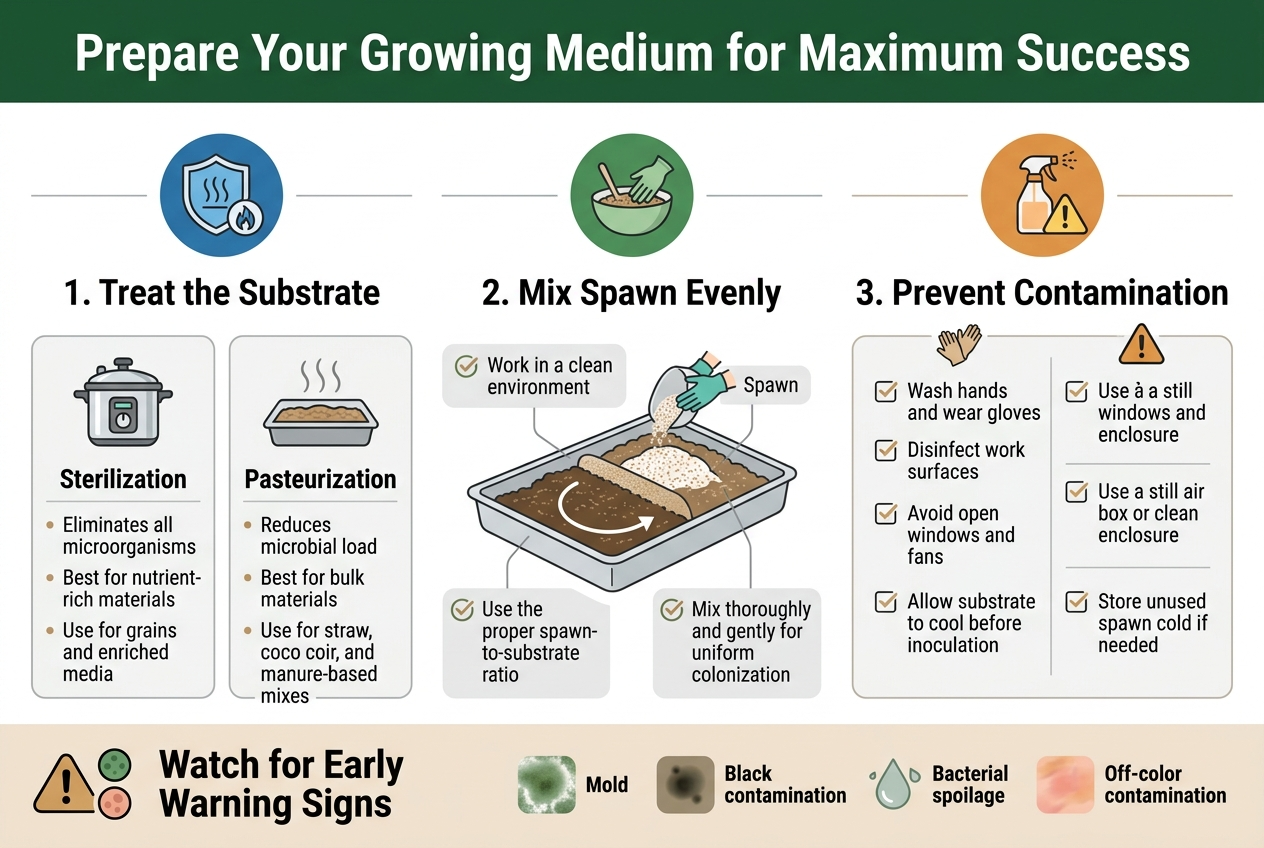
How to Sterilize or Pasteurize Your Substrate Effectively
Sterilization and pasteurization are critical steps when you want to grow magic mushrooms at home successfully. Sterilization (using a pressure cooker at 15 PSI for 2–2.5 hours) eliminates all competing organisms from grain or supplemented sawdust substrates. Pasteurization, typically done at 160–180°F for 1–2 hours, suits bulk substrates like coco coir or straw, killing most contaminants while preserving beneficial microbes that suppress mold.
Mixing and Distributing Spawn Evenly for Healthy Colonization
Once your substrate cools to room temperature, introduce spawn using a sterile glove box or flow hood. Distribute spawn evenly throughout the substrate — aim for a 10–20% spawn-to-substrate ratio — to encourage uniform mycelium colonization and reduce contamination windows.
Avoiding Contamination from the Start
| Contamination Risk | Prevention Strategy |
|---|---|
| Unclean hands/tools | Always use gloves and alcohol-sterilized tools |
| Premature opening | Wait until substrate cools fully before inoculating |
| Wet substrate | Maintain field capacity moisture levels only |
Work swiftly, minimize air exposure, and inspect for green, black, or pink mold regularly throughout colonization.
Master the Five Proven Home Growing Methods
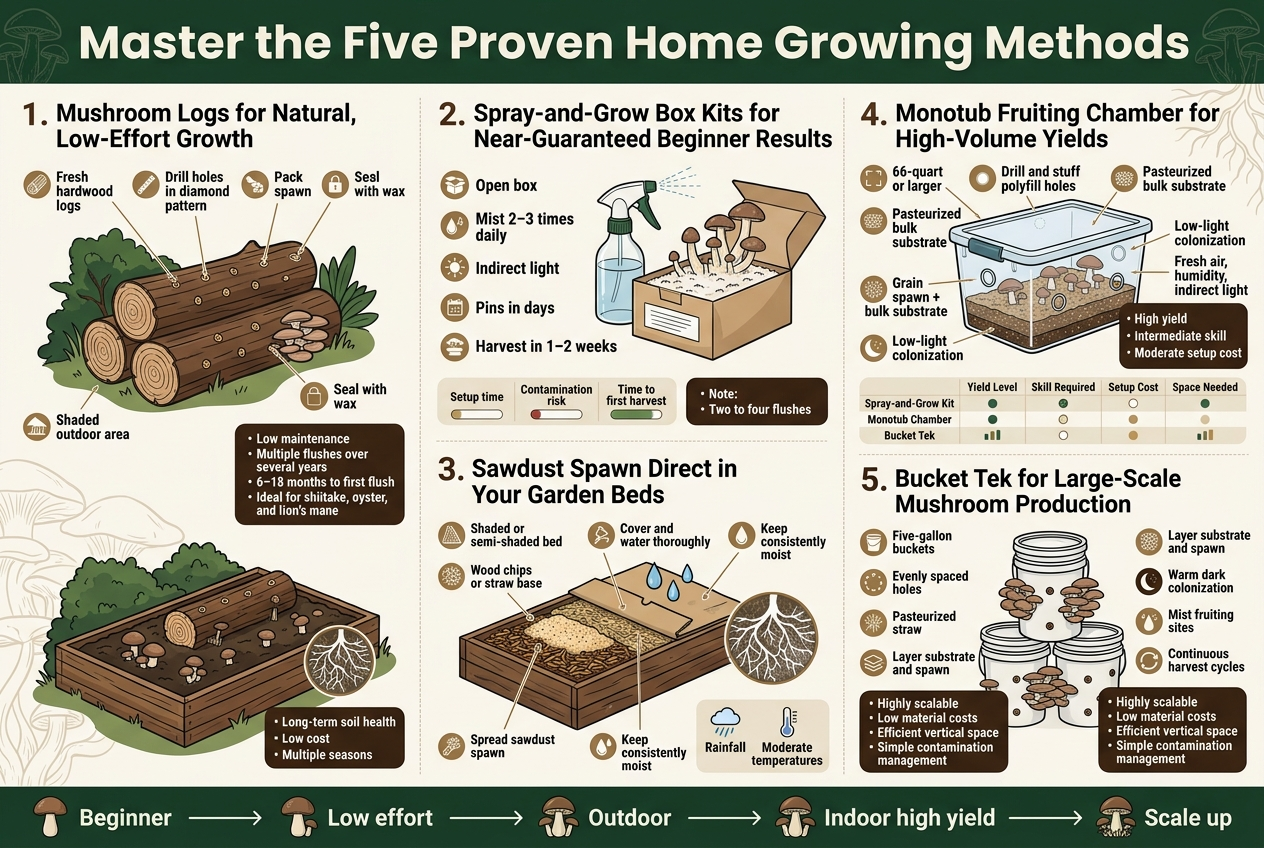
Method 1: Mushroom Logs for Natural, Low-Effort Growth
Growing mushrooms on logs is one of the oldest and most rewarding techniques available to home cultivators. This method mimics the way mushrooms naturally fruit in forest environments, making it a highly sustainable and beginner-friendly approach when you want to grow magic mushrooms at home.
To get started with log cultivation, you’ll need freshly cut hardwood logs — oak, maple, and alder are among the most popular choices. The logs are inoculated with mushroom spawn by drilling holes in a specific pattern, packing them with spawn, and then sealing the holes with wax to lock in moisture and prevent contamination.
Key advantages of the log method include:
-
Extremely low maintenance once inoculated
-
Can produce multiple flushes over several years
-
Requires no climate-controlled grow room
-
Produces naturally flavored, high-quality mushrooms
-
Ideal for outdoor cultivation in shaded garden areas
The main trade-off is patience. Logs typically take anywhere from six to eighteen months before they produce their first flush. However, once they begin fruiting, a single log can continue delivering harvests for up to five or more years with minimal intervention.
Step-by-step overview for log inoculation:
-
Source freshly cut hardwood logs (ideally less than three months old)
-
Drill holes in a diamond pattern, spaced approximately six inches apart
-
Pack each hole tightly with mushroom plug spawn or grain spawn
-
Seal every hole with cheese wax or beeswax to prevent moisture loss
-
Place logs in a shaded, humid outdoor area
-
Soak logs periodically during dry weather to maintain moisture levels
-
Wait for the colonization and fruiting cycle to complete naturally
This method is particularly well-suited for species like shiitake, oyster, and lion’s mane, and it requires very little hands-on time after the initial setup — making it ideal for gardeners who prefer a set-it-and-forget-it approach.
Method 2: Spray-and-Grow Box Kits for Near-Guaranteed Beginner Results
If you’re brand new to home mushroom cultivation, spray-and-grow kits offer the most forgiving and accessible entry point available. These pre-inoculated kits come with a fully colonized substrate block sealed inside a box, meaning all the difficult work — sterilization, inoculation, and colonization — has already been done for you.
How spray-and-grow kits work:
-
Open the box and expose the colonized substrate block to air
-
Mist the surface with water two to three times daily
-
Maintain humidity levels and indirect light
-
Watch pins form within days and harvest fully grown mushrooms within one to two weeks
The near-guaranteed success rate of these kits makes them exceptionally popular among beginners who want to grow mushrooms at home without investing heavily in equipment or risking expensive contamination failures.
Comparing spray-and-grow kits to other beginner methods:
| Feature | Spray-and-Grow Kit | Log Method | Sawdust Spawn |
|---|---|---|---|
| Setup time | Minutes | Several hours | Moderate |
| Time to first harvest | 1–2 weeks | 6–18 months | 2–4 months |
| Equipment required | Minimal | Moderate | Low to moderate |
| Contamination risk | Very low | Low | Moderate |
| Yield per cycle | Moderate | High (long-term) | Moderate to high |
| Cost | Higher per yield | Lower long-term | Affordable |
One important consideration is that while kits are convenient, they typically deliver a limited number of flushes — usually two to four — before the substrate becomes exhausted. For those who want ongoing production, progressing to more advanced methods is the logical next step.
Method 3: Sawdust Spawn Direct in Your Garden Beds
With this in mind, next, we’ll explore a method that bridges the gap between container cultivation and outdoor growing — using sawdust spawn directly in garden beds. This technique is particularly effective for species like oyster mushrooms, wine caps, and king stropharia, and it allows you to integrate mushroom production seamlessly into an existing garden space.
Sawdust spawn consists of hardwood sawdust fully colonized with mushroom mycelium. When introduced into a garden bed environment, it creates a self-sustaining mycelial network that can fruit repeatedly across multiple growing seasons.
How to prepare a garden bed for sawdust spawn:
-
Choose a shaded or semi-shaded garden area with good moisture retention
-
Clear the bed and lay down a thick layer of wood chips or straw as a base
-
Spread sawdust spawn evenly across the bed layer
-
Cover the spawn layer with another thick layer of wood chips or cardboard
-
Water the bed thoroughly to jumpstart colonization
-
Keep the area consistently moist throughout the colonization period
-
Allow the mycelium to colonize fully before expecting fruiting bodies
Benefits of garden bed sawdust spawn:
-
Integrates naturally with existing garden ecosystems
-
Requires minimal ongoing effort after initial setup
-
Builds long-term soil health through mycelial networks
-
Produces abundant harvests during ideal weather conditions
-
Very low cost compared to indoor methods
The primary challenge with this method is that fruiting is heavily dependent on outdoor weather conditions. Consistent rainfall and moderate temperatures trigger the best results, while extended dry or cold spells can delay or suppress fruiting. Strategic watering can help compensate during drier periods.
Method 4: Monotub Fruiting Chamber for High-Volume Yields
Previously, I’ve outlined methods that work best in outdoor or semi-outdoor settings. Now we move indoors, where the monotub fruiting chamber has become one of the most celebrated techniques among serious home cultivators aiming for high-volume, consistent production.
A monotub is simply a large, lidded plastic storage container that functions as a self-contained growing and fruiting environment. The substrate — typically a blend of grain spawn and bulk substrate such as coco coir, vermiculite, or pasteurized straw — is loaded into the tub, colonized, and then triggered to fruit by adjusting the environmental conditions inside.
Why the monotub method delivers impressive yields:
-
Large surface area allows for prolific pinning across the entire substrate mass
-
The enclosed environment retains humidity effectively with minimal effort
-
Requires relatively simple and inexpensive equipment
-
Allows growers to manage multiple tubs simultaneously for continuous harvests
-
Substrate can be pasteurized at home rather than requiring high-pressure sterilization
Standard monotub setup process:
-
Source or repurpose a large lidded plastic storage tub (66-quart or larger recommended)
-
Drill and stuff polyfill holes on the sides for passive air exchange
-
Prepare and pasteurize your bulk substrate
-
Mix colonized grain spawn with bulk substrate at a recommended ratio
-
Load the mixed substrate into the tub and seal
-
Allow full colonization at room temperature in low-light conditions
-
Once fully colonized, introduce fruiting conditions — fan for fresh air exchange, mist for humidity, and indirect light
-
Harvest mushrooms as they reach peak maturity before the veil breaks
Comparison of indoor growing methods for yield potential:
| Method | Yield Level | Skill Required | Setup Cost | Space Needed |
|---|---|---|---|---|
| Spray-and-Grow Kit | Low to moderate | Beginner | Low | Minimal |
| Monotub Chamber | High | Intermediate | Moderate | Medium |
| Bucket Tek | Very high | Intermediate+ | Moderate | Medium to large |
The monotub method rewards cultivators who pay close attention to environmental triggers and contamination prevention. Maintaining the right balance of fresh air exchange and humidity is the most critical skill to develop when mastering this approach.
Method 5: Bucket Tek for Large-Scale Mushroom Production
Now that we have covered high-yield indoor methods, we arrive at one of the most scalable techniques available to home growers — Bucket Tek. Designed for cultivators who want to push production volume significantly higher than what a monotub can deliver, this method uses five-gallon plastic buckets loaded with pasteurized substrate and inoculated with mushroom spawn.
Bucket Tek is particularly well-known for its use with oyster mushrooms, though it adapts well to several other species. The buckets are drilled with multiple holes around the exterior, which serve as the primary fruiting sites. As the colonized mycelium fills the bucket, mushroom clusters push through each hole and develop outward — producing striking, visually distinctive clusters that can be harvested cleanly and easily.
Setting up a Bucket Tek system:
-
Drill evenly spaced holes (approximately one to two inches in diameter) around the sides of each five-gallon bucket
-
Prepare and pasteurize your chosen bulk substrate — straw is the most commonly used material for this method
-
Allow the substrate to cool completely before inoculation
-
Layer substrate and spawn alternately inside the bucket, starting and ending with substrate
-
Seal the bucket with its lid and allow full colonization in a warm, dark space
-
Once fully colonized, move buckets to the fruiting area with appropriate humidity and airflow
-
Mist the holes regularly to encourage pinning at the fruiting sites
-
Harvest clusters as they approach maturity and before spore drop
Advantages of Bucket Tek for large-scale production:
-
Highly scalable — add as many buckets as your space allows
-
Efficient use of vertical space in your growing area
-
Low material costs, especially when using straw as a substrate
-
Staggered inoculation of multiple buckets allows continuous, overlapping harvest cycles
-
Simple to manage contamination — any single contaminated bucket can be removed without affecting others
The modular nature of Bucket Tek makes it one of the most practical methods for growers who are serious about scaling up their operation. By maintaining a rotating cycle of buckets at different stages of colonization and fruiting, it becomes entirely feasible to maintain a near-continuous harvest schedule throughout the year.
Control the Perfect Growing Environment at Every Stage

Incubation Phase: Temperature, Humidity, and Darkness Tips
During the incubation phase, maintaining a stable temperature between 75–80°F (24–27°C) is critical when you grow magic mushrooms at home. Keep the substrate in complete darkness to encourage mycelium colonization. Humidity should remain around 90–95% to prevent the substrate from drying out. Avoid disturbing the container unnecessarily, as contamination risk increases with frequent handling. Consistent conditions during this phase directly determine how successfully your mycelium network establishes before fruiting begins.
Triggering Fruiting with Fresh Air, Light, and Proper Humidity
Once colonization is complete, transitioning to the fruiting stage requires deliberate environmental shifts. Lower the temperature slightly to 70–75°F (21–24°C), introduce indirect light for 12 hours daily, and increase fresh air exchange to reduce CO₂ buildup. Maintaining humidity at 90–95% while misting lightly prevents surface drying. These combined triggers signal the mycelium to begin producing fruiting bodies, maximizing your overall yield and development speed throughout each flush.
Optimize Lighting Conditions for Bigger, Better Harvests
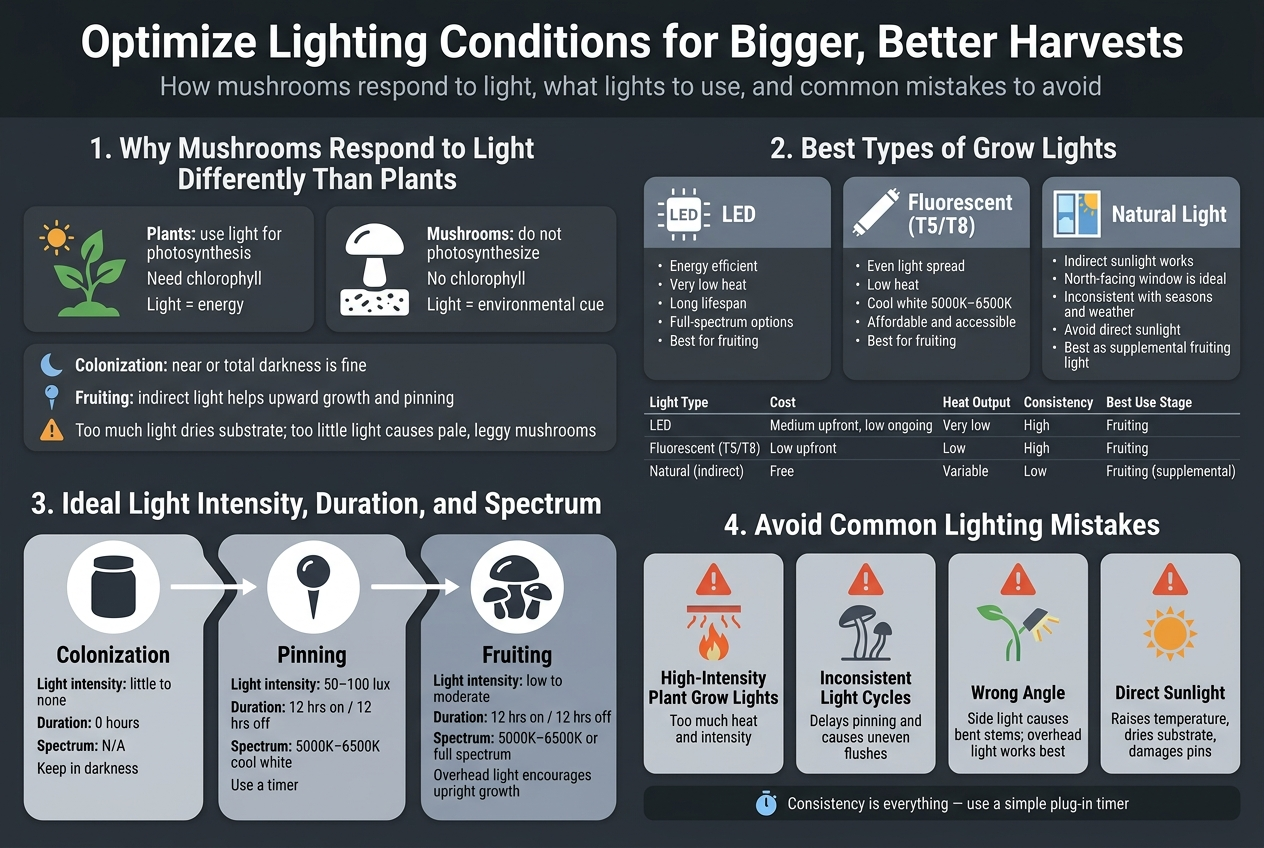
Why Mushrooms Respond to Light Differently Than Plants
When you decide to grow magic mushrooms at home, one of the first surprises is discovering that mushrooms relate to light in a fundamentally different way than the plants you may be used to cultivating. Plants rely on light as their primary energy source through photosynthesis — mushrooms do not. Fungi lack chlorophyll entirely, meaning they cannot convert light into food. Instead, mushrooms draw all their energy from the substrate they grow on.
So why does light matter at all? Light serves as an environmental cue for mushrooms. It signals directional growth, triggers pinning (the formation of tiny mushroom heads), and helps regulate the timing and density of your fruiting bodies. Think of it less like feeding a plant and more like setting an alarm clock. The right light at the right time tells your mycelium that it has broken through to the surface and that it is time to produce fruiting bodies.
Key differences to keep in mind:
-
Mushrooms do not need light to grow mycelium — the colonization stage can occur in near or total darkness.
-
Light becomes important during fruiting — once pinning begins, indirect or ambient light helps direct upward growth and encourages uniform canopy development.
-
Too much intense light can dry out the surface of your substrate, disrupting humidity and stalling growth.
-
Too little light during fruiting can produce pale, leggy mushrooms with thin stems and small caps.
Understanding this distinction is essential for anyone serious about optimizing their home grow operation.
Best Types of Grow Lights: LED, Fluorescent, and Natural Light
With this in mind, let’s explore the practical lighting options available to home growers. Not all light sources are created equal when it comes to cultivating mushrooms, and choosing the right one can make a measurable difference in your harvest size and quality.
LED Grow Lights
LED lights have become increasingly popular among home growers for several compelling reasons:
-
Energy efficiency — LEDs consume significantly less electricity than traditional bulbs, lowering your running costs.
-
Low heat output — because mushrooms thrive in cooler, humid environments, the minimal heat produced by LEDs helps maintain stable growing conditions without drying out your substrate.
-
Longevity — LEDs have a much longer lifespan than fluorescent or incandescent alternatives.
-
Full-spectrum options — modern LED panels can be tuned to emit specific wavelengths relevant to mushroom growth cues.
For mushroom cultivation, you do not need high-intensity horticultural LEDs designed for heavy-flowering plants. A simple, low-wattage LED panel or even standard household LED bulbs placed at a distance are more than sufficient.
Fluorescent Lights
Fluorescent tubes, particularly T5 and T8 varieties, have been a staple in mushroom cultivation for decades:
-
They produce a broad, even spread of light that covers a wide surface area effectively.
-
They operate at low temperatures, similar to LEDs, making them safe for humidity-sensitive growing environments.
-
Cool white fluorescents (5000K–6500K color temperature) are widely recommended for fruiting chambers.
-
They are generally affordable and widely available, making them an accessible choice for beginners.
The main drawback of fluorescents is that they are less energy-efficient than LEDs over the long term and have a shorter usable lifespan.
Natural Light
Natural, indirect sunlight can absolutely be used when growing magic mushrooms at home:
-
North-facing windows in the Northern Hemisphere provide consistent, indirect light without the harsh intensity of direct sun exposure.
-
Natural light follows a built-in photoperiod cycle, which can actually be beneficial for signaling fruiting stages.
-
However, natural light is inconsistent — seasonal changes, cloudy days, and geographic location all affect the amount and quality of light your grow receives.
-
Direct sunlight must be avoided as it raises temperatures, reduces humidity, and can physically damage delicate pins and fruiting bodies.
| Light Type | Cost | Heat Output | Consistency | Best Use Stage |
|---|---|---|---|---|
| LED | Medium upfront, low ongoing | Very Low | High | Fruiting |
| Fluorescent (T5/T8) | Low upfront | Low | High | Fruiting |
| Natural (indirect) | Free | Variable | Low | Fruiting (supplemental) |
Ideal Light Intensity, Duration, and Spectrum for Each Growth Stage
Now that we have covered the types of lighting available, let’s break down exactly how much light, for how long, and in what spectrum you should be providing at each stage of the growing cycle.
Colonization Stage (Mycelium Growth)
-
Light intensity needed: Little to none
-
Recommended duration: 0 hours (darkness is perfectly acceptable and often preferred)
-
Spectrum: Not applicable
-
Key tip: During colonization, your primary focus should be on temperature and humidity — not light. Covering your substrate jars or bags and keeping them in a dark cupboard or shelf is entirely appropriate and will not negatively affect mycelium development.
Pinning Stage (Primordia Formation)
-
Light intensity needed: Low to moderate (50–100 lux is generally sufficient)
-
Recommended duration: 12 hours on / 12 hours off
-
Spectrum: Blue-white light in the range of 5000K–6500K is most commonly associated with triggering and supporting pin formation
-
Key tip: Introducing a consistent light cycle at this stage is one of the most effective ways to encourage even and abundant pinning across your entire substrate surface.
Fruiting Stage (Cap Development)
-
Light intensity needed: Low to moderate — consistency matters more than intensity
-
Recommended duration: 12 hours on / 12 hours off (maintain the cycle established during pinning)
-
Spectrum: Continued blue-white or full-spectrum light supports healthy cap development and directional upward growth
-
Key tip: Mushrooms are phototropic — they will grow toward the light source. Positioning your light consistently above the fruiting chamber encourages straight, well-formed stems and evenly developed caps.
| Growth Stage | Light Duration | Intensity | Spectrum (Color Temp) |
|---|---|---|---|
| Colonization | 0 hours (darkness) | None required | N/A |
| Pinning | 12 hrs on / 12 hrs off | 50–100 lux | 5000K–6500K (cool white) |
| Fruiting | 12 hrs on / 12 hrs off | Low–Moderate | 5000K–6500K or full spectrum |
Using a simple plug-in timer to automate your light cycles removes the guesswork entirely and ensures your mushrooms receive consistent cues day after day.
Avoiding Common Lighting Mistakes That Stunt Growth
Previously, many beginner growers assumed that more light automatically meant better results — an understandable assumption if you come from a plant-growing background. With mushrooms, this logic can actively harm your harvest. Here are the most critical lighting mistakes to avoid when you grow magic mushrooms at home:
Mistake 1: Using High-Intensity Grow Lights Designed for Plants
Heavy-duty horticultural LEDs or HPS (high-pressure sodium) lights designed for cannabis or tomato cultivation are far too intense for mushroom fruiting chambers. They generate excessive heat, reduce relative humidity rapidly, and can bleach or physically damage delicate fruiting bodies. Always opt for low-wattage, ambient-level lighting.
Mistake 2: Skipping Light Entirely During Fruiting
While mushrooms do not need light to survive, completely dark fruiting environments consistently produce inferior results:
-
Mushrooms grow leggy and elongated, reaching desperately in all directions for a light cue that never comes.
-
Caps remain small and underdeveloped.
-
Pinning can be uneven or sparse.
Even a modest amount of indirect ambient light — from a window or a basic LED — makes a meaningful difference.
Mistake 3: Inconsistent Light Cycles
Irregular light schedules confuse the fruiting trigger mechanism. Flipping lights on and off randomly, or allowing dramatically variable natural light exposure, can delay pinning, reduce pin density, and produce unevenly developed flushes. Consistency is everything — use a timer and stick to a reliable schedule.
Mistake 4: Placing Lights at the Wrong Angle
Because mushrooms are phototropic, the angle and position of your light source directly affects the shape and direction of your fruiting bodies:
-
Side lighting causes mushrooms to grow laterally, producing bent, curved stems.
-
Overhead lighting encourages straight, upright growth and well-rounded caps.
-
Keep your light source positioned directly above your fruiting chamber whenever possible.
Mistake 5: Allowing Direct Sunlight Exposure
Direct sunlight is one of the most damaging environmental factors for a home mushroom grow. Beyond its intensity, direct sun:
-
Raises surface temperature dramatically, stressing the mycelium and fruiting bodies.
-
Evaporates moisture from the substrate surface far faster than passive ventilation, leading to cracking, shrinkage, and aborted pins.
-
Creates unpredictable light cycles that vary with seasons, weather, and time of day.
If you are relying on natural light, always filter it through a curtain or frosted glass, and monitor temperature and humidity closely whenever sunlight conditions change.
Troubleshoot the Most Common Growing Problems
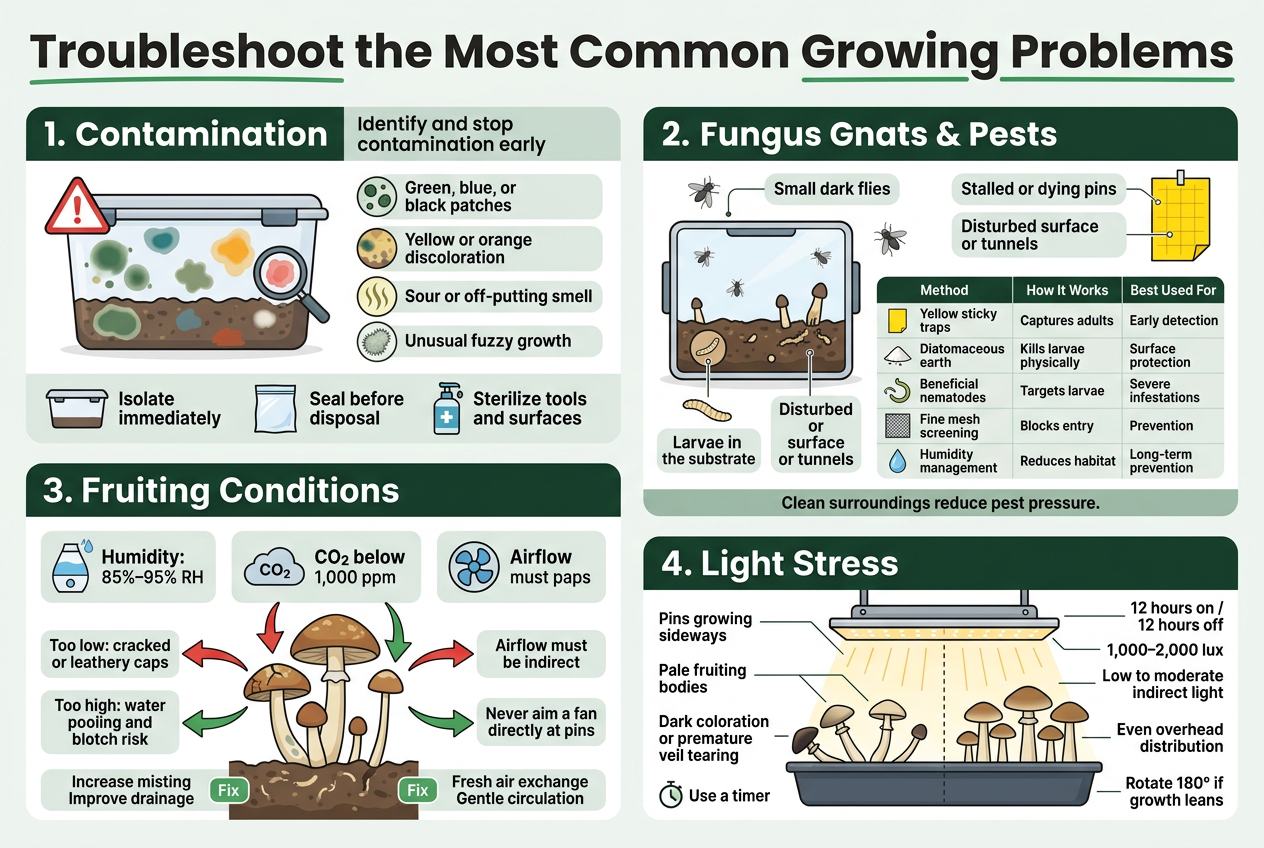
Identifying and Managing Contamination Before It Spreads
Contamination is the most common threat when you grow magic mushrooms at home. Watch for green, black, or pink mold patches, sour odors, or slimy textures on your substrate. Isolate affected containers immediately to prevent cross-contamination. Maintaining strict sterile technique during inoculation and colonization dramatically reduces contamination risk and keeps your grow environment clean and productive.
Dealing with Fungus Gnats and Other Pests
Fungus gnats thrive in moist growing environments and can devastate your fruiting blocks. Use sticky traps near your grow space and ensure proper airflow to discourage infestations. Keeping your grow area sealed and clean minimizes pest entry points significantly.
Fixing Poor Fruiting Conditions: Humidity, CO2, and Airflow Issues
Poor fruiting often results from low humidity, excessive CO2, or inadequate airflow. Maintain humidity between 90–95% during fruiting and fan your chamber regularly to exchange fresh air. High CO2 causes elongated, weak stems, while insufficient humidity prevents pin formation entirely.
Recognizing Light Stress and Adjusting Accordingly
Light stress presents as bleached or abnormally oriented mushrooms. Ensure indirect, consistent low-intensity lighting rather than direct harsh light. Adjusting your light schedule and intensity corrects these issues quickly, encouraging healthy, evenly developed fruiting bodies throughout your harvest cycle.
Harvest, Store, and Use Your Homegrown Mushrooms
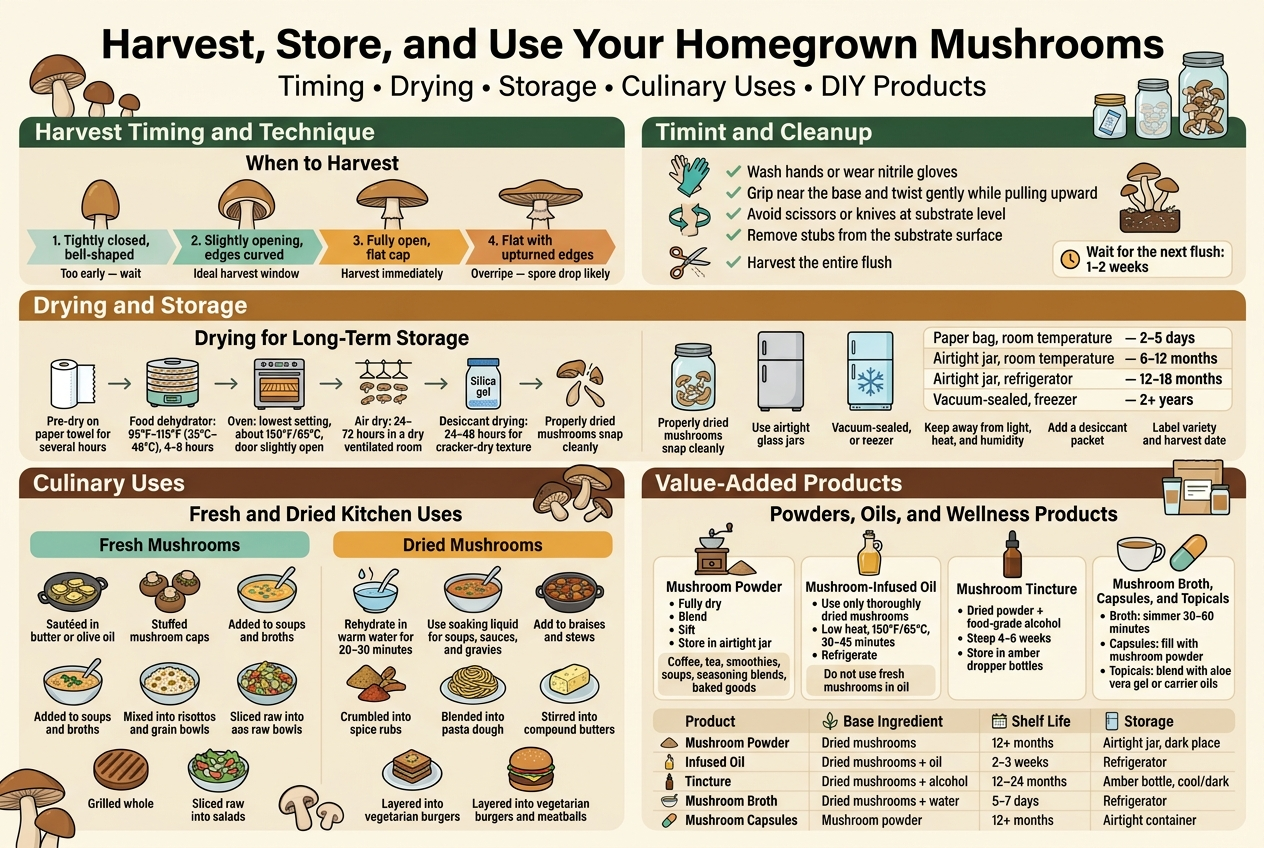
When and How to Harvest for Best Flavor and Texture
Timing your harvest correctly is critical when you grow magic mushrooms at home. Pick them just before the veil beneath the cap begins to tear for peak potency and texture. Twist gently at the base rather than cutting to avoid damaging surrounding pins.
Drying and Preserving Mushrooms for Long-Term Storage
Use a food dehydrator set to low heat or a desiccant-filled airtight container to preserve freshness. Store dried mushrooms in sealed glass jars away from light and moisture to maximize shelf life significantly.
Creative Culinary Uses for Fresh and Dried Homegrown Mushrooms
Fresh homegrown mushrooms excel in stir-fries, soups, and sautés, while dried varieties rehydrate beautifully in broths and sauces. Their earthy depth enhances pasta, risotto, and grain bowls effortlessly.
Making DIY Mushroom Powders, Infused Oils, and Wellness Products
Grind fully dried mushrooms into fine powder using a coffee grinder for smoothies, teas, or capsules. Infuse olive oil with dried mushrooms over low heat for a flavorful, functional culinary staple packed with natural compounds.
Scale Up and Expand Your Mushroom Growing Operation
Moving from Small Batches to Larger Growing Setups
Once you’ve mastered small-scale cultivation, scaling up your operation becomes a natural next step. Transitioning to larger setups means investing in bigger fruiting chambers, additional substrate blocks, and more efficient sterilization equipment. Batch scheduling — staggering multiple grows simultaneously — ensures a continuous, steady harvest rather than sporadic flushes, maximizing your overall yield and efficiency.
Exploring Medicinal Mushrooms: Reishi, Lion’s Mane, and Chaga
Now that we have covered scaling basics, expanding into medicinal varieties like Reishi, Lion’s Mane, and Chaga opens exciting new possibilities. Each species has unique substrate preferences and growth timelines, rewarding growers who diversify their setups. Joining online mushroom cultivation communities and forums further sharpens your skills, connecting you with experienced cultivators who share advanced techniques, troubleshooting advice, and resources to continuously elevate your home growing operation.
Embrace the Eco-Friendly Benefits of Home Mushroom Cultivation
How Mushroom Growing Reduces Waste and Carbon Footprint
When you grow magic mushrooms at home, you actively participate in a low-impact cultivation cycle. Mushrooms thrive on agricultural byproducts like straw, sawdust, and coffee grounds, diverting these materials from landfills. Compared to conventional farming, home mushroom cultivation requires minimal water, no pesticides, and produces a significantly smaller carbon footprint, making it one of the most environmentally responsible food-growing practices available to everyday households.
Improving Soil Health with Spent Substrate
Once your mushrooms have fully fruited, the remaining substrate is far from useless. Spent substrate is rich in fungal mycelium and organic matter, making it an exceptional soil amendment. Incorporating it into garden beds improves soil structure, boosts microbial diversity, and enhances nutrient retention. This closed-loop approach means that every stage of your home grow magic mushrooms journey contributes positively back to the earth, eliminating unnecessary waste.
Contributing to Biodiversity Through Diverse Mushroom Species
Cultivating a variety of mushroom species at home supports broader ecological awareness and biodiversity. Each species plays a unique role in decomposition, nutrient cycling, and ecosystem balance. By growing diverse varieties, home cultivators help preserve genetic diversity and deepen public appreciation for fungi’s critical environmental roles, fostering a culture of sustainability that extends well beyond the growing space itself.
7 FAQ
Can You Legally Grow Magic Mushrooms at Home?
Laws vary wildly by location. In some U.S. states and countries, growing psilocybin mushrooms is decriminalized or even legal for personal use. Always research your local laws before you grow magic mushrooms at home, since penalties can range from minor fines to serious criminal charges depending on where you live.
What’s the Easiest Mushroom Variety for Beginners?
Psilocybe cubensis is hands-down the best starting point. It’s forgiving, grows fast, and thrives in basic home setups without needing fancy equipment or expert-level skills.
How Long Does It Take to Grow Mushrooms at Home?
From inoculation to first harvest, expect roughly 4–6 weeks. Colonization takes 2–3 weeks, and once you see pins forming, full mushrooms are ready within 5–7 days.
Why Is My Substrate Turning Green or Black?
That’s contamination, usually from mold. Green means Trichoderma mold has taken over. Toss that block immediately and sanitize everything before starting fresh to stop it from spreading.
How Many Harvests Can You Get From One Grow?
Most setups produce 3–5 flushes per substrate block. Yields drop with each flush, but that first and second harvest are usually the most productive by far.
What Humidity Level Do Mushrooms Need?
Keep humidity between 80–95% during fruiting. A basic hygrometer helps you track this accurately so your mushrooms don’t dry out before they’re fully developed.
Do Mushrooms Need Light to Grow?
They don’t photosynthesize, but indirect, ambient light for 12 hours a day helps trigger pinning and guides proper growth direction — brighter isn’t better here.
Growing mushrooms at home is a genuinely rewarding journey that blends science, patience, and creativity. From selecting the right beginner-friendly variety like oyster or shiitake mushrooms, to mastering substrate preparation, inoculation, incubation, and harvesting, every step builds on the last. Whether you choose a simple spray-and-grow kit, a bucket tek setup, a mushroom log, or a fully automated monotub fruiting chamber, there is a method that fits your space, budget, and experience level. Controlling temperature, humidity, lighting, and air exchange are the keys that separate a thriving grow from a failed one, and troubleshooting common problems like contamination or poor fruiting conditions becomes easier with practice.
Beyond the harvest itself, home mushroom cultivation carries real eco-friendly benefits, from reducing food waste by repurposing agricultural byproducts to lowering your carbon footprint compared to conventional food production. As your confidence grows, you can scale up your operation, explore exotic varieties, experiment with medicinal mushrooms, and even share your knowledge with others. The most important step is simply starting. Pick one method, gather your supplies, and give it a try. Each flush of fresh, homegrown mushrooms will make the effort feel completely worth it.
Psilocybin Safety Beyond Psychotropics
Psilocybin Safety Beyond Psychotropics: A Comprehensive Guide to Medication Interactions and Safe Usage
Introduction
Psilocybin Safety Beyond Psychotropics represents a critical area of medical understanding that extends far beyond traditional psychoactive substance considerations. As psilocybin gains recognition for its therapeutic potential, understanding its complex interactions with conventional medications becomes paramount for ensuring user safety and treatment efficacy.

This comprehensive guide explores the intricate relationships between psilocybin and various pharmaceutical compounds, providing essential knowledge for anyone considering psilocybin use while managing existing health conditions with prescription medications.
Understanding Psilocybin’s Journey Through Your Body
How Your System Processes Psilocybin
Your body transforms psilocybin through a sophisticated biological process that begins the moment you consume it. The compound rapidly converts to psilocin through enzymatic action, primarily involving alkaline phosphatase enzymes in your intestinal tract and liver.
Absorption and Distribution:
- Peak blood concentrations occur within 60-90 minutes of ingestion
- The compound crosses the blood-brain barrier efficiently
- Elimination typically completes within 24 hours through urinary excretion
Metabolic Pathways:
Your liver’s cytochrome P450 enzyme system plays a crucial role in breaking down psilocybin compounds. These same enzymes process many common medications, creating potential competition that can alter the effects and safety profile of both substances.
Neurochemical Changes and Brain Function
Psilocybin primarily targets your brain’s serotonin 2A receptors, but its influence extends throughout multiple neurotransmitter systems. This widespread impact creates the foundation for understanding Psilocybin Safety Beyond Psychotropics.
Serotonin System Disruption:
- Direct binding to 5-HT2A, 5-HT2C, and 5-HT1A receptors
- Temporary alterations in serotonin signaling patterns
- Effects lasting 4-8 hours with potential residual changes for 24-48 hours
Secondary Neurotransmitter Effects:
Psilocybin indirectly influences dopamine release in reward pathways, modulates GABA inhibitory systems, and affects norepinephrine levels, creating complex interactions with medications targeting these same systems.
Individual Factors Affecting Psilocybin Processing
Your unique biological profile significantly influences how psilocybin interacts with other medications. Age-related changes in liver function can slow metabolism, while genetic variations in enzyme production create substantial individual differences in processing speed.
Critical Variables Include:
- Body weight and composition affecting distribution
- Liver and kidney function status
- Genetic polymorphisms in metabolic enzymes
- Hormonal differences affecting elimination rates
High-Risk Medication Categories Requiring Special Attention

Antidepressants and Psychiatric Medications
SSRI and SNRI Interactions:
Selective serotonin reuptake inhibitors create complex interactions with psilocybin by blocking serotonin reabsorption while psilocybin floods the same receptors. This combination can reduce psilocybin’s effectiveness while potentially increasing side effect risks.
Tricyclic Antidepressants:
These older medications carry higher interaction risks due to their broader receptor activity and longer elimination times. Users typically require extended medication-free periods before safe psilocybin use.
MAO Inhibitors – Critical Warning:
Monoamine oxidase inhibitors present the highest risk category for psilocybin interactions. The combination can trigger severe hypertensive crises and requires extended discontinuation periods of 6-8 weeks minimum.
Cardiovascular Medication Interactions
Beta-Blockers and Heart Rate Control:
Psilocybin can increase heart rate and blood pressure, potentially counteracting beta-blocker medications. This interaction may mask important cardiovascular symptoms or create unpredictable blood pressure fluctuations.
Blood Thinning Medications:
While direct interactions remain uncommon, psilocybin’s effects on blood vessel dilation and potential for physical activity during experiences may increase bleeding risks for users on anticoagulant therapy.
ACE Inhibitors and Calcium Channel Blockers:
These medications may interact unpredictably with psilocybin’s cardiovascular effects, potentially causing dangerous blood pressure changes that require careful medical monitoring.
Central Nervous System Medication Conflicts
Benzodiazepine Interference:
Anxiety medications like lorazepam, alprazolam, and clonazepam can significantly reduce or completely block psilocybin’s effects by counteracting its excitatory actions on brain receptors.
ADHD Stimulant Combinations:
Combining psilocybin with methylphenidate, amphetamines, or similar stimulants creates unpredictable cardiovascular and psychological effects that may overwhelm the user’s ability to manage the experience safely.
Sleep Medications and Sedatives:
Z-drugs, barbiturates, and other sleep aids can create dangerous interactions by affecting consciousness levels and respiratory function during psilocybin experiences.
Recognizing Dangerous Interactions and Emergency Situations

Life-Threatening Complications Requiring Immediate Medical Attention
Serotonin Syndrome Recognition:
This potentially fatal condition develops when excessive serotonin activity overwhelms your nervous system. Emergency symptoms include high fever, severe muscle rigidity, rapid heart rate, extreme agitation, and altered consciousness levels.
Cardiovascular Crisis Indicators:
Seek immediate emergency care for chest pain, severe headaches, breathing difficulties, irregular heartbeat, or blood pressure readings above 180/120 mmHg during or after psilocybin use.
Central Nervous System Depression:
Dangerous combinations can suppress vital functions, causing slow or irregular breathing, extreme confusion, loss of coordination, or unresponsiveness requiring emergency intervention.
Moderate Risk Scenarios Requiring Medical Monitoring
Medication Effectiveness Reduction:
Psilocybin may temporarily alter how your body processes essential medications, potentially reducing their therapeutic effects and requiring dosage adjustments or alternative treatments.
Unpredictable Side Effect Profiles:
Medication combinations can produce unexpected reactions that don’t fit typical patterns, making it difficult to predict or manage adverse effects without professional medical guidance.
Extended Recovery Complications:
Some interactions may prolong psilocybin’s effects or create persistent symptoms requiring extended medical observation and supportive care.
Early Warning Signs Requiring Immediate Assessment
Physical Warning Indicators:
Monitor for persistent nausea, severe headaches, chest discomfort, breathing changes, excessive sweating, tremors, or unusual muscle tension that develops during or after psilocybin use.
Mental Health Red Flags:
Seek help for extreme agitation, panic that doesn’t respond to calming techniques, persistent confusion, memory problems, or suicidal thoughts that emerge during the experience.
Safe Usage Protocols and Preparation Strategies
Medication Management and Discontinuation Planning
Professional Tapering Protocols:
Work exclusively with qualified healthcare providers to develop safe medication reduction schedules. Abrupt discontinuation of many psychiatric and cardiac medications can create serious health risks independent of psilocybin considerations.
Minimum Clearance Periods:
Different medications require varying elimination times before safe psilocybin use:
- SSRIs: 2-4 weeks minimum
- MAO Inhibitors: 6-8 weeks minimum
- Tricyclic antidepressants: 2-3 weeks minimum
- Long-acting benzodiazepines: 1-2 weeks minimum
Essential Medications Requiring Special Protocols:
Some life-sustaining medications cannot be safely discontinued, requiring alternative strategies such as medical supervision during use or indefinite postponement of psilocybin experiences.
Comprehensive Pre-Use Health Assessment
Required Medical Evaluations:
Complete physical examinations should include cardiovascular screening, liver and kidney function tests, blood pressure monitoring, and electrocardiogram assessment for users over 40 or with existing health conditions.
Mental Health Risk Assessment:
Qualified mental health professionals should evaluate personal and family psychiatric history, current symptoms, suicide risk factors, and psychological readiness for potentially intense experiences.
Complete Medication and Supplement Documentation:
Create detailed inventories including prescription medications, over-the-counter drugs, herbal supplements, vitamins, and recreational substances with specific dosages and usage patterns.
Environmental Safety and Support System Preparation
Medical Emergency Preparedness:
Establish clear protocols for accessing emergency medical care, including transportation plans, emergency contact information, and pre-written medical information cards detailing recent substance use and current medications.
Trained Companion Requirements:
Ensure experienced, sober companions understand interaction warning signs, basic first aid procedures, and when to seek professional medical help during the psilocybin experience.
Healthcare Provider Communication:
Develop relationships with medical professionals knowledgeable about psilocybin interactions who can provide guidance before, during, and after use when complications arise.
Long-Term Health Management and Ongoing Safety

Post-Experience Medication Management
Safe Medication Resumption:
Restart prescription medications according to healthcare provider guidance, typically beginning 24-48 hours after psilocybin effects completely resolve. Some medications may require gradual reintroduction to prevent rebound effects.
Monitoring Changed Medication Effectiveness:
Track how your regular medications perform after psilocybin use, as some individuals report lasting changes in medication sensitivity or effectiveness requiring dosage adjustments.
Delayed Interaction Recognition:
Monitor for subtle interaction effects that may emerge days or weeks after psilocybin use, particularly changes in mood, sleep patterns, or chronic condition management.
Ongoing Health Monitoring Requirements
Regular Laboratory Testing:
Schedule periodic blood work to monitor liver enzymes, kidney function, electrolyte levels, and other markers that may be affected by repeated psilocybin use combined with regular medications.
Cardiovascular Health Tracking:
Maintain regular blood pressure monitoring, especially for users with hypertension or heart conditions who combine psilocybin with cardiovascular medications.
Mental Health Check-ins:
Establish regular psychiatric follow-ups to assess medication effectiveness, mood stability, and any lasting psychological effects from psilocybin experiences.
Building Sustainable Safety Practices for Psilocybin Safety Beyond Psychotropics
Personal Interaction Tracking Systems:
Develop detailed records documenting medication combinations, dosages, timing, effects, and any complications to identify patterns and improve safety over time.
Healthcare Provider Relationships:
Cultivate ongoing relationships with medical professionals who understand both traditional pharmacology and emerging psychedelic therapies for comprehensive care coordination.
Long-term Planning Strategies:
Create sustainable approaches for integrating therapeutic psilocybin use with necessary medical treatments, considering evolving health needs and medication requirements.
Conclusion
Psilocybin Safety Beyond Psychotropics encompasses a complex web of biological interactions that extend far beyond the compound’s primary psychoactive effects. The intricate relationships between psilocybin and conventional medications create both opportunities and risks that require careful navigation with qualified medical supervision.
Understanding these interactions empowers individuals to make informed decisions about psilocybin use while maintaining their essential health treatments. The key to safe practice lies in thorough preparation, ongoing medical monitoring, and respect for the powerful ways psilocybin can influence your body’s processing of other therapeutic compounds.
As research continues expanding our knowledge of psilocybin’s therapeutic potential, maintaining focus on comprehensive safety practices ensures that individuals can explore these benefits while protecting their overall health and well-being.
Frequently Asked Questions
How long must I wait after stopping antidepressants before using psilocybin safely?
The required waiting period varies significantly based on your specific antidepressant type and individual metabolism. SSRIs typically require 2-4 weeks for safe clearance, while MAO inhibitors demand 6-8 weeks minimum. Tricyclic antidepressants generally need 2-3 weeks. Always consult with a qualified healthcare provider for personalized timing recommendations based on your specific medication and health profile.
Can I safely use psilocybin while taking blood pressure medications?
Blood pressure medications create varying interaction risks with psilocybin’s cardiovascular effects. Some combinations may be manageable under strict medical supervision, while others pose significant dangers. Beta-blockers, ACE inhibitors, and calcium channel blockers each present unique interaction profiles requiring individual medical assessment before considering psilocybin use.
Will my prescription medications work differently after psilocybin use?
Psilocybin can temporarily affect your body’s medication processing mechanisms, and some individuals report lasting changes in medication sensitivity or effectiveness. These changes may require dosage adjustments or alternative treatment approaches. Regular monitoring with your healthcare provider helps identify and manage any alterations in medication response patterns.
What emergency symptoms require immediate medical attention during psilocybin use with medications?
Seek immediate emergency care for chest pain, severe breathing difficulties, extreme confusion, rapid or irregular heartbeat, high fever above 101°F, severe muscle rigidity, or unresponsiveness. Have emergency contacts readily available and inform medical personnel about all substances and medications consumed, including exact dosages and timing.
Which over-the-counter medications should I avoid when using psilocybin?
Several common over-the-counter substances can interact dangerously with psilocybin, including St. John’s Wort, dextromethorphan (found in cough medicines), high-dose B-complex vitamins, and certain cold medications containing multiple active ingredients. Create a comprehensive list of all medications, supplements, and herbal products for thorough medical review before psilocybin use.
Psilocybin Safety Beyond Psychotropics | Psilocybin Safety Beyond Psychotropics | Psilocybin Safety Beyond Psychotropics | Psilocybin Safety Beyond Psychotropics | Psilocybin Safety Beyond Psychotropics Psilocybin | Psilocybin Safety Beyond Psychotropics | Psilocybin Safety Beyond Psychotropics | Psilocybin Safety Beyond Psychotropics | Psilocybin Safety Beyond Psychotropics | Psilocybin Safety Beyond Psychotropics | Psilocybin Safety Beyond Psychotropics | Psilocybin Safety Beyond Psychotropics | Psilocybin Safety Beyond Psychotropics | Psilocybin Safety Beyond Psychotropics

Microdosing Psychedelics
Microdosing Psychedelics: Unveiling Remarkable Health Benefits and Therapeutic Potential
The practice of microdosing psychedelics has emerged as one of the most fascinating developments in modern wellness and therapeutic research. Scientists and health practitioners worldwide now recognize that taking sub-perceptual doses of psychedelic substances offers unexpected health benefits that extend far beyond traditional mental health applications.
Understanding the Science Behind Microdosing Psychedelics

What Defines a Microdose and Its Mechanisms
Microdosing psychedelics involves consuming approximately 5-10% of a full psychoactive dose, typically ranging from 0.1-0.3 grams of dried psilocybin mushrooms or 6-25 micrograms of LSD. This practice activates specific neurobiological pathways without producing hallucinogenic effects.
The brain responds to these micro-amounts by stimulating serotonin receptors, particularly the 5-HT2A receptor, which triggers cascading neurochemical changes. These low doses create subtle but measurable alterations in neural activity patterns, promoting enhanced connectivity between brain regions while maintaining normal consciousness levels.
Unlike therapeutic doses used in clinical settings or recreational amounts that produce intense psychoactive experiences, microdoses work below the threshold of perception while still influencing brain chemistry and function.
Primary Substances in Microdosing Practices
Psilocybin Mushrooms
Psilocybin represents the most researched substance in microdosing psychedelics studies. Users typically consume 0.1-0.3 grams of dried mushrooms every three days, with effects lasting 6-8 hours. Current research demonstrates promising results for mood enhancement and cognitive improvement.
LSD Microdosing
LSD microdoses range from 6-25 micrograms, significantly lower than recreational doses. Research participants follow structured protocols showing improved focus and emotional regulation. Scientific findings indicate sustained benefits lasting several days post-dose.
Emerging Compounds
DMT and mescaline have entered microdosing research, though studies remain limited. These substances show potential for unique therapeutic applications, requiring further investigation to establish safety profiles and optimal dosing guidelines.
Established Protocols and Dosing Schedules
The Fadiman Protocol
Dr. James Fadiman developed the most widely adopted approach: dosing every three days with rest periods. This schedule prevents tolerance development while allowing cumulative benefits to emerge. Users take one dose, followed by two rest days, creating a sustainable long-term pattern.
Alternative Scheduling Methods
Some practitioners prefer five-day cycles or intuitive dosing based on individual responses. These variations accommodate personal schedules and sensitivity levels, though systematic research comparing different protocols remains limited.
Mental Health Improvements Through Microdosing Psychedelics

Depression and Anxiety Relief
Clinical studies reveal significant depression score reductions among microdosing psychedelics participants compared to control groups. Research demonstrates that regular microdosing activates neuroplasticity mechanisms, helping break persistent negative thought patterns associated with depressive episodes.
Anxiety reduction occurs through enhanced GABA system function and reduced amygdala hyperactivity. Participants report sustained mood improvements lasting weeks beyond active dosing periods, suggesting long-term neurochemical rebalancing rather than temporary symptom suppression.
Traditional antidepressant medications often produce side effects including sexual dysfunction, weight gain, and emotional blunting. Microdosing shows fewer adverse effects while providing comparable or superior mood enhancement in preliminary studies.
Enhanced Cognitive Function and Mental Clarity
Microdosing psychedelics produces measurable improvements in working memory, sustained attention, and executive function. Neuroimaging studies show increased activity in prefrontal cortex regions responsible for higher-order thinking and decision-making.
Problem-solving abilities demonstrate significant enhancement, with participants showing increased divergent thinking and creative solution generation. These cognitive benefits appear in both neurotypical individuals and those with attention-related disorders.
Processing speed and mental flexibility improve consistently across multiple studies, suggesting that microdosing enhances overall cognitive efficiency rather than targeting specific mental functions.
Emotional Regulation and Stress Management
Regular microdosing reduces emotional reactivity while preserving emotional depth and authenticity. Users report improved stress response patterns and enhanced resilience during challenging situations.
Interpersonal relationships benefit from increased empathy, emotional intelligence, and communication skills. These improvements stem from enhanced neural connectivity between emotional processing centers and rational decision-making regions.
Trauma processing capabilities improve as microdosing appears to reduce fear-based responses while maintaining access to emotional memories needed for therapeutic work.
Unexpected Physical Health Benefits
Cardiovascular System Improvements
Microdosing psychedelics produces measurable cardiovascular benefits including improved heart rate variability and blood pressure regulation. These effects result from enhanced autonomic nervous system balance and reduced chronic stress responses.
Inflammation markers linked to cardiovascular disease show significant reductions in regular microdosers. C-reactive protein, interleukin-6, and other inflammatory indicators decrease substantially during active microdosing periods.
Age-related cardiovascular decline may slow through microdosing’s protective effects on endothelial function and arterial flexibility, though long-term studies are needed to confirm these preliminary findings.
Immune System Function Enhancement
Immune response optimization occurs through microdosing psychedelics effects on inflammatory pathways and stress hormone regulation. Research shows improved immune cell function and reduced autoimmune symptom severity.
Cellular-level anti-inflammatory effects activate through serotonin receptor pathways that influence immune system signaling. These changes reduce systemic inflammation while preserving healthy immune responses to pathogens.
Chronic inflammatory conditions including arthritis, inflammatory bowel disease, and autoimmune disorders show improvement in preliminary case studies, warranting further investigation.
Sleep Quality and Energy Enhancement
Sleep architecture improvements include increased deep sleep phases and reduced sleep onset time. Microdosing psychedelics helps regulate circadian rhythms without producing sedative effects or next-day grogginess.
Daytime energy levels increase naturally without stimulant-like side effects or afternoon crashes. Users report sustained energy throughout the day while maintaining normal sleep patterns at night.
Natural sleep cycle restoration occurs as microdosing helps synchronize internal biological clocks with environmental light-dark cycles, particularly beneficial for individuals with disrupted circadian rhythms.
Neuroplasticity and Long-Term Brain Health

Neural Pathway Development
Microdosing psychedelics dramatically increases brain-derived neurotrophic factor (BDNF) production, promoting new neural connection formation. This neuroplasticity enhancement helps break rigid thought patterns and facilitates behavioral change.
Synaptic plasticity improvements create more flexible neural networks capable of adapting to new information and experiences. These changes support learning, memory formation, and cognitive flexibility throughout life.
Neural rewiring processes activated by microdosing help overcome entrenched mental habits and automatic response patterns, creating opportunities for personal growth and behavioral modification.
Neuroprotective Effects Against Aging
Research suggests microdosing psychedelics may protect against neurodegenerative diseases including Alzheimer’s and Parkinson’s disease. These protective effects result from enhanced cellular repair mechanisms and reduced neuroinflammation.
Cognitive function maintenance in aging populations shows promise through microdosing’s neuroplasticity-promoting effects. Older adults demonstrate improved memory, attention, and executive function during microdosing protocols.
Cellular repair mechanisms activated by psychedelic compounds include autophagy enhancement, mitochondrial function improvement, and oxidative stress reduction, all crucial for healthy brain aging.
Recovery and Rehabilitation Applications
Traumatic brain injury recovery accelerates through microdosing psychedelics effects on neurogenesis and neural repair processes. Patients show improved cognitive function and faster symptom resolution compared to standard treatments alone.
Stroke rehabilitation outcomes improve when microdosing supplements traditional therapy approaches. Enhanced neuroplasticity facilitates motor skill relearning and cognitive function recovery.
Addiction recovery programs incorporating microdosing show higher success rates and reduced relapse likelihood, as neuroplasticity enhancement supports breaking addictive behavior patterns.
Current Research Landscape and Clinical Evidence
Major Studies and Key Findings
Randomized controlled trials examining microdosing psychedelics have produced encouraging preliminary results. The largest study to date followed 953 participants over six months, demonstrating significant improvements in mood, anxiety, and cognitive function compared to placebo groups.
Longitudinal research tracking microdosing effects over extended periods reveals sustained benefits lasting months after treatment completion. These findings suggest that microdosing creates lasting neurobiological changes rather than temporary symptom relief.
Meta-analyses combining multiple research efforts show consistent positive effects across different populations and dosing protocols, strengthening confidence in microdosing’s therapeutic potential.
Research Limitations and Gaps
Current studies face sample size constraints and demographic limitations, with most participants being young, educated, and predominantly white. Broader demographic representation is needed to establish universal applicability.
Placebo effect considerations complicate research design since participants may recognize subtle psychoactive effects. Researchers develop innovative blinding methods to address these methodological challenges.
Long-term safety and efficacy studies remain limited, requiring multi-year investigations to fully understand microdosing psychedelics risks and benefits over extended periods.
Future Research Directions
Multiple clinical trials currently recruit participants to investigate specific therapeutic applications including treatment-resistant depression, ADHD, and chronic pain conditions. These studies employ rigorous methodologies to establish definitive efficacy evidence.
Research questions continue expanding to explore optimal dosing schedules, individual variation factors, and combination therapies integrating microdosing with traditional treatments.
Regulatory approval timelines suggest that medical microdosing applications may become available within 5-10 years as research evidence accumulates and regulatory frameworks evolve.
Safety Considerations and Risk Assessment
Known Side Effects and Contraindications
Microdosing psychedelics produces minimal side effects in most users, with reported adverse effects including mild anxiety, appetite changes, and occasional sleep disturbances. These effects typically resolve quickly and rarely require intervention.
Drug interactions remain poorly understood, requiring caution when combining microdosing with psychiatric medications, particularly SSRIs and MAOIs. Medical supervision is essential for individuals taking prescription medications.
Psychological risks exist for vulnerable populations including individuals with psychotic disorders, bipolar disorder, or severe anxiety conditions. Screening protocols help identify unsuitable candidates.
Legal Status and Regulatory Framework
Most psychedelic substances remain federally illegal despite growing research evidence and changing public attitudes. However, numerous jurisdictions have decriminalized or created legal research frameworks.
Regional variations in enforcement and medical access create complex legal landscapes. Some areas permit supervised therapeutic use while others maintain strict prohibition policies.
Regulatory pathways for future legalization focus on medical applications first, with recreational access likely following successful therapeutic integration.
Best Practices for Safe Implementation
Medical supervision provides optimal safety for microdosing psychedelics implementation. Healthcare providers can monitor progress, manage interactions, and address adverse effects promptly.
Substance purity and quality control present significant challenges in unregulated markets. Third-party testing and trusted sources become crucial for safety and consistency.
Integration practices including therapy, meditation, and journaling enhance benefits while providing support systems for processing experiences and insights.
Conclusion
Microdosing psychedelics represents a revolutionary approach to health optimization with benefits extending far beyond traditional therapeutic applications. Current research demonstrates remarkable potential for mental health improvement, cognitive enhancement, and unexpected physical health benefits including cardiovascular protection and immune system optimization.
While research continues evolving, preliminary evidence strongly supports microdosing’s therapeutic potential with minimal side effects compared to traditional medications. The practice shows promise for addressing multiple health conditions simultaneously through neuroplasticity enhancement and systemic inflammation reduction.
Safety considerations, legal constraints, and the need for comprehensive long-term studies remain important factors requiring attention before widespread adoption. However, as regulatory frameworks evolve and research evidence accumulates, microdosing psychedelics may become an essential tool in personalized medicine and preventive healthcare strategies.
The future of microdosing appears bright as scientific understanding deepens and societal acceptance grows, potentially transforming approaches to mental health treatment, cognitive optimization, and overall wellness enhancement.
Frequently Asked Questions
Q: How long do microdosing effects typically last?
A: Individual microdoses produce subtle effects lasting 6-8 hours, while cumulative benefits may persist for weeks or months after consistent use, though comprehensive long-term research continues developing.
Q: Can microdosing replace traditional depression or anxiety medications?
A: Microdosing psychedelics should never replace prescribed medications without medical supervision, as research remains ongoing and individual responses vary significantly across different populations.
Q: What is the legal status of microdosing in most countries?
A: Most psychedelic substances remain illegal internationally, though numerous regions have decriminalized use or established legal research programs. Legal status varies considerably by location and specific substance.
Q: How can someone determine if microdosing is producing benefits?
A: Effects typically include improved mood, enhanced creativity, better focus, or increased emotional regulation. Maintaining a detailed daily journal helps track subtle changes and progress over time.
Q: What are the most frequently reported side effects?
A: Common side effects include mild anxiety, slight appetite changes, occasional sleep disturbances, and rare instances of increased emotional sensitivity, though most users report minimal adverse effects.
Q: What dosing frequency provides optimal benefits?
A: Most research supports dosing every 2-3 days to prevent tolerance development, though optimal frequency varies individually and requires additional study to establish definitive protocols for different populations.
Psilocybin vs Psychedelics: Your USA Guide
Psilocybin vs Psychedelics: Your USA Guide

If you’ve been hearing a lot about magic mushrooms lately and wondering what’s actually going on with all of it — you’re not alone. Psilocybin vs psychedelics is one of the most searched topics right now, and for good reason. The science is moving fast, the laws are shifting state by state, and a lot of people are trying to separate fact from hype.
This guide is for anyone curious about where psilocybin fits into the broader world of psychedelics — whether you’re a patient exploring mental health options, a researcher tracking the field, or just someone who wants to understand what’s actually happening in the USA right now.
Here’s what we’ll cover:
-
What psilocybin actually is and how it differs from other psychedelics
-
Where it stands legally across the United States
-
What the research really shows — including the breakthroughs coming out of Johns Hopkins and what they mean for everyday people
No fluff, no scare tactics. Just a clear breakdown of what we know so far.
Understanding Psilocybin and Its Place Among Psychedelics
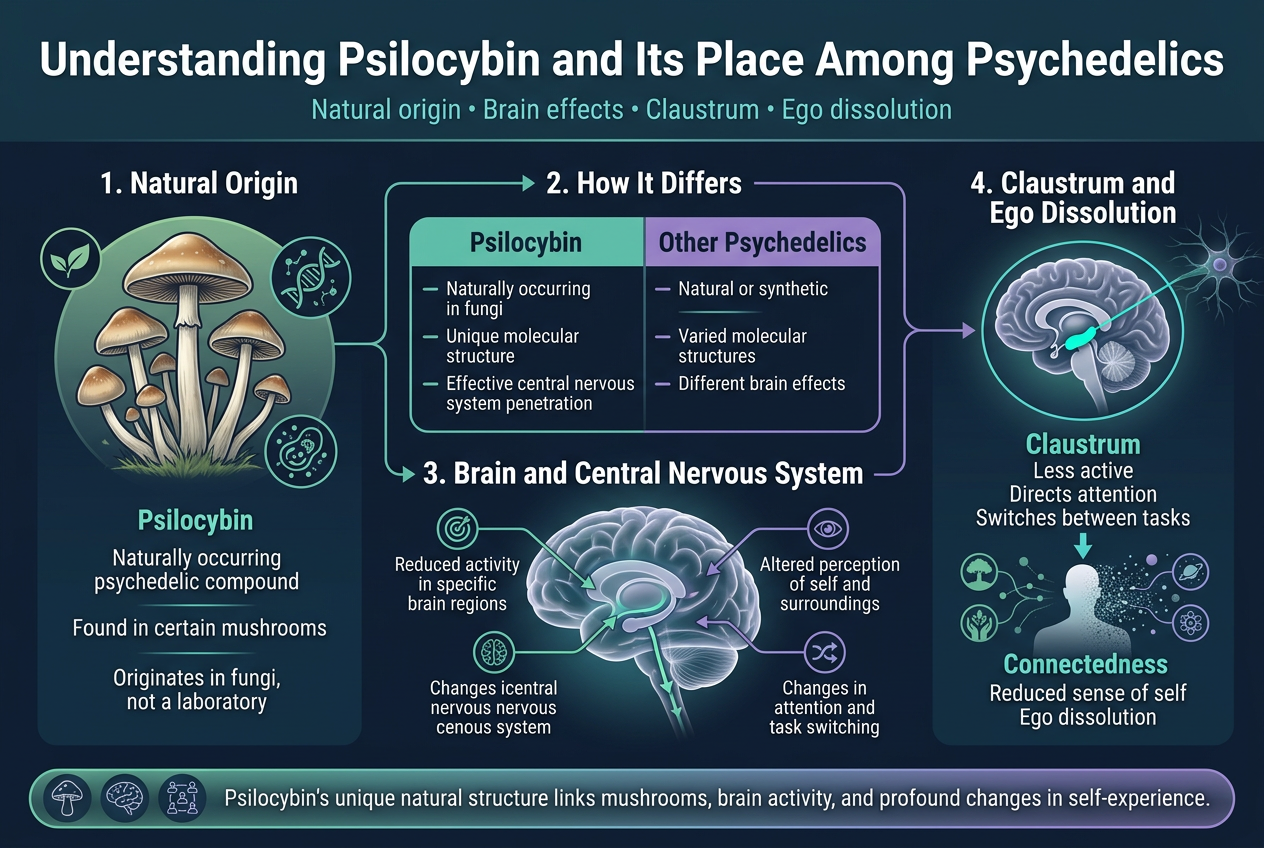
What Is Psilocybin and Where Does It Come From
Psilocybin is a naturally occurring psychedelic compound found in what are commonly known as “magic mushrooms.” Unlike synthetic substances manufactured in laboratories, psilocybin has its origins in nature, embedded within the biological makeup of certain fungal species. This natural origin is a key part of what distinguishes psilocybin within the broader landscape of psychedelic substances and has contributed to its long history of use across various cultures.
The fact that psilocybin is naturally occurring does not diminish its potency or complexity. Its molecular structure is sophisticated enough to interact profoundly with human biology, particularly the central nervous system, making it one of the most pharmacologically significant compounds found in nature.
How Psilocybin Differs From Other Psychedelic Substances
Within the broad category of psychedelics, psilocybin occupies a distinctive position. While many psychedelic substances exist — both natural and synthetic — psilocybin stands apart due to several characteristics:
-
Natural origin: Psilocybin is derived directly from fungi, specifically certain species of mushrooms, rather than being synthesized chemically.
-
Molecular structure: The molecular structure of psilocybin is specifically designed, in a biological sense, to penetrate the central nervous system effectively.
-
Mechanism of action: Psilocybin targets specific regions and systems in the brain, producing effects that are characteristic yet distinct from those of other psychedelic compounds.
| Feature | Psilocybin | Other Psychedelics (General) |
|---|---|---|
| Origin | Naturally occurring in fungi | Can be natural or synthetic |
| CNS Penetration | Yes, via unique molecular structure | Varies by compound |
| Primary Brain Effects | Claustrum activity reduction, ego dissolution | Varies widely |
These distinctions matter considerably when discussing the Psilocybin vs Psychedelics conversation in the context of research, therapy, and legal status across the USA.
How Psilocybin Affects the Brain and Central Nervous System
Now that we have covered where psilocybin comes from and how it compares to other psychedelics, it is important to understand precisely how it operates within the human body — particularly the brain.
The molecular structure of psilocybin is a critical factor in its psychoactive effects. This structure allows psilocybin to effectively penetrate the central nervous system, gaining access to brain regions and neural pathways that govern perception, cognition, mood, and a sense of self. Once it crosses into the central nervous system, psilocybin begins to exert its influence on specific brain structures, leading to the vivid and often profound experiences that users report.
Key effects on the brain and central nervous system include:
-
Reduced activity in specific brain regions, most notably the claustrum
-
Altered perception of self and surroundings, tied directly to these neural changes
-
Changes in how the brain switches between tasks and allocates attention
These neurological effects are not random. They are the direct result of how psilocybin’s molecular structure interacts with the central nervous system, producing consistent patterns of experience that researchers have been able to study and document.
The Role of the Claustrum and Ego Dissolution in Psilocybin Experiences
With this in mind, next, we will explore one of the most fascinating neurological findings related to psilocybin: the role of the claustrum.
Psilocybin use has been shown to make the claustrum in the brain less active. The claustrum is a region of the brain believed to be responsible for two critical cognitive functions:
-
Setting and directing attention
-
Switching between tasks
When psilocybin reduces activity in the claustrum, these functions are significantly altered. The brain’s usual mechanisms for filtering attention and managing cognitive transitions become less dominant, which opens the door to a cascade of characteristic psychedelic effects.
This reduced claustrum activity is directly linked to some of the most commonly reported — and therapeutically relevant — effects of psilocybin, including:
-
Feelings of being deeply connected to everything around you, including other people, nature, and the universe at large
-
A reduced sense of self or ego, often described in clinical and research settings as ego dissolution
Ego dissolution, in particular, is a defining feature of psilocybin experiences that sets it apart within the psychedelic category. It refers to the temporary diminishment or complete dissolution of one’s ordinary sense of individual identity — a psychological state that researchers believe may be central to psilocybin’s potential therapeutic benefits.
Previously, understanding how psychedelics worked relied heavily on subjective user reports. The identification of the claustrum’s role provides a concrete, neurological basis for these experiences, bridging the gap between reported phenomenology and measurable brain activity. This scientific grounding is one reason psilocybin has attracted such serious academic and medical attention in recent years.
The Legal Status of Psilocybin in the USA
Current Federal Classification as a Schedule I Drug
At the federal level, psilocybin remains classified as a Schedule I controlled substance under the Controlled Substances Act. This classification carries significant weight, as it places psilocybin in the same legal category as substances deemed to have:
-
No currently accepted medical use in the United States
-
A high potential for abuse
-
A lack of accepted safety for use under medical supervision
This federal standing creates substantial barriers for researchers, clinicians, and patients alike. Scientists seeking to study psilocybin must navigate layers of regulatory hurdles simply to obtain the substance for controlled research settings. For patients, the Schedule I designation means there is no legal pathway to access psilocybin through a licensed healthcare provider at the federal level — regardless of the growing body of evidence suggesting its therapeutic promise.
Understanding this classification is foundational to any honest discussion about psilocybin vs psychedelics in the broader USA guide context, because it shapes everything from research timelines to clinical access and provider liability.
Johns Hopkins Recommendation to Reclassify Psilocybin to Schedule IV
Now that we have covered the current legal landscape, it is important to highlight a pivotal recommendation that could reshape psilocybin’s future. Researchers at Johns Hopkins University, one of the most respected medical institutions in the world, have made a formal and evidence-backed recommendation: if psilocybin successfully clears Phase III clinical trials, it should be reclassified from a Schedule I drug to a Schedule IV controlled substance.
To understand the significance of this, consider how Schedule IV substances are treated under U.S. law:
| Classification | Examples | Medical Use Recognized? | Abuse Potential |
|---|---|---|---|
| Schedule I | Psilocybin (current) | No | Considered high |
| Schedule IV | Prescription sleep aids | Yes | Considered low-to-moderate |
A Schedule IV designation is typically reserved for medications that have accepted medical applications and a relatively lower potential for abuse compared to substances in higher schedules. The Johns Hopkins recommendation places psilocybin in the same category as certain prescription sleep aids, though notably with the suggestion that it be subject to tighter controls than those currently applied to standard Schedule IV drugs.
This distinction is critical. The Hopkins team is not advocating for open or recreational access. Rather, they are proposing a framework in which psilocybin could be prescribed and monitored within a structured, medically supervised environment — contingent on the drug first demonstrating consistent efficacy and safety through the rigors of Phase III trial protocols.
What Reclassification Could Mean for Patients and Providers
With this in mind, the implications of moving psilocybin from Schedule I to Schedule IV would be far-reaching, touching every corner of the healthcare ecosystem.
For Patients:
-
A reclassification would open the door to legal, medically supervised access to psilocybin-based treatments
-
Patients dealing with conditions where current therapies fall short could have a new, legitimate treatment option available through licensed providers
-
The pathway through a regulated medical system would offer greater safety, consistency, and oversight compared to unregulated use
For Providers and Clinicians:
-
Healthcare professionals could legally prescribe and administer psilocybin within appropriate clinical settings
-
Medical institutions could expand research programs without the current burden of Schedule I regulatory restrictions
-
The tighter controls proposed alongside the Schedule IV designation suggest that providers would still operate under strict protocols, ensuring that psilocybin is used responsibly and only where medically appropriate
For the Research Community:
-
Reclassification would significantly lower the regulatory barriers that currently slow clinical research
-
Phase III trials — the very milestone that would trigger reclassification under the Hopkins framework — would become more feasible as the legal environment evolves
-
A more permissive research classification could accelerate the development of evidence-based psilocybin therapies
Previously, the idea of reclassifying a psychedelic compound within the U.S. federal system would have seemed remote. Today, with institutions of the caliber of Johns Hopkins lending their credibility to the conversation, the question of reclassification has shifted from theoretical to genuinely actionable — pending the clinical evidence that Phase III trials are designed to provide.
Breakthrough Research Driving the Psychedelic Renaissance

Johns Hopkins Center for Psychedelic and Consciousness Research Overview
When examining the forces behind the modern psychedelic renaissance, one institution stands head and shoulders above the rest: the Johns Hopkins Center for Psychedelic and Consciousness Research. This pioneering center holds the distinction of being both the first such research center in the United States and the largest psychedelic research center in the world — a remarkable combination that has positioned it at the absolute forefront of this rapidly evolving field.
The center operates with a total backing of $55 million in funding, a figure that reflects the extraordinary level of confidence researchers, philanthropists, and the broader scientific community have placed in this work. Its foundation was laid with $17 million in private donations, demonstrating that long before federal agencies were ready to invest, private individuals and organizations recognized the immense potential of psilocybin-assisted research. This grassroots financial momentum was essential in keeping the science alive during decades when government support was virtually nonexistent.
Key areas the center investigates include:
-
Innovative psilocybin treatments for a wide range of conditions
-
Consciousness research that examines how psychedelics alter human perception and awareness
-
The safety and therapeutic potential of classic psychedelics in controlled clinical settings
The center’s work has not only produced groundbreaking scientific findings but has also helped legitimize psychedelic research on a global scale, encouraging institutions worldwide to launch their own programs.
Key Milestones From 2000 to 2025 in Psilocybin Research
With this in mind, it is worth tracing the timeline of critical developments that have brought psilocybin research from the fringes of science to the center of mainstream medicine. The journey has been long, deliberate, and filled with hard-won victories at every stage.
Here is a structured overview of the key milestones:
| Year | Milestone |
|---|---|
| 2000 | Johns Hopkins receives regulatory approval to resume psychedelics research in healthy volunteers — a pivotal turning point after decades of restrictions |
| 2006 | Publication of a landmark study on psilocybin’s safety and its enduring positive effects on mystical-type experiences, widely credited with sparking a global revival of psychedelic research |
| 2021 | Johns Hopkins Medicine is awarded the first federal NIH grant in over 50 years to directly study the therapeutic effects of a classic psychedelic |
Each of these milestones represents far more than a bureaucratic checkpoint. They reflect a gradual but unmistakable shift in how governments, scientists, and the public perceive the therapeutic value of psilocybin and other psychedelics within the broader Psilocybin vs Psychedelics conversation shaping the USA today.
The First Federal NIH Grant for Psychedelic Research in 50 Years
Previously, federal funding for psychedelic research had been entirely absent for more than half a century — a gap that speaks volumes about how politically and socially contentious these substances had become following their prohibition. That changed in a significant way in 2021, when Johns Hopkins Medicine was awarded the first federal NIH grant in over 50 years to directly investigate the therapeutic effects of a classic psychedelic.
The focus of this landmark grant was psilocybin as a treatment for tobacco addiction — a specific, clinically meaningful application that underscores the seriousness with which the scientific community now views this research. Tobacco addiction is notoriously difficult to treat with conventional methods, making psilocybin’s potential in this area both exciting and practically significant.
Why does this federal grant matter so profoundly? Consider the following:
-
Validation: Federal NIH funding represents an institutional endorsement of the science, signaling that psilocybin research has met rigorous standards of credibility and promise.
-
Scale: NIH grants open the door to larger, more comprehensive clinical trials that private funding alone cannot always support.
-
Precedent: Once the federal government funds one psychedelic study, it becomes far easier to fund subsequent ones, creating a positive feedback loop for the field.
-
Legitimacy: For researchers, clinicians, and patients alike, federal backing removes much of the stigma that has historically surrounded psychedelic medicine.
This single grant, while representing just one study, carries enormous symbolic and practical weight for the entire trajectory of psychedelic medicine in the USA.
Landmark 2006 Study That Sparked Global Psychedelic Research Revival
Now that we have covered the institutional and funding milestones, it is essential to examine the specific scientific work that catalyzed so much of what followed. The 2006 publication from Johns Hopkins on psilocybin’s safety and its enduring positive effects on mystical-type experiences is widely regarded as one of the most consequential studies in the modern history of psychedelic science.
What made this study so remarkable was not just its findings, but its timing and credibility. After decades during which psychedelic research had been largely shut down and socially stigmatized, a rigorous, peer-reviewed study from one of the world’s most respected medical institutions delivered a clear and evidence-based message: psilocybin, when administered under controlled conditions, is safe and produces lasting positive psychological effects.
The key findings that gave this study its landmark status included:
-
Safety: The study provided compelling evidence that psilocybin does not carry the dangers that had been widely assumed in popular and political discourse.
-
Mystical-type experiences: Participants reported profound, meaningful experiences that were rated among the most significant of their lives — and these effects endured over time, not just in the immediate aftermath of the experience.
-
Rigorous methodology: The careful, controlled design of the study gave it the scientific credibility needed to be taken seriously by researchers, clinicians, and regulators worldwide.
The ripple effect of this publication cannot be overstated. It effectively gave researchers around the globe the scientific and institutional cover they needed to pursue their own psychedelic studies. Universities, medical centers, and research institutes in countries across the world began launching programs in the years that followed, creating the global psychedelic research community that exists today. In many ways, this single study was the spark that lit the fire of what is now commonly called the psychedelic renaissance.
Proven and Potential Therapeutic Benefits of Psilocybin
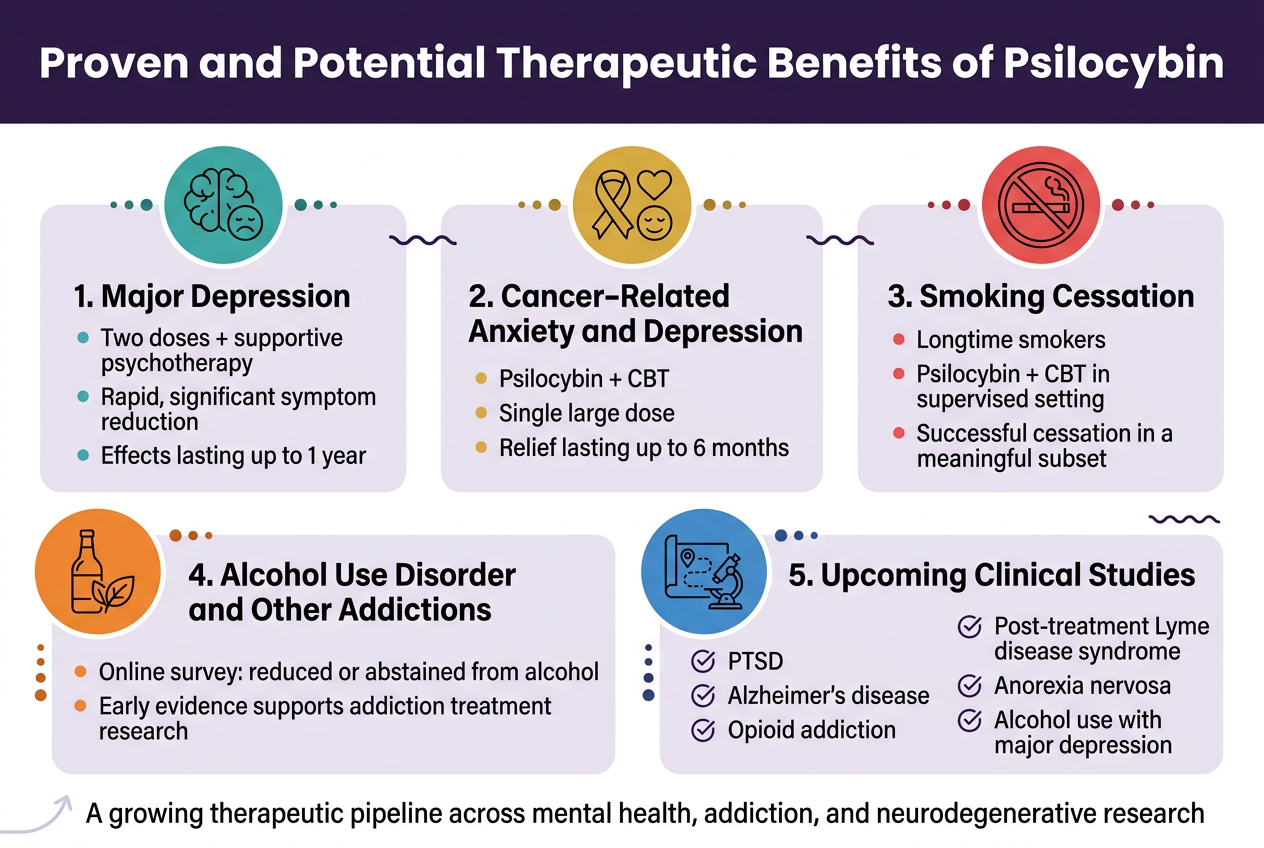
A. Psilocybin as a Treatment for Major Depression
Among the most compelling findings in the psychedelic renaissance is psilocybin’s potential to address one of the most widespread mental health conditions in the United States: major depressive disorder. Clinical research has demonstrated that just two doses of psilocybin, when combined with supportive psychotherapy, produced rapid and significant reductions in depressive symptoms in adults diagnosed with major depression. What makes this particularly remarkable is the durability of the results — for some patients, these therapeutic effects persisted for up to a full year following treatment.
This stands in stark contrast to conventional antidepressants, which typically require daily administration and can take weeks to produce noticeable effects. The depth and longevity of psilocybin’s impact on depression signals a fundamentally different mechanism of healing, one that is generating enormous excitement within both the psychiatric and research communities.
B. Reducing Anxiety and Depression in Cancer Patients
With this in mind, next, we’ll see how psilocybin has shown equally profound results in a deeply vulnerable population: individuals facing life-threatening cancer diagnoses. The psychological burden of a cancer diagnosis — including existential dread, anxiety, and depression — is well-documented and notoriously difficult to treat.
Research has shown that:
-
Psilocybin combined with cognitive behavioral therapy (CBT) can help reduce anxiety in cancer patients.
-
A single large dose of psilocybin offered considerable relief from cancer-related anxiety and depression for a substantial majority of patients studied.
-
Critically, this relief was not fleeting — effects lasted for up to six months following a single administration.
This ability to deliver sustained psychological relief from just one therapeutic session has enormous implications for palliative care and end-of-life mental health support. For patients who may not have the time, energy, or access to ongoing psychiatric treatment, a single psilocybin-assisted session could offer something that conventional medicine has long struggled to provide: lasting peace of mind.
C. Supporting Smoking Cessation Through Psilocybin-Assisted Therapy
Previously, smoking cessation has proven to be one of the most stubbornly resistant behavioral challenges in medicine. Nicotine addiction involves deep psychological and neurological pathways that most conventional treatments only partially address. Psilocybin-assisted therapy, however, has demonstrated a potentially transformative role in helping people break free from long-term tobacco use.
In a controlled clinical setting, psilocybin facilitated smoking cessation for a small number of longtime smokers who had previously failed multiple quit attempts. Importantly, the treatment was delivered alongside cognitive behavioral therapy (CBT), suggesting that the combination of a mystical or introspective psilocybin experience with structured psychological support may be key to achieving lasting behavioral change.
Key highlights from this area of research include:
| Factor | Detail |
|---|---|
| Target Population | Longtime smokers with previous failed cessation attempts |
| Setting | Controlled, supervised clinical environment |
| Therapeutic Pairing | Cognitive behavioral therapy (CBT) |
| Outcome | Successful smoking cessation in a meaningful subset of participants |
While the sample sizes in initial studies remain small, the results provide a compelling foundation for larger, more definitive trials.
D. Addressing Alcohol Use Disorder and Other Substance Addictions
Now that we have covered smoking cessation, it’s worth examining another critical domain where psilocybin and psychedelics more broadly are showing early promise: Alcohol Use Disorder (AUD) and substance addiction.
An online survey found that psychedelic use — including psilocybin specifically — may help individuals with Alcohol Use Disorder reduce or abstain from alcohol consumption. While survey-based evidence occupies a lower tier of scientific rigor compared to controlled clinical trials, it provides meaningful directional insight and helps justify the funding and design of more rigorous studies.
The implications for addiction medicine are considerable. Alcohol Use Disorder is a chronic, relapsing condition associated with severe health, social, and economic consequences. If psilocybin can interrupt the psychological patterns underpinning alcohol dependence — as early data suggests — it could represent a genuinely novel therapeutic pathway for a condition that has resisted many conventional approaches.
E. Upcoming Studies on PTSD, Alzheimer’s, Opioid Addiction, and Anorexia
The existing body of evidence is compelling, but researchers are only beginning to map the full therapeutic landscape of psilocybin. A robust pipeline of upcoming clinical studies is set to explore psilocybin’s effectiveness across a wide range of additional conditions, including:
-
Post-Traumatic Stress Disorder (PTSD)
-
Alzheimer’s disease
-
Opioid addiction
-
Post-treatment Lyme disease syndrome
-
Anorexia nervosa
-
Alcohol use in individuals also diagnosed with major depression
Each of these conditions represents a significant unmet medical need — areas where current treatments are either insufficient, inaccessible, or accompanied by serious drawbacks. The inclusion of Alzheimer’s disease in this research pipeline is particularly noteworthy, as it suggests scientists are exploring psilocybin’s potential neuroplasticity-related mechanisms beyond purely psychiatric applications.
Similarly, research into anorexia nervosa — a condition with one of the highest mortality rates among psychiatric disorders — highlights how broadly researchers believe psilocybin’s therapeutic reach may extend. And with the opioid crisis continuing to devastate communities across the United States, any effective adjunct to addiction treatment carries enormous public health relevance.
The breadth of these upcoming studies underscores a growing scientific consensus: psilocybin’s therapeutic potential is not limited to a single condition or mechanism, but may reflect a fundamental capacity to facilitate deep psychological and neurological healing across multiple domains of human suffering.
Risks, Side Effects, and Safety Considerations
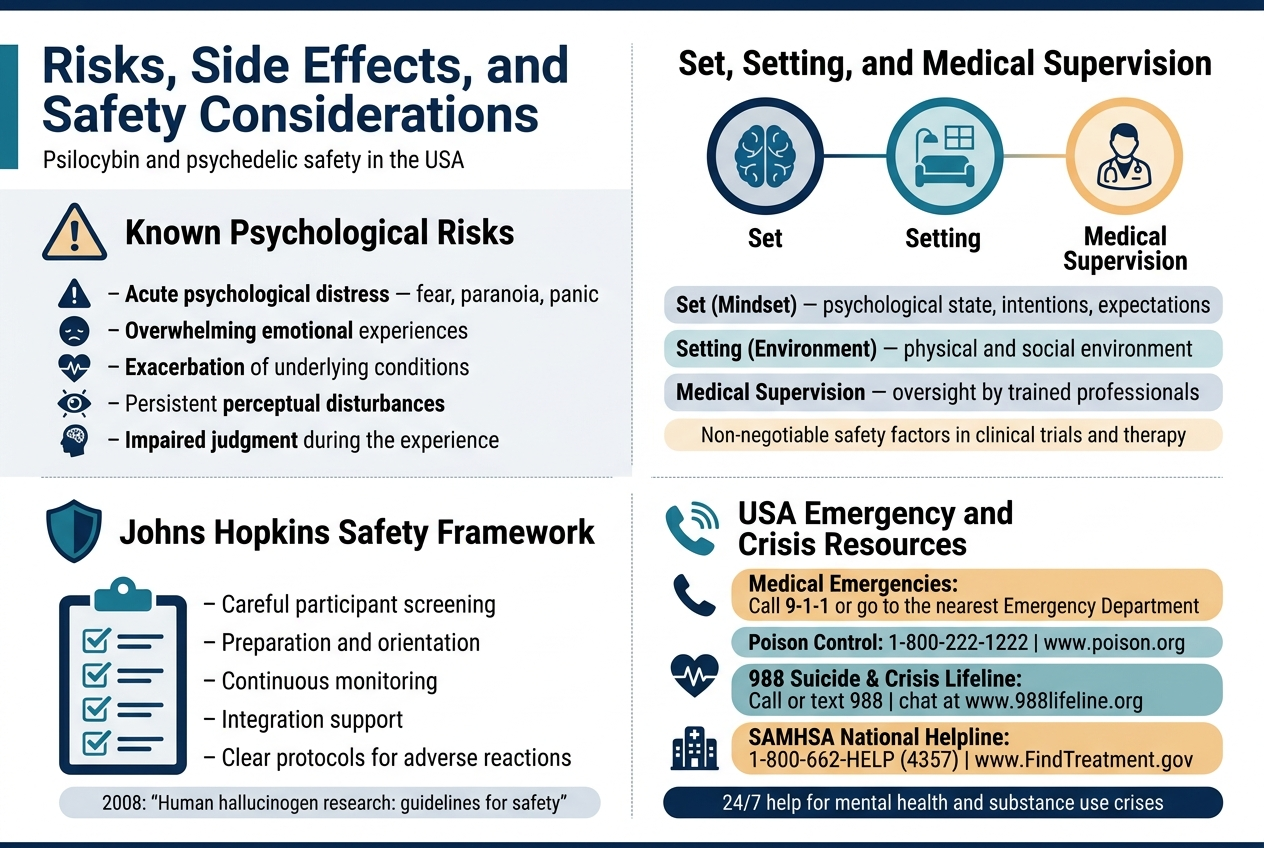
Known Psychological Risks and Potential Harms of Psychedelics
As psychedelics like psilocybin become increasingly visible in mainstream conversations around mental health and medicine, it is critically important to acknowledge that they are not without risk. Even as clinical research continues to highlight their therapeutic promise, a responsible and balanced understanding demands equal attention to their potential harms.
Known psychological risks associated with psilocybin and other psychedelics include:
-
Acute psychological distress – Users may experience intense fear, paranoia, or panic during a session, commonly referred to as a “bad trip.”
-
Overwhelming emotional experiences – The depth of introspective content can be destabilizing for individuals without proper preparation or support.
-
Exacerbation of underlying conditions – People with a personal or family history of psychosis or certain psychiatric disorders may face heightened vulnerability.
-
Persistent perceptual disturbances – Though rare, some individuals report lasting changes in perception following psychedelic use.
-
Impaired judgment during the experience – Decision-making can be significantly compromised while under the influence, posing situational safety risks.
These cautions are not reasons to dismiss the field, but they are essential considerations for anyone navigating the evolving landscape of psilocybin vs psychedelics in the USA.
Why Set, Setting, and Medical Supervision Matter
With this in mind, the context in which psilocybin is administered plays a decisive role in determining whether an experience is safe and potentially beneficial or distressing and harmful. Research has consistently demonstrated that psilocybin can be administered safely when it is facilitated by a qualified medical team, conducted over guided sessions, and carried out within regulated, controlled spaces.
The concept of “set and setting” refers to:
| Factor | What It Means | Why It Matters |
|---|---|---|
| Set (Mindset) | The psychological state, intentions, and expectations of the individual before the session | Shapes how the experience is interpreted and processed |
| Setting (Environment) | The physical and social environment in which the session takes place | Provides a sense of safety, comfort, and containment |
| Medical Supervision | Oversight by trained professionals throughout the session | Enables real-time support, crisis management, and clinical monitoring |
Without these protective factors in place, the probability of a distressing or harmful experience increases substantially. This is precisely why clinical trials and therapeutic programs treat set and setting as non-negotiable elements of the psilocybin protocol — not optional enhancements, but foundational safety mechanisms.
Safety Guidelines Established by Johns Hopkins Researchers
Previously, I’ve outlined the potential risks and the importance of structured contexts. Now, it is worth highlighting that the field has not been left without formal guidance. A landmark contribution to psychedelic safety came with the 2008 publication by Johns Hopkins researchers titled “Human hallucinogen research: guidelines for safety.”
This publication established a rigorous framework for conducting human hallucinogen research responsibly, and its guidelines have since been widely adopted by other researchers and institutions working in this space. The fact that these standards have achieved broad acceptance across the field speaks to both their comprehensiveness and the scientific community’s commitment to prioritizing participant welfare.
Key principles embedded in such safety frameworks typically address:
-
Careful participant screening to exclude individuals at elevated psychological risk
-
Preparation and orientation before the session to set informed expectations
-
Continuous monitoring by trained personnel throughout the session
-
Integration support following the experience to help participants process what arose
-
Clear protocols for managing adverse reactions or psychological crises
These guidelines represent the gold standard against which responsible psilocybin-assisted therapy should be measured, serving as an essential reference point for clinicians, researchers, and policymakers alike.
Emergency and Crisis Resources for USA Residents
With safety considerations fully in view, it is equally important that USA residents know exactly where to turn if an emergency or crisis arises — whether connected to psychedelic use or broader mental health and substance use concerns.
For Medical Emergencies:
-
Call 9-1-1 or go directly to your nearest Emergency Department
-
Poison Control: Call 1-800-222-1222 or visit www.poison.org for immediate guidance on substance-related concerns
For Substance Use or Mental Health Crises:
-
988 Suicide & Crisis Lifeline: Call or text 988, or chat online at www.988lifeline.org
-
This resource is available 24/7 for anyone experiencing a mental health or substance use crisis
For Treatment Referrals:
-
SAMHSA National Helpline: Call 1-800-662-HELP (4357) or visit www.FindTreatment.gov
-
SAMHSA provides free, confidential referrals to substance use and mental health treatment programs across the country
These resources are not just safety nets — they are lifelines. Anyone exploring the world of psilocybin or psychedelics in the USA should have these contact points readily accessible, both for themselves and for those around them.
What the Future Holds for Psychedelic Medicine in the USA

Expanding Research Into Wellness and Human Thriving
With a clearer picture of psilocybin’s therapeutic promise now established, researchers at institutions like Johns Hopkins are setting their sights even further. Rather than limiting the scope of study to clinical populations suffering from specific disorders, Johns Hopkins researchers are actively working to expand their investigations to include healthy volunteers. The goal is ambitious: to explore how psilocybin and related psychedelics might open entirely new pathways to support human thriving — not just the alleviation of illness, but the enhancement of well-being, meaning, and psychological flourishing.
This shift in research direction is backed by substantial resources. Johns Hopkins has secured $55 million in funding to drive this next phase of psychedelic science forward. This level of investment signals growing institutional confidence that psychedelic medicine is no longer a fringe pursuit — it is a serious, well-resourced scientific frontier.
Key areas this expanding research aims to address include:
-
Psychological well-being in non-clinical populations
-
Meaning-making and life satisfaction as measurable outcomes
-
Cognitive and emotional resilience as potential benefits for healthy individuals
-
New models of mental flourishing that go beyond the traditional disease-treatment framework
This pivot from treating illness to fostering thriving represents a genuinely exciting evolution in the field — one that could redefine what psychedelic medicine ultimately means for society at large.
New Educational Resources and Clinician Training on Psychedelic Medicine
Now that we have covered the expanding scope of research, it is equally important to recognize that scientific advances only translate into real-world impact when clinicians and the public are properly educated. Recognizing this gap, Johns Hopkins researchers have taken meaningful steps to build accessible, high-quality educational infrastructure around psychedelics.
By 2025, Johns Hopkins researchers developed a comprehensive online course on psychedelics designed to serve a broad audience — from curious individuals to practicing clinicians. This course covers a wide range of essential topics, including:
| Course Module | Key Focus Areas |
|---|---|
| History of Psychedelics | Cultural, scientific, and legal history |
| Clinical Trials | Methodology, outcomes, and ongoing studies |
| Neuroscience | How psychedelics interact with the brain |
| Risks and Safety | Known adverse effects and harm reduction |
| Bioethical Issues | Informed consent, equity, and access |
| The Future of Psychedelics | Emerging therapies and research directions |
Beyond the online course, the Johns Hopkins Psychiatry Guide was relaunched with new, dedicated modules on psychedelic medicine. This updated resource also includes streamlined pharmaceutical information, making it a practical, clinician-facing tool. These developments reflect a broader understanding that clinician training is not a secondary concern — it is a foundational requirement for the safe and effective integration of psychedelic therapies into mainstream healthcare settings.
The creation of structured educational resources marks a critical transition point: psychedelic medicine is moving from laboratory curiosity to institutionally supported clinical discipline.
The Path Toward FDA Approval and Mainstream Therapeutic Use
Previously, I’ve outlined how research is expanding and how clinicians are being equipped with the knowledge they need. With this in mind, it becomes clear that the trajectory of psychedelic medicine in the USA is pointing steadily toward broader legitimacy and mainstream therapeutic application.
The groundwork being laid through rigorous clinical research, substantial funding commitments, and robust clinician education is building the foundation that FDA approval ultimately requires. While the reference data does not yet confirm a specific FDA approval milestone for psilocybin, the cumulative weight of the developments discussed throughout this guide — the research expansion, the $55 million investment, the educational infrastructure at major institutions — paints a picture of a field moving deliberately and confidently toward that threshold.
Several factors are converging to accelerate this path:
-
Institutional credibility: Major research universities like Johns Hopkins are lending scientific authority to the field
-
Financial investment: $55 million in dedicated funding demonstrates long-term commitment to clinical development
-
Clinician readiness: Online courses and updated psychiatric guides are preparing the healthcare workforce in advance of broader therapeutic availability
-
Public and academic education: Courses covering history, neuroscience, ethics, and future applications are cultivating an informed base of practitioners and advocates
Together, these elements suggest that psychedelic medicine — and psilocybin in particular — is not merely a promising outlier in the Psilocybin vs Psychedelics: Your USA Guide conversation. It is rapidly becoming a central pillar of next-generation psychiatric care, moving from breakthrough research designation toward a future where evidence-based psychedelic therapy may be a recognized and accessible option for patients across the United States.
Psilocybin stands apart from the broader psychedelic landscape through its unique molecular profile, growing body of clinical evidence, and rapid evolution in legal status across the USA. From its classification as a Schedule I substance to landmark research at institutions like Johns Hopkins — where studies have shown lasting relief from major depression, reduced cancer-related anxiety, and promising results for smoking cessation — psilocybin is no longer a fringe topic. While risks and side effects remain real considerations, the safety guidelines established by researchers have helped shape a more responsible path forward for both science and public understanding.
The future of psychedelic medicine in the USA is unfolding in real time. With ongoing clinical trials exploring psilocybin’s potential for PTSD, opioid addiction, Alzheimer’s disease, and alcohol use disorder, the next decade could redefine how mental health is treated nationwide. If you want to stay informed, consider exploring credible resources — including the educational courses now offered by Johns Hopkins researchers — and always consult a qualified healthcare professional before making any decisions related to your mental health. This is a space worth watching closely.